
Anxiety Assessment Tools: How to Choose, Score, and Document Them
Compare the GAD-7, BAI, HAM-A and other anxiety tools — with score ranges, severity cutoffs, and guidance on which to use when.


Anxiety affects millions of people, which makes accurate assessment central to diagnosis and treatment planning. Behavioral health clinicians rely on anxiety assessment tools — the GAD-7, the Beck Anxiety Inventory (BAI), the Hamilton Anxiety Rating Scale (HAM-A) and others — to screen, characterize severity, and monitor change over time. This guide covers which anxiety screening tools are used in clinical practice, how each is scored and interpreted, how to choose between them, and how to document the result so it holds up on review.
What you'll learn
- Which anxiety assessment tools — GAD-7, BAI, HAM-A and others — are used in clinical settings, and what each measures
- The difference between screening, assessment, and diagnostic evaluation, and what current USPSTF guidance recommends
- Score ranges and severity cutoffs for each instrument, in one reference table
- How to choose between the GAD-7 and the BAI, and when neither is the right fit
- How to document a score — and the functional impairment behind it — so it supports medical necessity
- How assessment scores can be captured and tracked inside an EHR
Signs, Symptoms, and Effects of Anxiety
Anxiety is a broad category with different types and presentations, and it can affect emotion, cognitive functioning, behavior, and physical health. It shows up in children and adults and often overlaps with other conditions, which can make it hard to identify.
Adults can usually express what they are feeling and, with fully developed executive function, can often recognize when a thought is disproportionate. Children may not be able to recognize or put words to the same experience.
Anxiety is also frequently comorbid and shares symptoms with many other conditions. Depression, for instance, can involve irritability, sleep disturbance, and fatigue — all of which also appear in anxiety presentations. Clinicians may also need to separate disordered anxiety from ordinary, proportionate worry. Structured assessment tools help with both problems.
Signs and Symptoms of Anxiety
Presentation varies across anxiety types, from a specific phobia to generalized anxiety disorder (GAD), but common signs and symptoms include:
- Worry or fear that is hard to control
- Difficulty concentrating
- Restlessness or an inability to relax
- Irritability
- Rapid breathing
- A sense of impending danger or doom
- Avoidance of certain situations or events
- Social isolation or withdrawal
- Poor sleep or trouble falling asleep
- Sweating, shakiness, or fatigue
- Distractibility
- Digestive issues
- Panic attacks
- Aches and pains
Note that while older texts grouped them with anxiety disorders, the DSM-5-TR does not classify obsessive-compulsive disorder (OCD) or post-traumatic stress disorder (PTSD) as anxiety disorders.
Effects of Anxiety
Anxiety can affect a client's ability to function day to day. The symptoms above are burdensome on their own, and they tend to extend into other areas — education, work performance, relationships, and social participation.
Adults often seek help once they notice these effects. Teens and children may not recognize when they need support, so parents, teachers, and counselors may be the ones to notice behavioral changes such as school refusal, increased crying, or difficulty in class. Assessment tools help put language around experiences clients of any age may struggle to describe.
What Are Anxiety Assessment Tools?
Anxiety assessment tools are standardized questionnaires and rating scales used to evaluate the presence, severity, and type of anxiety symptoms. They support diagnostic accuracy by providing measurable indicators and consistency across evaluations and across clinicians.
Which instrument fits depends on client demographics, setting, and presenting concern. Tools are typically designed for specific age ranges and purposes, with published validation behind them. Formats generally fall into three types:
- Rating scales: the client rates severity or frequency along a fixed scale.
- Checklists: the client marks the symptoms or statements that apply.
- Questionnaires: items or prompts that gather more detail on specific domains.
Because anxiety has many contributors and downstream effects, a thorough evaluation may also cover the client's home environment, education or employment, activities, substance use, risk-taking or conduct concerns, relationships, mood, and suicide risk.
Screening, Assessment, or Diagnosis? What Each Tool Can and Cannot Do
These three words get used interchangeably in everyday practice, and the imprecision usually does no harm in conversation. It does cause problems in documentation, where a note that treats a screening score as a diagnostic finding is vulnerable on review. The distinction is worth holding clearly.
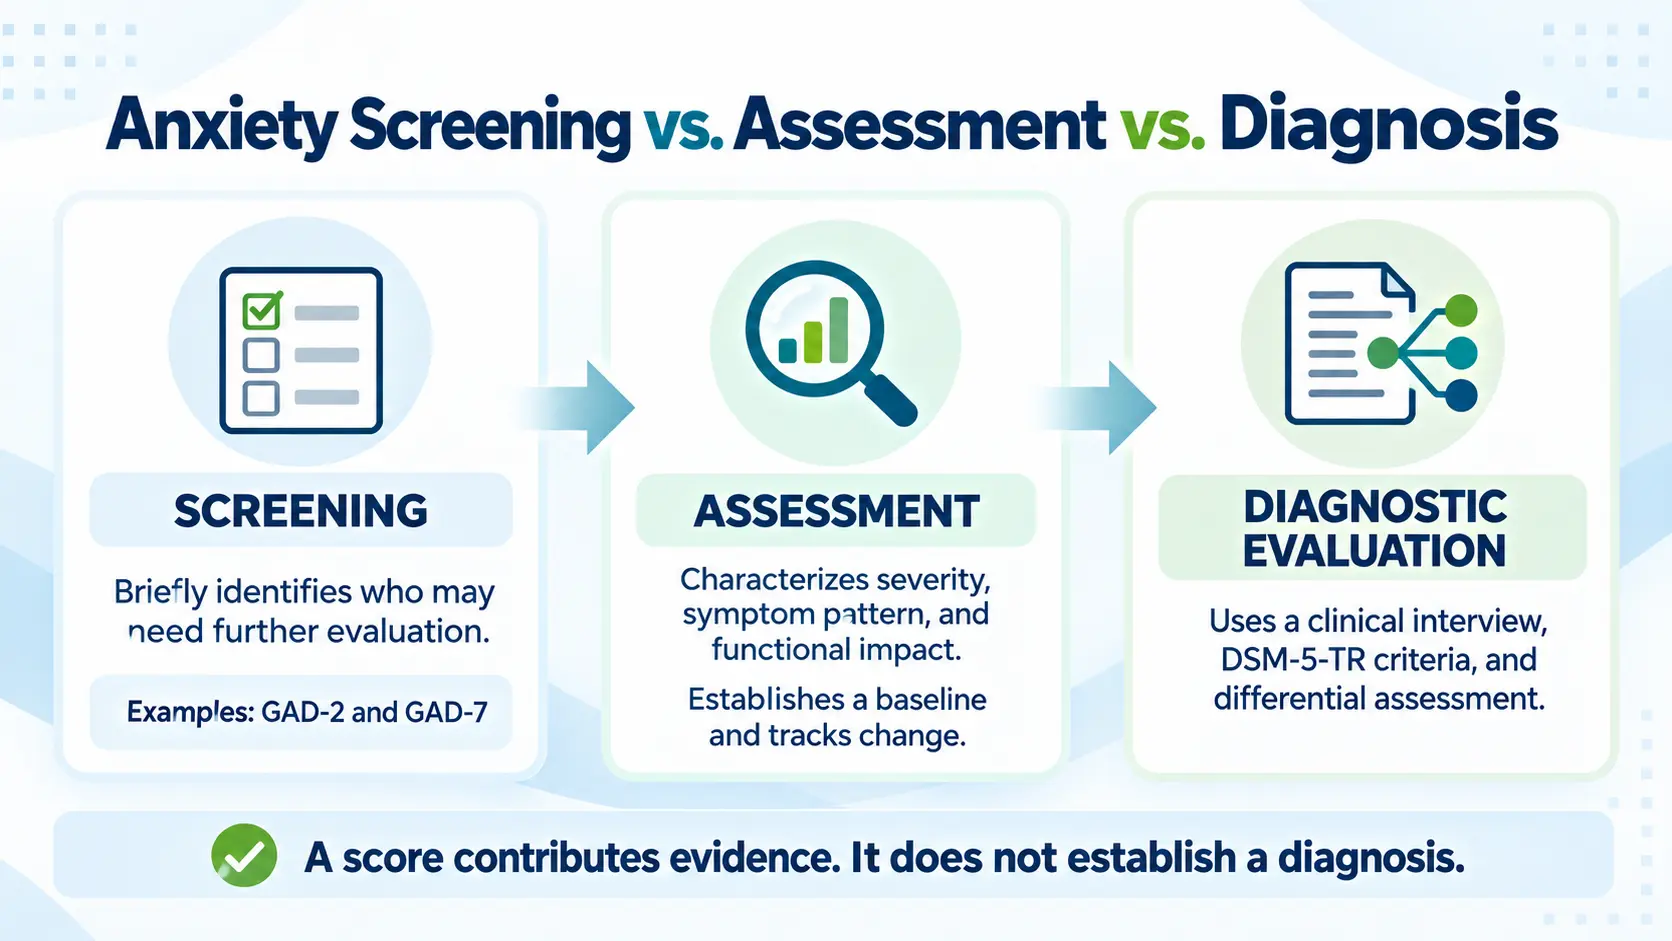
Screening is brief and cast wide. It is applied to people who have not been identified as having anxiety, and its only job is to flag who needs a closer look. Screening accepts false positives in exchange for catching cases that would otherwise be missed — a trade worth making, given that anxiety disorders in primary care have been found to go substantially undetected without systematic screening.⁵ The GAD-7 and GAD-2 are typical screening instruments.
Assessment comes after identification. It characterizes severity, symptom pattern, and functional impact in a client already known to be struggling, and establishes the baseline against which change is measured. The same instrument can do both jobs — a GAD-7 at intake screens, and the same GAD-7 at session six assesses — but the clinical question is different each time.
Diagnostic evaluation is a third activity that no questionnaire performs. It requires a clinical interview against DSM-5-TR criteria, differential assessment of conditions with overlapping presentations, and consideration of medical and substance-related contributors. A score contributes evidence to that process; it does not shortcut it.
| Activity | Clinical question | Who it is applied to | Typical tools |
|---|---|---|---|
| Screening | Does this person need a closer look? | Broad populations, not yet identified | GAD-7, GAD-2, SCARED (pediatric) |
| Assessment | How severe is it, and is it changing? | Clients already identified or in treatment | GAD-7, BAI, HAM-A, DASS-21, RCADS |
| Diagnostic evaluation | Are DSM-5-TR criteria met, and for what? | Clients under clinical evaluation | Clinical interview; structured interviews where indicated |
What Current Screening Guidance Says
For clinicians in the United States, the most directly relevant guidance is the US Preventive Services Task Force recommendation issued in 2023. The Task Force gave a B recommendation for screening adults aged 19 to 64 for anxiety disorders, including those who are pregnant and postpartum. For adults 65 and older it issued an I statement — evidence insufficient to recommend for or against — noting the limited direct evidence on screening benefits in that group.⁴
Two practical consequences follow. First, in most US outpatient settings routine anxiety screening of working-age adults is now guideline-supported, which is useful language to have available when a payer or an administrator asks why a scale is being administered at intake. Second, the absence of a recommendation for older adults is not a recommendation against screening them — it is a gap in the evidence, and clinical judgment still applies.
Why Use Assessment Tools for Anxiety?
Clinicians rely on structured assessment for more than diagnosis. Well-constructed tools offer reliability, validity, and clinical utility — they produce consistent results and help guide decisions.
- Reliability means the instrument yields consistent results across administrations.
- Validity means it measures what it claims to measure. Published instruments go through formal validation, which is why their results carry more weight than an informal impression.
- Clinical utility means the result actually informs treatment planning. These tools turn diffuse experience into a number you can compare over time.
Assessment tools also give clinicians a shared vocabulary. A GAD-7 of 14 communicates something specific to the next clinician who opens the chart, and to a reviewer evaluating whether continued care is warranted.
Commonly Used Anxiety Screening Tools
Generalized Anxiety Disorder Scale (GAD-7)
The GAD-7 is a seven-item self-report questionnaire asking how often the client has been bothered by core anxiety symptoms over the past two weeks. Each item offers four response options scored 0 to 3 — not at all, several days, more than half the days, nearly every day — producing a total of 0 to 21.¹
Scoring: 0–21. Cutpoints of 5, 10, and 15 mark mild, moderate, and severe symptoms. A score of 10 or higher is the commonly cited threshold for probable generalized anxiety disorder and the point at which further assessment is generally recommended.
Psychometrics: at the cut point of 10, the original validation study reported sensitivity of 89% and specificity of 82% for GAD.¹
Strengths: brief enough to administer in about a minute, extensively validated, and free to reproduce — which makes it practical for repeat administration across an episode of care.
Limitations: built around generalized anxiety, so it can under-detect panic, social anxiety, and specific phobia. It screens and tracks severity; it does not diagnose.
One detail worth attending to: the GAD-7 closes with an item asking how difficult the symptoms have made work, home life, and getting along with other people. That item is not included in the 0–21 total, and it is the one clinicians most often skip when charting. Since functional impairment is central to how payers evaluate medical necessity, record the response every time.

Turn GAD-7 Scores Into Defensible Documentation
Download the free GAD-7 Documentation Kit for practical guidance on interpreting scores, documenting clinical reasoning, and connecting symptom severity with functional impairment and medical necessity.
- Interpret GAD-7 scores and severity ranges with confidence
- Adapt sample medical necessity language and progress note wording
- Use the re-administration guide and printable GAD-7 in your workflow
Beck Anxiety Inventory (BAI)
The BAI is a 21-item self-report inventory asking how much the client has been bothered by each of a list of anxiety symptoms over the past week, rated 0 to 3.² Its items lean heavily toward somatic and panic-type symptoms, which is the source of both its main strength and its main limitation.
Scoring: 0–63. Severity bands are 0–7 minimal, 8–15 mild, 16–25 moderate, and 26–63 severe. Scores of 16 and above suggest moderate to severe anxiety.
Age range: designed for ages 17 and older.
Strengths: the somatic emphasis helps separate anxiety from depression, which matters when the two present together and a single global impression is hard to disentangle.
Limitations: that same emphasis can inflate scores in clients with medical conditions that produce similar physical sensations. The BAI is copyrighted and must be licensed from the publisher — it cannot be freely photocopied or posted.
Hamilton Anxiety Rating Scale (HAM-A)
The HAM-A is a 14-item scale completed by the clinician rather than the client, based on a clinical interview.³ This is the most commonly misstated fact about it: it is not a self-report measure. Each item is rated 0 to 4 for severity, producing a total of 0 to 56.
Scoring: 0–56. Commonly cited bands are below 17 mild, 18–24 mild to moderate, 25–30 moderate to severe, and 31 and above severe.
Coverage: splits into psychic anxiety (worry, tension, fear, cognitive symptoms) and somatic anxiety (cardiovascular, respiratory, gastrointestinal, muscular), which is useful when you want to see which side is driving the presentation.
Strengths: long clinical and research history, and a clinician-rated format that does not depend on the client's insight or literacy.
Limitations: requires a trained rater and introduces rater variability. It also includes a depressed-mood item, so it is a poor choice when your goal is specifically to distinguish anxiety from depression — the BAI is the better instrument for that question.
Anxiety Assessment Scoring Reference
Score ranges are the detail clinicians most often need to look up mid-session, and they are easy to confuse because several of these instruments use similar-looking totals for different item counts. This table consolidates them.
| Tool | Items & rating | Total | Severity bands | Reproduction |
|---|---|---|---|---|
| GAD-7 | 7 items, self-report, 0–3 | 0–21 | 0–4 minimal; 5–9 mild; 10–14 moderate; 15–21 severe | Free, no permission required |
| BAI | 21 items, self-report, 0–3 | 0–63 | 0–7 minimal; 8–15 mild; 16–25 moderate; 26–63 severe | Copyrighted; license required |
| HAM-A | 14 items, clinician-rated, 0–4 | 0–56 | below 17 mild; 18–24 mild to moderate; 25–30 moderate to severe; 31+ severe | |
| DASS-21 | 21 items (7 per subscale), self-report, 0–3 | 0–21 per subscale | Subscale-specific; consult the DASS manual | Free for research and clinical use |
| SCARED | 41 items, child & parent versions, 0–2 | 0–82 | Total and subscale cutoffs published by the developers | Free for clinical and research use |
Two cautions on using any of these bands. They describe symptom severity, not diagnosis, and they are population-derived — an individual client’s meaningful change may be smaller or larger than a band boundary suggests. When tracking change over time, interpret the direction and size of movement alongside what the client reports functionally, rather than treating a band crossing as the clinical event.
Documenting a Score So It Holds Up
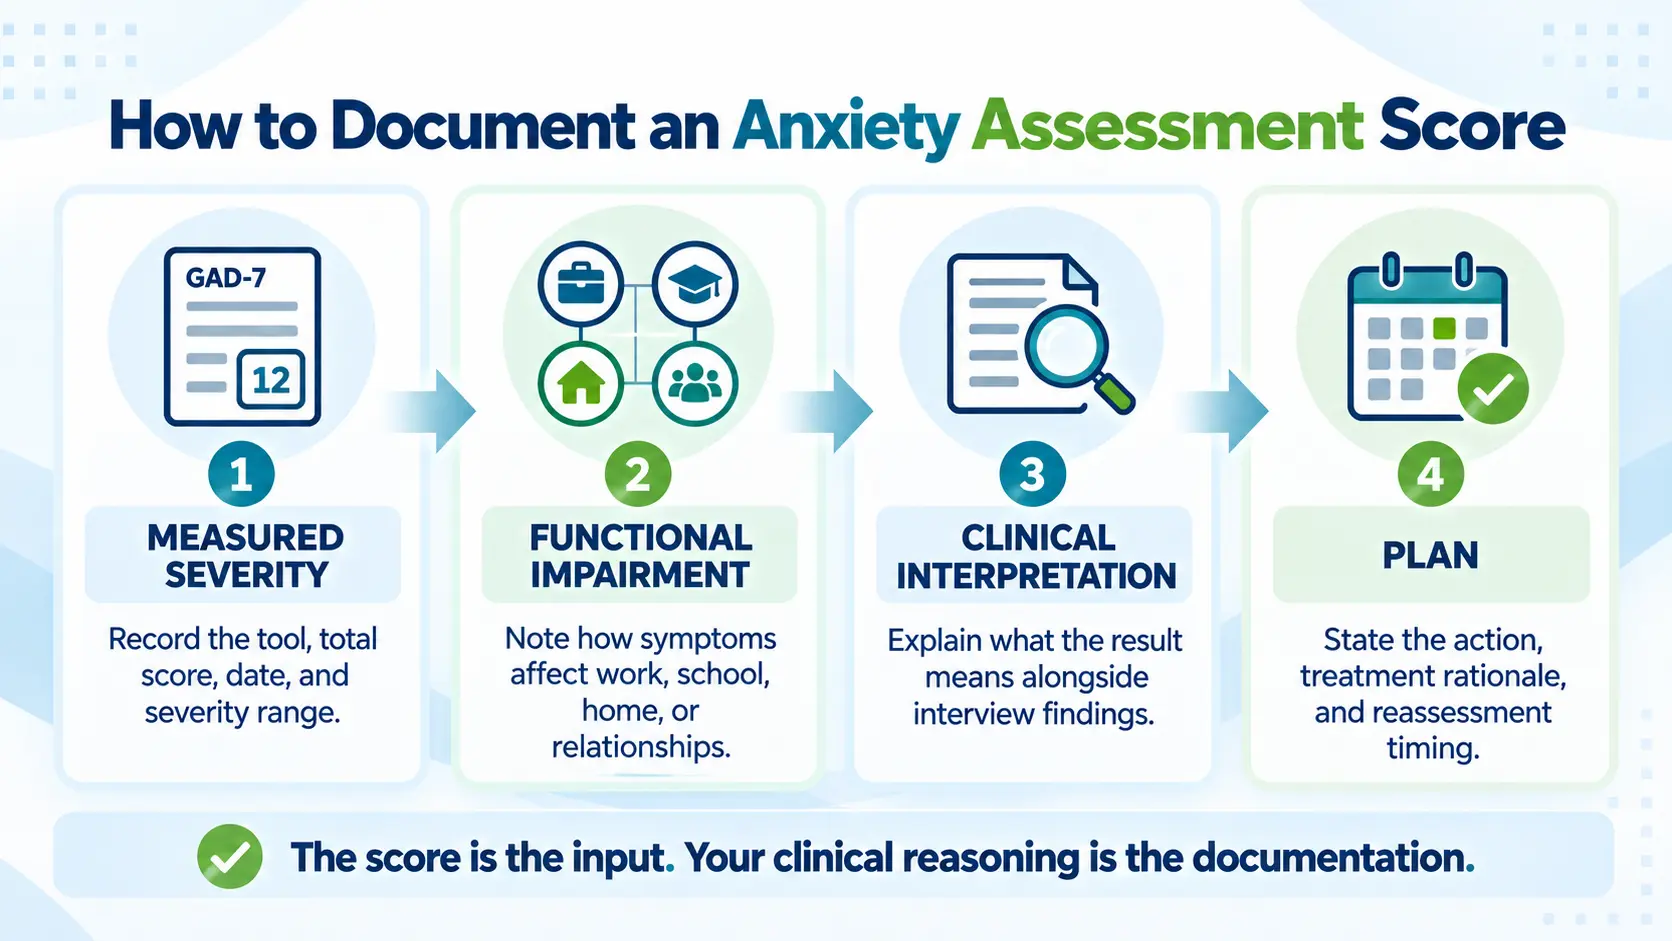
A score recorded without interpretation is one of the more common documentation gaps in behavioral health charts. The score itself is not the clinical reasoning; it is the input to it. A defensible entry generally connects four things: the measured severity, the functional impairment it corresponds to, what you concluded, and what you are doing about it.
Where a score and your clinical impression diverge, say so explicitly and explain the reasoning. A documented discrepancy reads as careful assessment. A silent one reads as an oversight.
How Clinicians Choose the Right Anxiety Scales
When selecting an anxiety scale, clinicians weigh several factors to make sure the instrument fits the setting and the client population: the target age group, the time required to administer it, whether it is free or proprietary, whether it has been adapted for the client’s language and culture, and whether it suits the context of care — telehealth, primary care, or traditional outpatient therapy.
Use the table below to compare adult and pediatric measures, then follow the if/then guide to narrow to a tool for your setting.
Anxiety Assessment Tools — Quick Comparison
| Tool | Format & length | Primary focus | Age range | Strengths | Limitations |
|---|---|---|---|---|---|
| BAI | 21 self-report items | Somatic & cognitive anxiety symptoms | Adolescents & adults | Quick to complete; good for tracking severity over time | Less effective at differentiating anxiety subtypes |
| GAD-7 | 7 self-report items | Core symptoms of generalized anxiety disorder | Adolescents & adults | Very brief; widely validated; excellent for screening | Focused mainly on GAD — may miss other anxiety disorders |
| HAM-A | 14 clinician-rated items | Psychic & somatic anxiety symptoms | Adults | Long-standing clinical use; covers psychological & physical symptoms | Requires clinician administration; more subjective |
| SCARED | 41 self-report items (child & parent versions) | Multiple anxiety disorders (GAD, social, separation) | Children & adolescents | Comprehensive; covers multiple anxiety types | Longer to administer; best for pediatric use |
| STAI | 40 self-report items | Separates temporary “state” from general “trait” anxiety | Adults (youth adaptations exist) | Useful for research; distinguishes acute vs. chronic anxiety | Longer; not disorder-specific |
| Zung SAS | 20 self-report items | Anxiety symptoms (somatic emphasis) | Adolescents & adults | Simple scoring; useful for large-scale screening | Less sensitive to mild anxiety; older norms |
| DASS-21 | 21 self-report items (7 per scale) | Depression, anxiety, and stress | Adults (16+) | Measures three related constructs in one tool | Not diagnostic; anxiety scale less detailed than BAI or HAM-A |
| RCADS | 47 self-report items (child & parent versions) | Anxiety disorders + depression (DSM-aligned subscales) | Children & adolescents | DSM-aligned subscales; detailed profiles | Lengthy; may be too detailed for quick screening |
If/Then Decision Guide for Anxiety Assessment Tools
Start at the top and answer each question in sequence. Follow the Yes column to find the tool that fits. If no, move to the next decision point.
| Decision point | Yes → tool(s) | No → next step |
|---|---|---|
| Is your client a child or adolescent? | SCARED or RCADS | Go to next row |
| Do you want to briefly screen for generalized anxiety? | GAD-7 | Go to next row |
| Do you need to assess physical symptoms of anxiety? | BAI | Go to next row |
| Do you prefer a clinician-rated tool? | HAM-A | DASS-21 |

GAD-7 vs. Beck Anxiety Inventory: Which to Use When
This is the comparison clinicians ask about most, and the two instruments are different enough that the choice is usually straightforward once the question is framed correctly. They are not competing measures of the same thing.
| GAD-7 | Beck Anxiety Inventory | |
|---|---|---|
| Length | 7 items, about 1 minute | 21 items, about 5–10 minutes |
| Recall window | Past 2 weeks | Past week |
| Symptom emphasis | Worry, tension, restlessness, irritability | Somatic and panic-type sensations |
| Best suited to | Generalized anxiety; routine repeat measurement | Somatic or panic presentations; separating anxiety from depression |
| Total range | 0–21 | 0–63 |
| Cost | Free to reproduce | Licensed from the publisher |
| Administration | Self-report | Self-report |
Reach for the GAD-7 when you need a baseline you will re-administer repeatedly. Its brevity is the clinical feature — a one-minute instrument actually gets completed at session six and session twelve, where a ten-minute one quietly stops happening. Its two-week window also means it should not be administered more often than every two weeks, or consecutive administrations measure overlapping periods.
Reach for the BAI when the presentation is physical — chest tightness, dizziness, sensations the client is interpreting as medical — or when anxiety and depression are tangled and you want an instrument whose content does not overlap with mood. Pairing the BAI with a depression measure gives you two readings that are genuinely distinguishable.
Reach for neither when the client is a child or adolescent. Both are adult and older-adolescent instruments; the SCARED and RCADS are built for younger clients and cover anxiety subtypes the adult scales do not separate. The SCARED, like the GAD-7, is available at no cost.
A practical pattern in many practices: administer the GAD-7 routinely at intake and at defined intervals, and add a second instrument selectively when the presentation or the clinical question calls for it. That keeps measurement consistent enough to trend while leaving room for the cases where the brief screen is not telling you what you need to know.
Using Anxiety Questionnaires in Treatment Planning
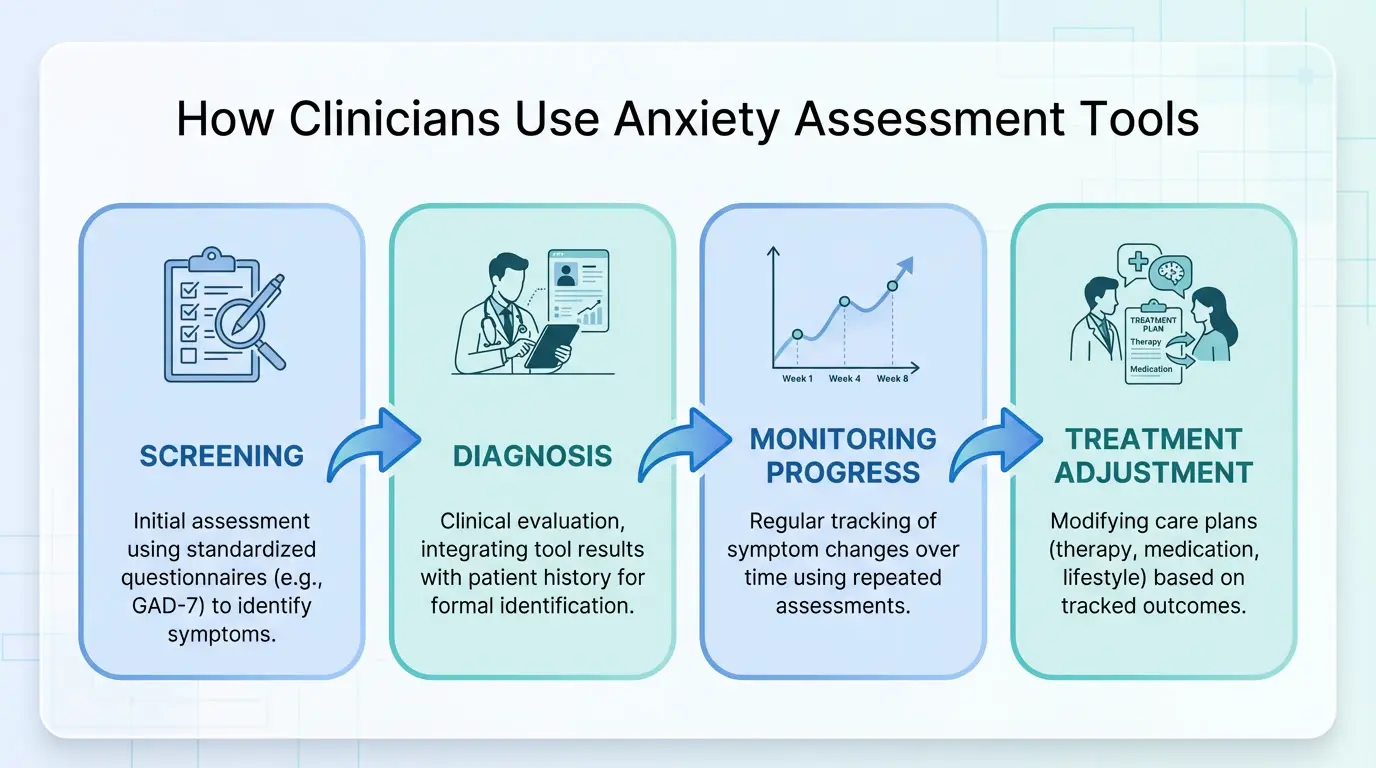
Once completed, anxiety questionnaires produce data that applies directly to treatment planning. Clinicians use results to track progress over time, adjust therapeutic interventions as severity changes, and communicate findings to payers when required. Documented scores also support evidence-based charting, which matters during utilization review and when establishing the medical necessity of continued care.
Best Practices for Using Anxiety Assessment Tools
To get the most out of these instruments, administer them during the intake process and at defined intervals through treatment rather than ad hoc. Pair them with clinical interview — a score and a conversation together give a fuller picture than either alone. Record results in the EHR so the history stays continuous and available to whoever opens the chart next. And share results with clients: seeing a number move can support insight and collaboration, and it gives the two of you a shared reference point.
Related Assessment & Treatment Resources
- How to Write a Treatment Plan for Anxiety
- Understanding the Relationship Between Anxiety and Trauma
- Acceptance and Commitment Therapy for Anxiety
- Top Interventions for Anxiety
Using Anxiety Assessments Inside an EHR
Everything above assumes you can find a client's score history when you need it. In practice that is where measurement-based care most often breaks down. A GAD-7 typed into a narrative note at session three is effectively invisible by session twelve — which is exactly when you need it, for a treatment plan review or a continued-care request.
If you are evaluating how an EHR handles rating scales, three questions separate systems that make this workable from systems that technically support it:
Are scores captured as discrete data?
A score typed into a free-text field cannot be sorted, trended, or reported on. A score captured in a structured field can.
Can you see the series in one place?
Reading a trend should not require opening six notes and reconstructing it by hand.
Can clients complete scales before the session?
Collecting a GAD-7 through a portal ahead of time means the score is available when the session starts, rather than consuming session time.
ICANotes includes over 100 clinical rating scales, among them the GAD-7 and PHQ-9, available directly within the charting workflow. Scores are captured as structured data that posts to the client's chart, where the history can be tracked over time alongside the rest of your documentation. Scales and intake forms can also be sent to clients through the secure client portal and completed before the appointment.
See clinical assessment tools in ICANotes, or plans and pricing, for detail on how assessments fit into the documentation workflow.
See how assessment scores flow into documentation
Capture the GAD-7, PHQ-9, and over 100 other clinical rating scales as structured data that posts to the chart and trends over time. Start a free trial to see how assessments fit into your documentation workflow.
- Access 100+ built-in clinical rating scales, including the GAD-7 and PHQ-9
- Capture assessment scores as structured data directly in the client chart
- Review score histories and symptom trends in one place
- Send assessments through the secure client portal for completion before appointments
See how ICANotes can support your clinical workflow. Start your free trial or book a product demo today!
Start Your Free 30-Day Trial
Explore ICANotes with no obligation. No credit card required.
Final Thoughts on Anxiety Assessment
Anxiety assessment tools are central to identifying, characterizing, and monitoring anxiety symptoms. The GAD-7, BAI, and HAM-A are widely used because each has published validation behind it and each answers a slightly different clinical question. Choosing deliberately between them — and documenting both the score and the functional impairment it corresponds to — is what turns a number in a chart into clinical reasoning a reviewer can follow.
Frequently Asked Questions About Anxiety Assessment Tools
How does the GAD-7 scale work and how effective is it for anxiety screening?
Which anxiety assessment tools measure both frequency and intensity of symptoms?
How often should clinicians administer anxiety assessment tools to monitor patient progress?
Do anxiety assessment tools differentiate anxiety disorders from depression or other comorbidities?
Is the GAD-7 a diagnostic tool?
What is the difference between anxiety screening and anxiety assessment?
What is the Beck Anxiety Inventory score range and how is it interpreted?
Should I use the GAD-7 or the Beck Anxiety Inventory?
What is the Hamilton Anxiety Rating Scale score range?
Does the USPSTF recommend screening adults for anxiety?
Which anxiety assessment tools are free to use?
References
- Spitzer, R. L., Kroenke, K., Williams, J. B. W., & Löwe, B. (2006). A brief measure for assessing generalized anxiety disorder: The GAD-7. Archives of Internal Medicine, 166(10), 1092–1097. PMID 16717171
- Beck, A. T., Epstein, N., Brown, G., & Steer, R. A. (1988). An inventory for measuring clinical anxiety: Psychometric properties. Journal of Consulting and Clinical Psychology, 56(6), 893–897. PMID 3204199
- Hamilton, M. (1959). The assessment of anxiety states by rating. British Journal of Medical Psychology, 32(1), 50–55. PMID 13638508
- US Preventive Services Task Force. (2023). Screening for anxiety disorders in adults: US Preventive Services Task Force recommendation statement. JAMA, 329(24), 2163–2170. PMID 37338866
- Kroenke, K., Spitzer, R. L., Williams, J. B. W., Monahan, P. O., & Löwe, B. (2007). Anxiety disorders in primary care: Prevalence, impairment, comorbidity, and detection. Annals of Internal Medicine, 146(5), 317–325. PMID 17339617
Dr. October Boyles
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.





