
Blog > Treatment Strategies > DBT Skills: A Clinician's Guide to Modules, Stages & Techniques
DBT Basics Explained: Skills, Stages, Techniques & Treatment Planning

Katie Cox, MA, LPCC
Last Updated: September 9, 2026


What You'll Learn
-
What Dialectical Behavior Therapy (DBT) is and the conditions it is designed to treat
-
The four stages of DBT treatment and how clinicians use them to guide treatment planning
-
How long DBT treatment typically takes and the core components of a comprehensive DBT program
-
The four DBT skills modules — Mindfulness, Distress Tolerance, Emotion Regulation, and Interpersonal Effectiveness
-
Common DBT skills and techniques, including Wise Mind, TIPP, PLEASE, DEAR MAN, GIVE, and FAST
-
How clinicians document, code, and bill for DBT individual and group therapy sessions
Contents
- What Is DBT?
- DBT vs CBT: What's the Difference?
- What Is DBT Used For?
- What Are the Stages of DBT Treatment?
- How Long Does DBT Treatment Take?
- What Does a Comprehensive DBT Program Include?
- What Are DBT Skills? The 4 Modules and Core Techniques
- Using DBT to Help Your Patients
- Frequently Asked Questions About DBT Basics
Dialectical Behavior Therapy (DBT) is an evidence-based treatment that combines acceptance and change strategies to help clients manage intense emotions, reduce self-destructive behaviors, and build healthier relationships. Originally developed for borderline personality disorder, DBT is now used across a range of presentations involving emotion dysregulation. This guide covers DBT basics: what it treats, its four stages, and the core skills clinicians teach.
What Is DBT?
Dialectical Behavior Therapy was developed by psychologist Marsha Linehan in the late 1980s, originally to treat chronically suicidal individuals diagnosed with borderline personality disorder (BPD). It's a derivative of cognitive behavioral therapy (CBT), but with a key difference: DBT explicitly balances acceptance of a client's present-moment experience with change-oriented strategies to build new skills and behaviors. That balance — the “dialectic” — is where the therapy gets its name.
DBT rests on a core assumption: clients are doing the best they can, and they also need to do better, try harder, and be more motivated to change. Holding both of those truths at once, rather than treating them as contradictory, is central to how DBT clinicians approach treatment.
A standard DBT program combines four components: individual therapy, group skills training, between-session phone or skills coaching, and a therapist consultation team. Each plays a distinct role, which we cover in What Does a Comprehensive DBT Program Include? below.
DBT vs. CBT: What's the Difference?
Dialectical Behavior Therapy (DBT) evolved from Cognitive Behavioral Therapy (CBT) and shares CBT's focus on helping clients identify unhelpful thoughts, emotions, and behaviors. However, DBT adds a stronger emphasis on acceptance, emotional regulation, and skills training.
While traditional CBT primarily focuses on changing distorted thinking patterns and maladaptive behaviors, DBT balances change-oriented strategies with acceptance-based approaches. This dialectical perspective helps clients learn to accept their current experiences while simultaneously working toward meaningful change.
DBT is often used with clients who experience significant emotion dysregulation, chronic suicidality, self-harm, impulsive behaviors, or unstable relationships. CBT is commonly used to treat conditions such as anxiety disorders, depression, phobias, obsessive-compulsive disorder, and insomnia.
Rather than viewing DBT and CBT as competing approaches, it's more accurate to think of DBT as an evolution of CBT that was specifically designed to address severe emotional dysregulation and high-risk behaviors. Many clinicians integrate principles from both approaches depending on a client's presenting concerns and treatment goals.
While DBT and CBT share many foundational principles, they differ in their emphasis, structure, and clinical applications. The infographic below highlights some of the most important distinctions clinicians should understand when selecting or integrating these treatment approaches.
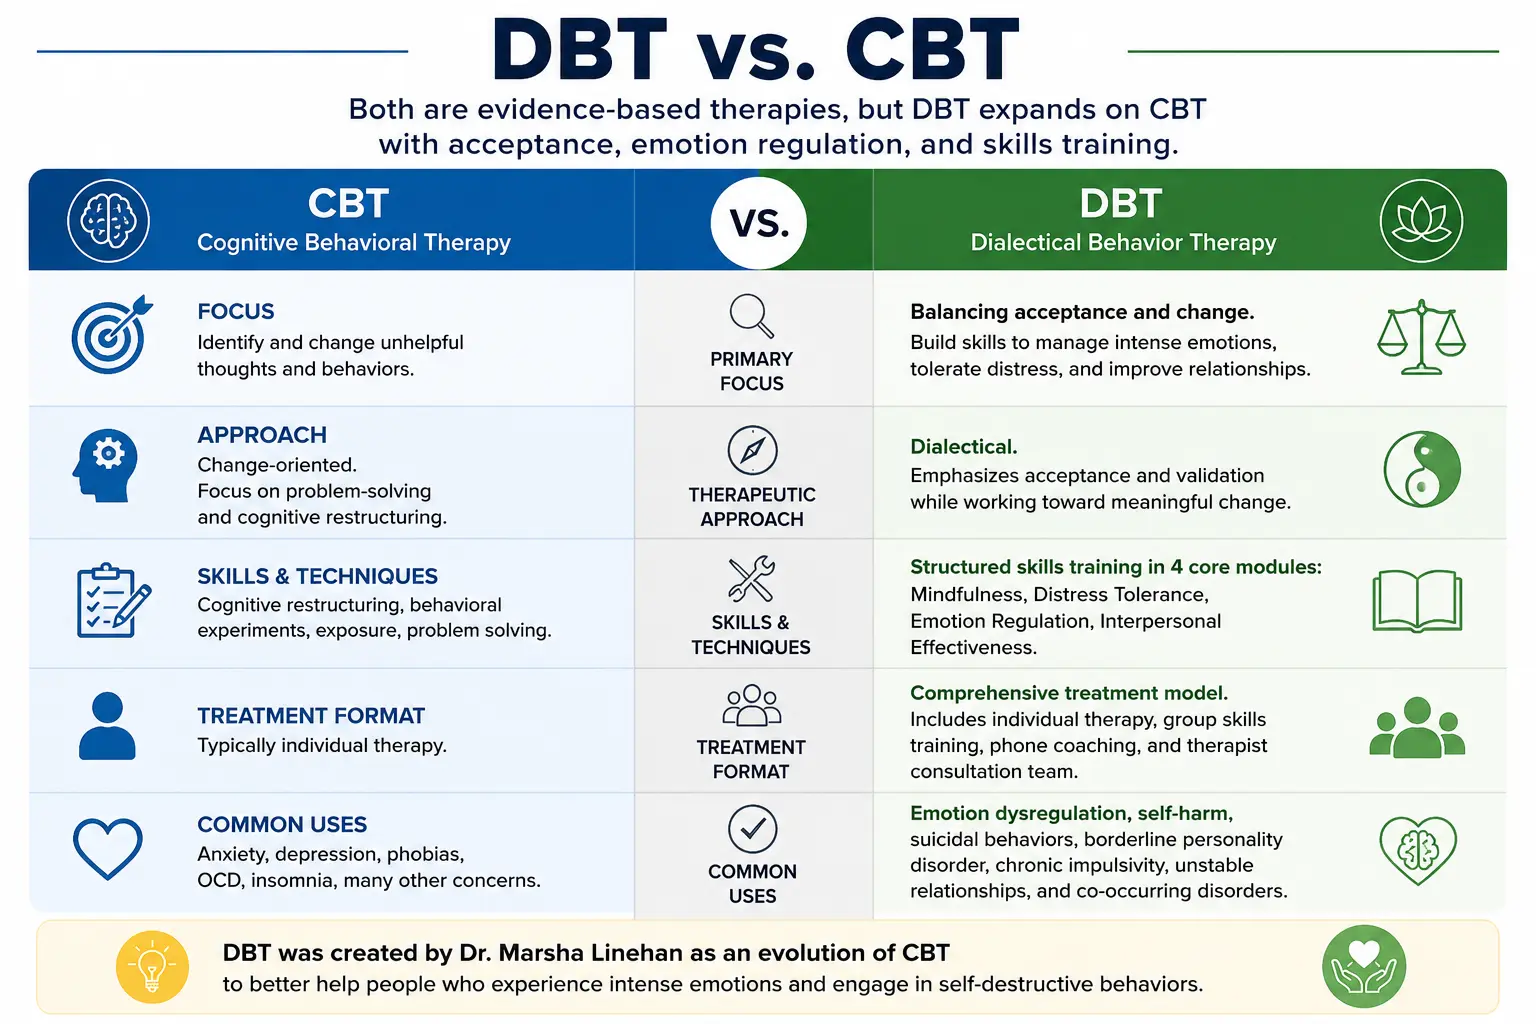
Although both therapies are evidence-based and goal-oriented, DBT was specifically developed to help clients who experience severe emotion dysregulation, self-destructive behaviors, and chronic interpersonal difficulties.
What Is DBT Used For?
DBT was originally designed for borderline personality disorder, and it remains one of the most well-supported treatments for BPD. Since then, clinicians have adapted it for a broader range of presentations involving emotion dysregulation, including:
- Chronic suicidal ideation and self-harming behavior
- Substance use disorders
- Eating disorders, particularly binge eating disorder and bulimia nervosa
- Post-traumatic stress disorder (PTSD)
- Treatment-resistant depression
- Bipolar disorder
- Difficulty regulating anger or impulsivity
DBT is also used with adolescents (DBT-A) and has been adapted for family and multi-family group formats. It's not a fit for every client — those without significant emotion regulation difficulties, or who need a higher level of care than an outpatient DBT program offers, may be better served by another modality or level of care.
DBT for Adolescents (DBT-A)
DBT-A teaches adolescent clients the same four skills modules as the adult model, with one addition: “Walking the Middle Path” skills. According to WVU School of Medicine, these skills target flexible patterns of thinking, self-validation and validating others, and effective problem-solving, helping teens hold two seemingly opposite truths at once instead of getting stuck in all-or-nothing thinking.
DBT-A also brings the family into treatment. Per the same source, family sessions work toward more balanced patterns of interaction, better communication among family members, and contingencies that reinforce effective, skillful behavior. In practice, that means helping families find the middle path across three recurring tensions: normalizing pathological behavior versus pathologizing normative behavior, excessive leniency versus authoritarian control, and fostering dependence versus forcing autonomy.
Evidence and Effectiveness of DBT
DBT's evidence base is strongest for BPD, but it extends well beyond symptom reduction. According to Cleveland Clinic, clients with borderline personality disorder who complete DBT show less self-harm behavior and anger, fewer days of inpatient hospitalization, less drug and alcohol misuse, and improved depressive symptoms.
A 2015 study by Linehan and colleagues, cited by Psychwire, found that skills training alone, apart from the full DBT protocol, accounts for unique reductions in non-suicidal self-injury, depression, and anxiety symptoms. That's a meaningful data point for clinicians weighing a skills-only group against a full comprehensive program. More broadly, Hernandez-Bustamante and colleagues (2024), also cited by Psychwire, found that both the full DBT protocol and short-term DBT reduce suicidality, general psychopathology, and depressive symptoms in people with BPD, while improving compliance, impulsivity, mood stability, and hospitalization frequency.
Get the DBT Skills Quick-Reference Guide
Save time preparing for DBT sessions with a practical DBT skills cheat sheet designed for behavioral health clinicians. This free resource gives you a complete DBT skills overview, summarizing all four modules, and includes a reusable client worksheet for skills practice and reflection.
- Overview of all four DBT skills modules
- Mindfulness, Distress Tolerance, Emotion Regulation, and Interpersonal Effectiveness techniques
- Named DBT skills including Wise Mind, STOP, TIPP, PLEASE, DEAR MAN, GIVE, and FAST
- Module selector to help match presenting concerns to the right skills
- Printable DBT Skill Practice Log worksheet for client use
Download Your Free Guide
Get instant access to the DBT Skills Quick-Reference Guide for clinicians.
Free download. Instant access.
What are the Stages of DBT Treatment?
DBT treatment is typically organized into four stages, each with its own goals and priorities. While clients may move through the stages at different speeds, the overall progression is designed to help them move from crisis and behavioral dyscontrol toward emotional well-being, meaningful relationships, and a life worth living.

Linehan organized DBT treatment into four stages, each with its own target and exit criteria. Clients move through the stages in order, though the pace varies widely based on presenting severity. The table below provides a more detailed look at each stage, including its primary treatment targets and overall therapeutic goals.
| Stage | Primary Target | Goal |
|---|---|---|
| Stage 1: Achieving Behavioral Control | Life-threatening behaviors, therapy-interfering behaviors, and severe quality-of-life-interfering behaviors, such as suicidality, self-harm, or substance use | Move the client out of crisis and behavioral dyscontrol into safety and stability |
| Stage 2: Reducing Quiet Desperation | Trauma, intense emotional suffering, and inhibited emotional experiencing | Help the client move from emotional shutdown or quiet desperation to full emotional experiencing |
| Stage 3: Resolving Ordinary Problems in Living | Self-respect, relationship problems, and individual goals | Build a “life worth living” by addressing everyday problems in living |
| Stage 4: Building Capacity for Joy and Connection | Incompleteness, lack of connectedness, or lack of meaning | Develop a sustained capacity for joy and a deeper sense of connection or purpose |
A client's DBT treatment plan should identify which stage they're starting in and what target behaviors define progress out of that stage — this is one of the most common documentation gaps clinicians run into when starting DBT with a new client.
While every client's needs and goals will differ, a DBT treatment plan typically includes the client's current treatment stage, target behaviors, measurable objectives, and the specific DBT skills or interventions that will be used to support progress. The simplified example below illustrates how these elements may come together in practice.
Example: DBT Treatment Plan Goal
Presenting Problem: Recurrent self-harm urges and difficulty regulating emotions
Current DBT Stage: Stage 1: Achieving Behavioral Control
Long-Term Goal: Eliminate self-harm behaviors and improve emotional regulation
Objectives:
- Complete a daily diary card
- Practice TIPP skills during emotional crises
- Attend weekly DBT skills training sessions
- Identify triggers through chain analysis
Interventions:
- Weekly individual DBT therapy
- Group skills training
- Skills coaching between sessions
- Distress tolerance and emotion regulation skills practice
As clients make progress toward their treatment goals, the focus of DBT gradually shifts from crisis stabilization to building emotional resilience, improving relationships, and creating a life worth living. The timeline for reaching those milestones varies considerably depending on symptom severity, treatment engagement, and the client's starting stage.
How Long Does DBT Treatment Take?
A full DBT program is typically structured in 24-week cycles, often repeated for a full year so clients move through all four skills modules at least once (and sometimes twice). Clients with significant Stage 1 needs — active self-harm, suicidality, or severe behavioral dyscontrol — often stay in DBT for a year or longer before transitioning to Stage 2 work.
That said, “DBT” is sometimes used loosely to describe shorter skills-only groups (8–16 weeks) that teach the four modules without the full individual therapy and coaching components. These can be useful, but they aren't equivalent to comprehensive DBT, and it's worth being clear with clients and referral sources about which version they're getting.
According to Cleveland Clinic, DBT usually takes at least six months to a year, and clients shouldn't expect to be completely free of symptoms or problematic behaviors after just one year, especially with BPD. Many clinicians find that treatment for BPD, specifically, can take several years. It's worth setting that expectation with clients early. Progress in DBT tends to be gradual, and any progress toward the client's goals is good progress worth recognizing as such.
What Does a Comprehensive DBT Program Include?
Linehan's model specifies four components that work together. Dropping any one of them changes what the client is actually receiving.
Pre-Assessment
Most programs start here, before any of the four core components. According to Cleveland Clinic, the therapist uses this session to determine how suitable DBT is for the client, explain how the treatment works, and, if it's a good fit, secure the client's commitment to the treatment and its length before moving forward.
Group Skills Training
A weekly group, usually 90–150 minutes, where a skills trainer leads dialectical behavior therapy skills training across a structured curriculum covering all four modules. Groups are psychoeducational rather than process-oriented — the focus is on learning and practicing specific skills, not on processing group dynamics.
Individual Therapy
A weekly one-on-one session with a primary DBT therapist who helps the client apply skills to their actual life, using diary cards and chain analysis to understand what's driving target behaviors. The individual therapist also tracks the client's stage and overall treatment plan.
Phone or Skills Coaching
Brief, between-session contact, often by phone or text, that lets clients get in-the-moment coaching on using a skill during a crisis rather than waiting until the next session. Coaching calls are typically short and skills-focused, not full crisis sessions.
Diary Cards
A daily self-monitoring tool where clients track target behaviors, including urges, actions, emotions, and which skills they used. Diary cards are reviewed at the start of each individual session and directly shape that session's agenda.
The infographic below provides a visual overview of the four DBT skills modules and some of the most commonly taught DBT techniques used in clinical practice.

What are DBT Skills? The 4 Modules and Core Techniques
DBT skills are organized into four modules, split across two broader categories: Acceptance skills (Mindfulness and Distress Tolerance), which help clients tolerate and accept present-moment reality, and Change skills (Emotion Regulation and Interpersonal Effectiveness), which help clients build new patterns and responses.
| Module | Category | Core Techniques | Primarily Used For |
|---|---|---|---|
| Mindfulness | Acceptance | Wise Mind; Observe, Describe, Participate; Non-judgmentally, One-mindfully, Effectively | Grounding in the present moment; the foundation for all other modules |
| Distress Tolerance | Acceptance | STOP, TIPP, Self-Soothe, Radical Acceptance, IMPROVE, Pros and Cons | Surviving crises without making them worse |
| Emotion Regulation | Change | Check the Facts, Opposite Action, PLEASE, Build Positive Experiences, Reduce Vulnerability | Understanding and changing unwanted emotional responses |
| Interpersonal Effectiveness | Change | DEAR MAN, GIVE, FAST | Asking for what you need and setting boundaries while keeping relationships and self-respect intact |
Complete DBT Skills List
DBT skills are grouped into four core modules that form the foundation of Dialectical Behavior Therapy: Mindfulness, Distress Tolerance, Emotion Regulation, and Interpersonal Effectiveness. The complete DBT skills list below, which doubles as a DBT coping skills list for treatment planning and client handouts, includes the most commonly taught techniques clinicians use in treatment. Clients and clinicians alike often ask which are the best DBT skills to start with, and Wise Mind and STOP are usually the most accessible entry points because they translate quickly into daily situations.
Mindfulness Skills
- Wise Mind
- Observe
- Describe
- Participate
- Non-judgmentally
- One-mindfully
- Effectively
Distress Tolerance Skills
- STOP
- TIPP
- Self-Soothe
- Distract with Wise Mind ACCEPTS
- Willingness
- Half-Smile
- Radical Acceptance
- IMPROVE
- Pros and Cons
Emotion Regulation Skills
- Check the Facts
- Opposite Action
- PLEASE
- Problem Solving
- Build Positive Experiences
- Reduce Vulnerability
Interpersonal Effectiveness Skills
- DEAR MAN
- GIVE
- FAST
- Factors Reducing Interpersonal Effectiveness
Mindfulness Skills
Mindfulness is considered the foundation of DBT — clients return to it throughout every other module. Linehan organized mindfulness into “what” skills (Observe, Describe, Participate) and “how” skills (Non-judgmentally, One-mindfully, Effectively). Clinicians also teach the concept of Wise Mind — the integration of “emotion mind” and “reasonable mind” — as a touchstone clients can return to when deciding how to respond to a situation.
Mindfulness is an ancient practice that comes from Buddhist and Hindu teachings. It falls under the "acceptance" skills category. While mindfulness comes in many forms, such as deep breathing and meditation, the core principles of DBT mindfulness are about living in the moment without the influence of the past or future. When being mindful, one observes the thoughts and sensations they're experiencing and objectively labels them, rather than being overwhelmed by the emotions that come with them. They focus on one thing at a time, all without judgment.
Since mindfulness focuses on responding objectively, it can be valuable in avoiding self-criticism and other emotional responses that can build up.
One of the more common examples of a mindfulness strategy is deep breathing. Clients are instructed to take deep breaths, sometimes with different counting strategies. While breathing, the client focuses on different sensations around and within them, such as the scent of a nearby candle or the movement of one's body as they breathe. They can then consider thoughts and emotions. These thoughts should be allowed to simply exist as they are without any judgment or negativity attached.
Distress Tolerance Skills
Distress tolerance skills help clients get through a crisis without making it worse, before they've built longer-term emotion regulation skills. Some individuals have a heightened sensitivity to stress and may react in ways that undermine their goals or trigger unwanted behaviors. Distress tolerance, one of DBT’s core acceptance skills, helps clients navigate inevitable life challenges without becoming overwhelmed or impulsive. Rather than trying to eliminate distress altogether, this skill set empowers clients to endure uncomfortable emotions and situations without making things worse. These DBT coping skills give clients something concrete to reach for the moment distress spikes, instead of defaulting to whatever unhelpful habit is closest at hand.
By learning to tolerate mild to moderate distress, clients can reduce the risk of spiraling into unhelpful thought patterns or self-destructive behaviors.
Here are DBT skills examples clinicians teach for crisis moments:
- STOP (Stop, Take a step back, Observe, Proceed mindfully) — an immediate pause skill for high-intensity moments
- TIPP (Temperature, Intense exercise, Paced breathing, Progressive muscle relaxation) — body-based skills that rapidly lower physiological arousal
- Self-Soothe — using the five senses to comfort oneself
- Distract with Wise Mind ACCEPTS — a distraction acronym covering Activities, Contributing, Comparisons, Emotions, Pushing Away, Thoughts, and Sensations, used to step away from a distressing situation just long enough to return with a clearer head
- Willingness — turning toward what's needed in the moment, as opposed to willfulness, as a way of acting from Wise Mind
- Half-Smile — adopting a relaxed, accepting facial expression to help shift internal state toward acceptance
- Radical Acceptance — fully accepting reality as it is, without fighting it, as a way to reduce suffering
- IMPROVE and Pros and Cons — additional crisis-survival and decision-making tools
Emotion Regulation Skills
Emotion regulation skills help clients manage overwhelming emotional responses and reduce their intensity to a more tolerable level. In DBT, this process — often referred to as down-regulation — involves both in-the-moment coping strategies and reflective practices aimed at fostering long-term emotional resilience.
Emotion regulation skills help clients understand what's driving an emotion and change it when it isn't working for them. Therapists teach clients how to recognize, label, and understand their emotional experiences, which is the first step toward gaining control over them. One key technique is cognitive reappraisal, where clients learn to reframe the situation that triggered the emotion in order to change their response. For example, instead of viewing an argument with a friend as a failure, a client might see it as an opportunity to strengthen the relationship through honest communication.
Emotion regulation strategies often overlap with acceptance skills and may include:
-
Check the Facts – testing whether an emotion fits the actual facts of a situation
- PLEASE – (treating PhysicaL illness, balancing Eating, avoiding mood-Altering substances, balancing Sleep, getting Exercise — a foundational skill for reducing emotional vulnerability
- Opposite action – acting opposite to an unhelpful emotional urge
-
Problem Solving – used when the emotion fits the facts and the situation itself needs to change: describing the problem, setting a realistic goal, brainstorming options, choosing and acting on a solution, then evaluating whether it worked
-
Build positive experiences – engaging in activities that promote joy or connection
-
Reducing vulnerability – attending to physical health, sleep, nutrition, and stress management to reduce vulnerability to negative emotions
By developing these skills, clients become better equipped to respond to emotional challenges with intention rather than impulsivity, ultimately improving their ability to function in daily life and build meaningful relationships.
Interpersonal Effectiveness Skills
Strong relationships are essential to mental health, but intense emotions can often interfere with how clients relate to others — and to themselves. Interpersonal effectiveness skills help clients build and maintain healthy relationships while asserting their needs in respectful, balanced ways. These skills support clients in setting boundaries, asking for what they need, saying no when necessary, and managing interpersonal conflicts — without damaging their self-respect or their relationships.
DBT therapists often focus on situations that carry a high emotional charge or risk of harm — such as unmanaged anger directed at a partner or patterns of negative self-talk that can contribute to self-injurious behavior. The goal is to equip clients with tools for navigating these challenges while maintaining both personal integrity and relational stability.
Interpersonal effectiveness skills help clients ask for what they need, say no, and manage conflict — without damaging the relationship or their own self-respect.
The three core acronyms are:
- DEAR MAN (Describe, Express, Assert, Reinforce, stay Mindful, Appear confident, Negotiate) — for making requests or refusing them
- GIVE (be Gentle, act Interested, Validate, use an Easy manner) — for protecting the relationship
- FAST (be Fair, no Apologies, Stick to values, be Truthful) — for protecting self-respect
Clinicians often teach all three together as a single sequence: DEAR MAN for what to say, GIVE for how to say it while preserving the relationship, and FAST for staying true to yourself while saying it.
Clients don't always use these skills even when they know them, and DBT names five Factors Reducing Interpersonal Effectiveness clinicians can check for: Lack of Skill (not knowing what to say or do), Worry Thoughts (anticipatory fears that block action even when the skill is there), Emotions (automatic reactions that shut the interaction down before it starts), Indecision (conflict over competing priorities), and Environment (situations where even a well-judged request can't succeed, or another priority outweighs self-respect in the moment). These factors tend to feed on each other, and it's worth naming that explicitly to clients so the goal doesn't become self-blame for not getting what they wanted.
Finding and Choosing a DBT Therapist
Referring a client to DBT, or deciding whether to build a program yourself, starts with knowing what to look for. A prospective client (or a colleague making a referral) should feel comfortable asking a DBT therapist five questions, per Cleveland Clinic:
- What is the nature of your training in DBT?
- Do you provide comprehensive DBT or a modification? If not comprehensive DBT, why not?
- Do you belong to a DBT consultation team?
- What's your policy on phone calls and emails during the week?
- How much time will you initially ask me to commit to for the entire therapy process?
To locate a DBT therapist, Cleveland Clinic recommends starting with referrals, whether from a primary care provider, a friend, or a family member, and searching local and state psychological associations for therapists who list DBT among their specialties.
Before referring a client or committing to a provider, verify a few basics: confirm the therapist is a state-certified, licensed mental health professional, confirm they treat the client's specific area of concern (self-harm, BPD, eating disorders, and so on), and call or email the office with any remaining questions before making a decision. DBT also isn't limited to one type of provider. Per Cleveland Clinic, a DBT therapist can be a psychiatrist, a psychiatric nurse, a psychologist, a social worker, or a family therapist.
Using DBT to Help Your Patients
DBT is part of a comprehensive approach to treating clients diagnosed with different types of emotional regulation problems. It can help them gain control over the emotions that trigger unhealthy behaviors and get in the way of living the life they want to live. Most DBT strategies have been well-studied and well-documented for their effectiveness, and they can be a strong asset in many treatment plans.
ICANotes streamlines the documentation process for clinicians using DBT by offering a behavioral health–specific EHR designed to support structured, skills-based care. With customizable templates for individual and group therapy sessions, clinicians can efficiently document DBT interventions, reinforce DBT therapy skills between sessions, track client progress across core modules, and ensure that treatment aligns with evidence-based protocols. Built-in features for treatment planning, progress note generation, and outcome measurement make it easier to maintain compliance, support continuity of care, and focus more time on client engagement rather than paperwork. Whether you're delivering DBT in an outpatient setting, partial hospitalization program, or private practice, ICANotes helps you stay organized, efficient, and clinically effective.
Learn more about ICANotes or reach out to us to request a demo. You can also give us a call at (866) 847-3590 with any questions.
Frequently Asked Questions About DBT Skills
+What are the core components of DBT?
A comprehensive DBT program includes four components: weekly individual therapy, weekly group skills training, between-session phone or skills coaching, and a therapist consultation team. All four work together — skills taught in group are reinforced in individual sessions, applied in real time through coaching calls, and clinicians get their own support through the consultation team.
+What are the four stages of DBT treatment?
DBT treatment moves through four stages: Stage 1 (achieving behavioral control, targeting life-threatening and therapy-interfering behaviors), Stage 2 (reducing quiet desperation, addressing trauma and inhibited emotional experiencing), Stage 3 (resolving ordinary problems in living, such as relationship and self-respect issues), and Stage 4 (building capacity for joy and connection). Clients move through the stages in order, though the time spent in each stage varies based on severity.
+Which clients are a good fit for DBT?
DBT was developed for borderline personality disorder and remains strongly indicated for clients with chronic suicidality, self-harm, or significant emotion dysregulation. It's also commonly used for substance use disorders, eating disorders, PTSD, and difficulty managing anger or impulsivity. Clients without significant emotion regulation difficulties, or who need a higher level of care than outpatient DBT provides, are typically better served elsewhere.
+How is DBT different from CBT?
DBT evolved from CBT and shares its focus on identifying unhelpful thoughts and behaviors. The key difference is that DBT adds explicit acceptance-based strategies alongside change-oriented ones. DBT is specifically designed for clients with severe emotion dysregulation, chronic suicidality, or self-harm, while CBT is more commonly used for anxiety, depression, and phobias.
+What are the 4 DBT modules?
The four DBT modules are Mindfulness, Distress Tolerance, Emotion Regulation, and Interpersonal Effectiveness. Mindfulness and Distress Tolerance are acceptance-based skills, while Emotion Regulation and Interpersonal Effectiveness are change-based. Together, they teach clients to stay present, tolerate crises, regulate emotions, and communicate effectively in relationships.
+How do clinicians build a DBT treatment plan?
A DBT treatment plan starts by identifying the client's current stage and target behaviors within that stage — for most new clients, this means Stage 1 targets like self-harm, suicidality, or other life-threatening behavior. From there, the plan should specify which skills modules the client will work through, how progress will be tracked (often via diary cards), and the criteria for moving to the next stage.
+How are DBT skills introduced across each module?
Skills are introduced module by module in group: Mindfulness (Wise Mind, Observe, Describe, Participate) is taught first and revisited throughout, followed by Distress Tolerance (STOP, TIPP, Radical Acceptance), Emotion Regulation (PLEASE, Check the Facts, Opposite Action), and Interpersonal Effectiveness (DEAR MAN, GIVE, FAST). Individual therapists reinforce whichever module the client is currently learning.
+What are the most commonly used DBT skills in clinical practice?
The most frequently taught DBT skills include Wise Mind (Mindfulness), STOP and TIPP (Distress Tolerance), Opposite Action and PLEASE (Emotion Regulation), and DEAR MAN, GIVE, and FAST (Interpersonal Effectiveness). These named skills appear across all four modules and are typically introduced in group, then reinforced in individual sessions using real situations from the client's week.
+How do individual and group DBT sessions differ?
Group sessions are psychoeducational — a skills trainer teaches a module to the full group, with structured practice and homework review. Individual sessions are personalized: the therapist reviews the client's diary card, identifies what drove any target behaviors that week, and works with the client to apply the specific skills they're learning to their actual life using chain analysis.
+How is DBT typically billed?
DBT individual sessions are generally billed using standard psychotherapy codes, such as CPT 90834 or 90837 depending on session length, while DBT group skills training is typically billed under group psychotherapy codes, such as CPT 90853. Coding can vary by payer and by whether a session is primarily skills training versus therapy, so clinicians should confirm requirements with each payer before billing.
Recent Posts






Katie Cox
MA, LPCC
About the Author
Katie Cox, MA, LPCC is a Licensed Professional Clinical Counselor with over 10 years of clinical experience working with adolescents and adults. Her areas of expertise include anxiety, depression, OCD, life transitions, self-esteem, career concerns, and women's mental health. Katie utilizes evidence-based, client-centered approaches to help individuals develop practical coping skills, increase emotional awareness, and achieve their personal goals. Through her clinical work and writing, she is committed to making mental health information accessible, practical, and empowering.