
The Psychiatric Diagnostic Evaluation: Getting 90792 Right
CPT code 90792 covers the psychiatric diagnostic evaluation with medical services, and getting the documentation, timing, and billing details right keeps your claims clean and your notes defensible under audit.


CPT code 90792 is used for a psychiatric diagnostic evaluation that includes medical services, typically performed by psychiatrists, PMHNPs, and other qualified prescribing clinicians. This guide explains CPT 90792 documentation requirements, how 90792 differs from 90791, medical-necessity and ICD-10 considerations, modifier and billing rules, frequency limits, reimbursement considerations, and how to create an audit-ready psychiatric diagnostic evaluation note.
Key takeaways
- CPT code 90792 describes a psychiatric diagnostic evaluation with a medical component, and CMS coverage documentation limits it to prescribing clinicians such as psychiatrists and PMHNPs.
- 90792 is untimed under CPT and CMS rules. The 45 to 90 minute or 60 to 120 minute ranges you may have seen online come from billing companies, not from CMS or the AMA.
- CMS requires no universal modifier for 90792 itself. Modifiers like AF, AH, and AJ come from state Medicaid programs and individual payer contracts, not a federal coding rule.
- Medical necessity for 90792 rests on your ICD-10 diagnosis, and the accepted code list is set by your Medicare Administrative Contractor (MAC), not one single nationwide roster.
- According to ICANotes' 2026 survey of 416 licensed behavioral health professionals, 40% spend six or more hours a week on documentation, and 49% say they could take on more patients if documentation consumed less time.
What CPT Code 90792 Actually Covers
If you are a psychiatrist or a psychiatric-mental-health nurse practitioner, 90792 is probably the first code you bill on almost every new patient. It represents the initial psychiatric diagnostic evaluation, the visit where you build the history, run the mental status exam, and land on a working diagnosis and treatment plan, but with one addition that separates it from its sibling code, 90791: a medical component.
CMS's Local Coverage Determination L33252 quotes the AMA descriptor directly. A psychiatric diagnostic evaluation with medical services is "an integrated biopsychosocial and medical assessment, including history (to include past, family, and social), psychiatric history, a complete mental status exam, other physical examination elements as indicated, establishment of a tentative diagnosis, and an evaluation of the patient's ability to respond to treatment." That definition is doing real work. It is the reason non-prescribing clinicians cannot bill it, and the reason a medical component has to show up somewhere in your note.
90792 is the initial psychiatric diagnostic evaluation with a medical component. That medical piece can be a physical exam element, a medication order, or the ordering and interpretation of labs — you need one, documented clearly, not all three.
AAPC's Codify code reference puts the same idea in plainer language: the provider performs a psychiatric evaluation aimed at a diagnosis, and "in addition to the diagnostic evaluation, he also renders some additional medical services." The American Psychiatric Association's CPT Primer draws the line even more directly, describing a split "between an initial evaluation with medical services done by a physician (90792) and an initial evaluation done by a non-physician (90791)."
In practice, that medical piece can be a physical exam element, a medication order, or the ordering and interpretation of labs. It does not have to be all three. CMS's guidance language, "other physical examination elements as indicated," gives you latitude here rather than a fixed checklist, which matters when you are documenting an evaluation for a patient who is stable on an existing medication and does not need a full physical exam that day.

Make CPT 90792 Documentation Easier to Get Right
Use this free checklist to confirm eligibility, capture the required medical-services component, support medical necessity, and reduce avoidable billing issues.
- Verify CPT 90792 eligibility before you bill
- Confirm your note includes the required documentation elements
- Identify common denial triggers and medical-necessity considerations
90791 vs. 90792: What Actually Separates Them
The two codes describe the same underlying encounter, a psychiatric diagnostic evaluation, but they split on one question: does this visit include a medical assessment.
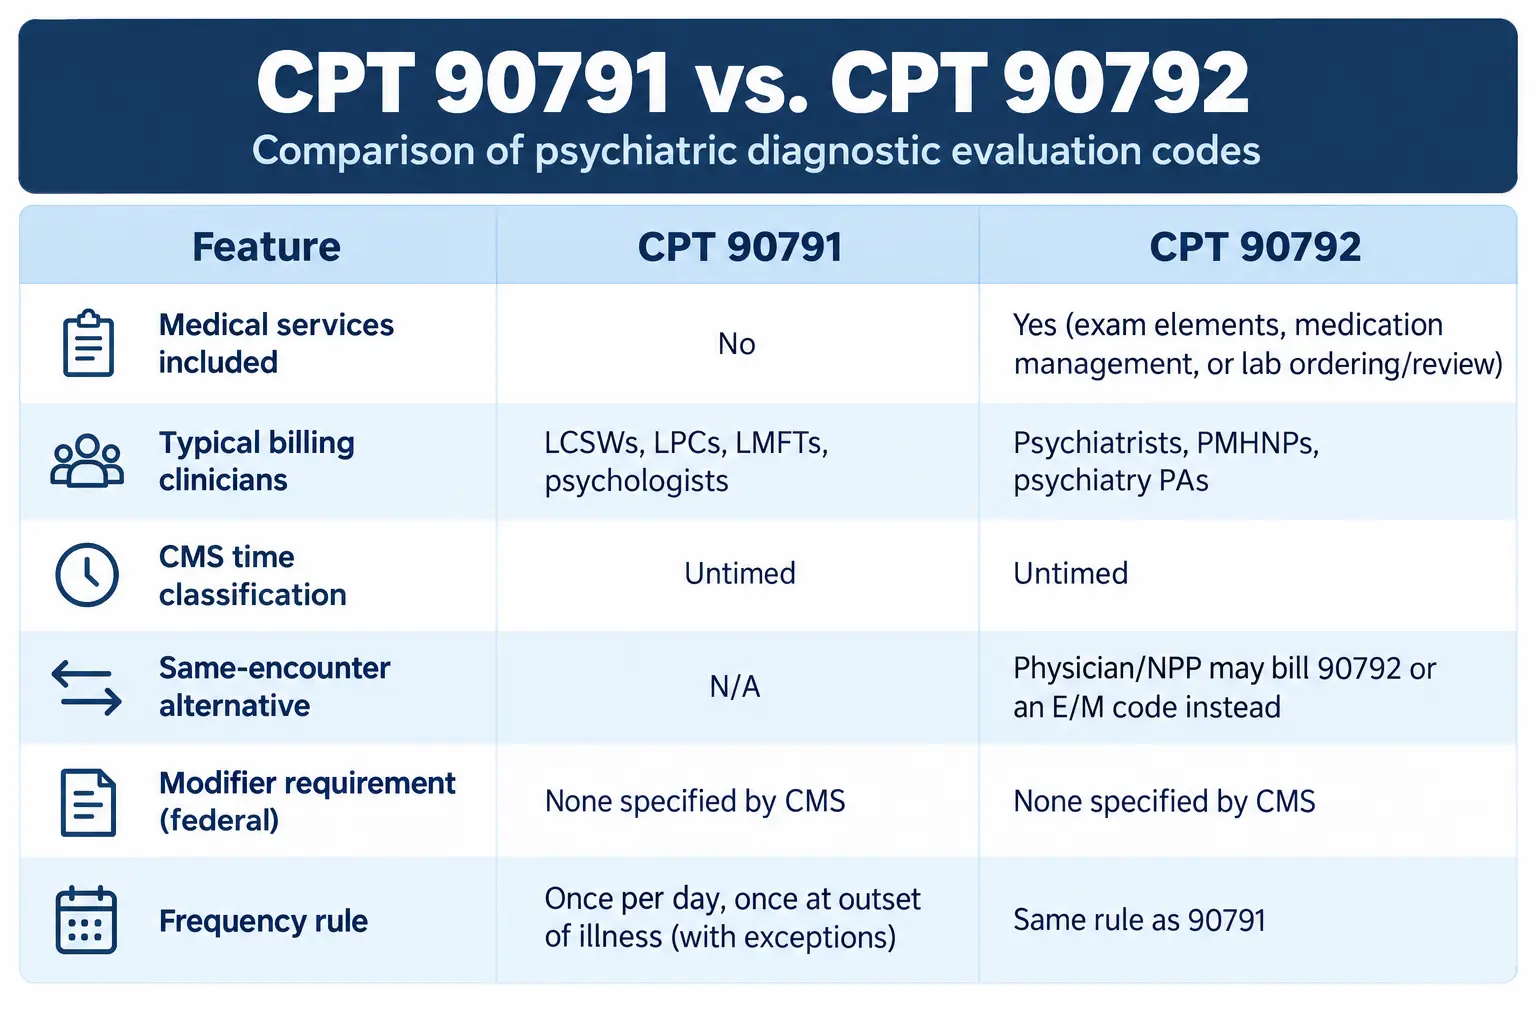
Noridian, a CMS Medicare Administrative Contractor, states the distinction plainly on its Mental Health billing page: 90791 is a psychiatric diagnostic evaluation "without medical services," while 90792 "adds medical assessment or physical exam piece." Who can bill which code follows from that split. The APA's CPT Primer notes that 90791 "in all likelihood will not be used by psychiatrists," since it was built for clinicians who cannot perform or order medical services, while 90792 fits psychiatrists, PMHNPs, and psychiatry PAs who build a medical component into the evaluation.
| Feature | CPT 90791 | CPT 90792 |
|---|---|---|
| Medical services included | No | Yes (exam elements, medication management, or lab ordering/review) |
| Typical billing clinicians | LCSWs, LPCs, LMFTs, psychologists | Psychiatrists, PMHNPs, psychiatry PAs |
| CMS time classification | Untimed | Untimed |
| Same-encounter alternative | N/A | Physician/NPP may bill 90792 or an E/M code instead |
| Modifier requirement (federal) | None specified by CMS | None specified by CMS |
| Frequency rule | Once per day, once at outset of illness (with exceptions) | Same rule as 90791 |
One nuance worth flagging for prescribers: CMS's LCD article notes that for an evaluation that does include a medical assessment, "the physician or non-physician practitioner (NPP) may use CPT code 90792 or an evaluation and management (E/M) code." You have a choice at that first visit, and which one you pick should depend on your documentation and your payer mix, not habit.
CMS's National Correct Coding Initiative (NCCI) Policy Manual confirms the two codes are mutually exclusive for a given encounter. You bill one or the other for a single evaluation, never both, and never alongside a same-day E/M code from the same provider.
Documentation Requirements for CPT Code 90792
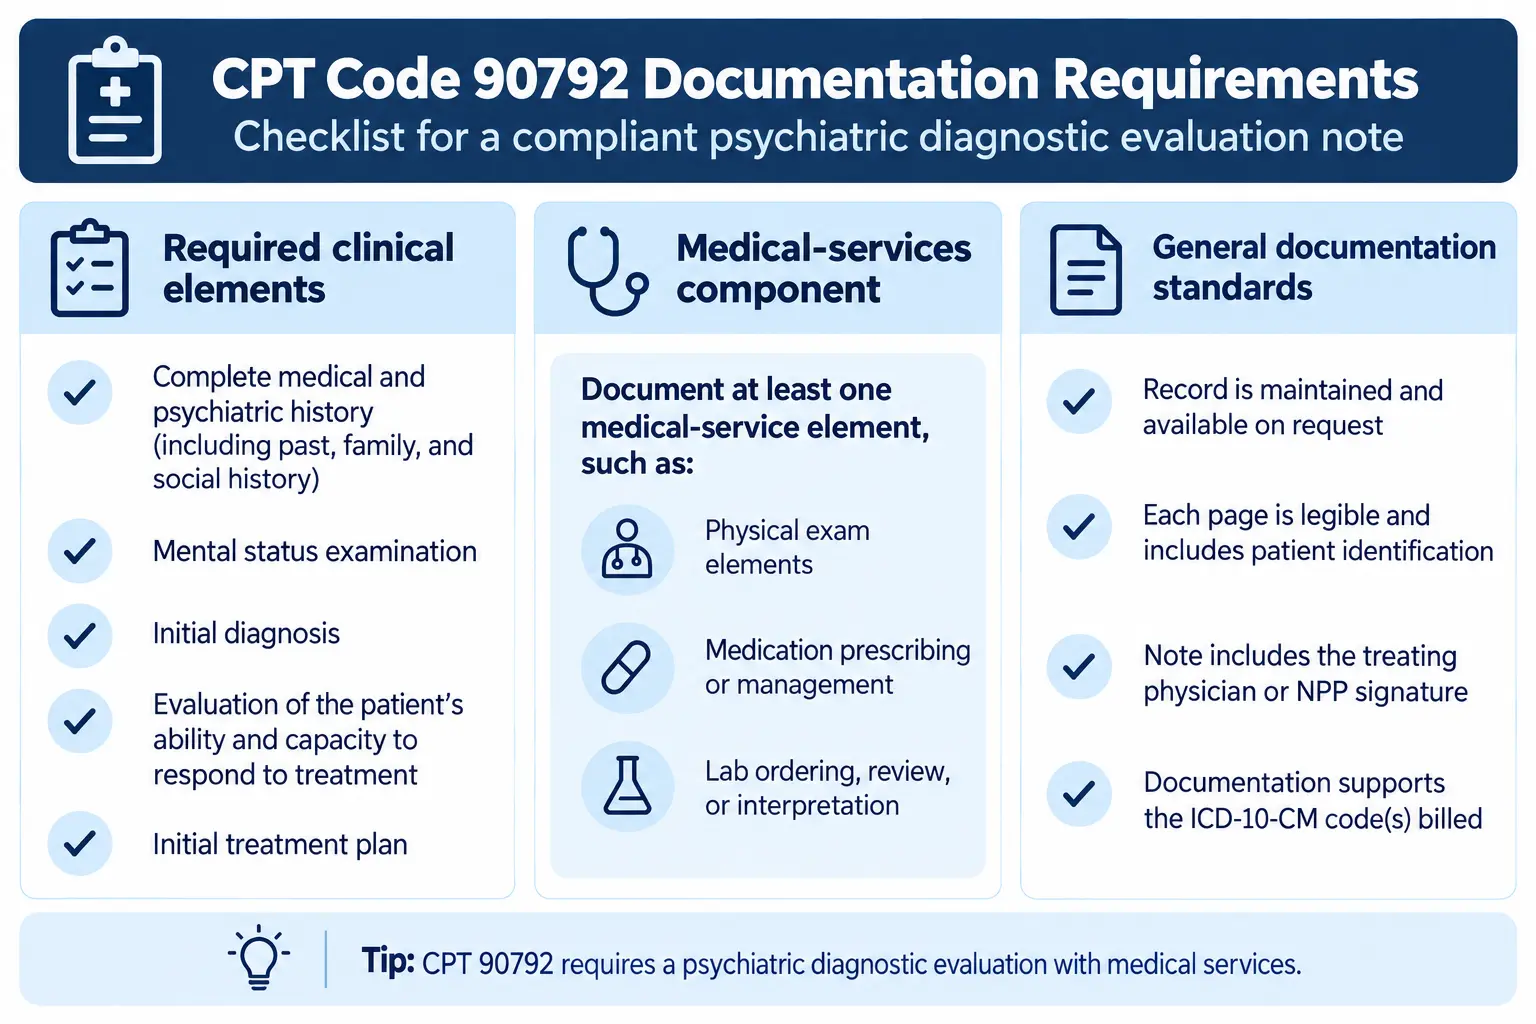
CMS's Outpatient Psychiatric Services fact sheet lists five required clinical elements for both 90791 and 90792:
- A complete medical and psychiatric history, including past, family, and social history
- A mental status examination
- Establishment of an initial diagnosis
- An evaluation of the patient's ability and capacity to respond to treatment
- An initial plan of treatment
Beyond those clinical elements, CMS's Billing and Coding Article A57520 sets four general record-keeping standards that apply regardless of specialty. The record must be maintained and available on request. Every page needs to be legible and carry patient identification. The note needs the legible signature of the treating physician or NPP. And the documentation has to support the ICD-10-CM code or codes billed on the claim.
The APA's CPT Primer adds detail on what "medical services" looks like in the note itself: chief complaint, history of present illness, a review of pertinent systems, family and psychosocial history, a complete mental status exam, and "any medical work such as the ordering and medical interpretation of laboratory or other diagnostic studies or the prescribing of medications."
One thing worth clarifying, since it trips up a lot of new prescribers: neither CMS nor the APA specifies a minimum word count or a required template structure. "Medical services" is satisfied by any one of physical exam elements, medication prescribing, or lab ordering and review. You don't need all three in a single note, you need one, documented clearly enough that a reviewer can find it.
Does CPT Code 90792 Have a Time Requirement?
No. CPT code 90792 is not a time-based code under CMS or CPT rules, and that distinction matters because it sits right next to codes that are. CMS's NCCI Policy Manual, Chapter 11, separates 90791 and 90792 from the psychotherapy codes explicitly, noting that "individual psychotherapy codes are time-based codes," a category the manual does not extend to the two diagnostic evaluation codes.
CMS's Billing and Coding Article A57520 reinforces the same split. It labels psychotherapy codes 90832 through 90838, plus the crisis codes 90839 and 90840, as time-based, and spells out their exact minute ranges. It includes no comparable time language anywhere for 90791 or 90792.
That said, you will run into practical time ranges if you search around, and it is worth knowing where they come from, because they conflict. TheraThink's billing guide states that a thorough 90792 evaluation typically "requires at minimum 60 minutes up to 120 minutes." PsychiatryBillers.com cites a narrower window of 45 to 90 minutes for the same code. These are clinical conventions from billing companies, not a CPT or CMS rule, and the roughly 45-minute gap between the two figures is a good reminder to treat them as rough guidance rather than a compliance standard. Document what the evaluation actually required. Don't clock-watch to hit a number that no regulator asked you to hit.
Document what the evaluation actually required. Don't clock-watch to hit a number that no regulator asked you to hit.
Does CPT 90792 Need a Modifier?
| Modifier / code | What it signals | Applies universally under CMS? |
|---|---|---|
| None (base code) | Standard psychiatric diagnostic evaluation with medical services | Yes, this is the default |
| 90785 (add-on code) | Interactive complexity, used when communication is complicated by a third party or developmental factors | Yes, but only when documented and only if the patient can communicate by some means |
| 95 (telehealth) | Service delivered via telehealth | Payer- and state-dependent, not a 90792-specific federal rule |
| AF, AH, AJ (license-level) | Physician, psychologist, or clinical social worker designation | No, these are state Medicaid or commercial-payer conventions |
At the federal Medicare level, CMS does not require a modifier tied specifically to 90792. Its own Billing and Coding Article A57520 lists the "CPT/HCPCS Modifiers" field as "N/A" for this code family, which is about as direct a confirmation as you'll get that there is no federal modifier mandate here.
The one true add-on code associated with 90792 is 90785, interactive complexity, billed when communication during the evaluation is complicated by a third party, developmental factors, or similar circumstances. The same CMS article is specific about a limit here too: "if a patient is unable to communicate by any means, the interactive complexity CPT code 90785 should not be billed."
Where modifiers do show up is at the state Medicaid level, and they vary by state. Ohio Medicaid's CareSource behavioral health billing guide, for example, lists a full set of license-level modifiers for 90791 (HE, AM, SA, UC, UD, AH, AJ, and several state-specific U-series codes) but a narrower list for 90792 (HE, AM, SA, UC, UD), reflecting that 90792 is restricted to physician, NP, and PA-level billers.
You may also come across billing blogs claiming that CMS universally requires "modifier AF for psychiatrists, AH for psychologists, AJ for social workers" on 90792. That claim does not hold up. AAPC's own coding forum disputes it directly, with practitioner comments clarifying that AJ specifically denotes a clinical social worker and functions as a state Medicaid convention, "not required for commercial insurances." Check your own state Medicaid manual and your commercial payer contracts before assuming a modifier applies. Don't assume a national rule that doesn't exist.
Establishing Medical Necessity: ICD-10 Pairing
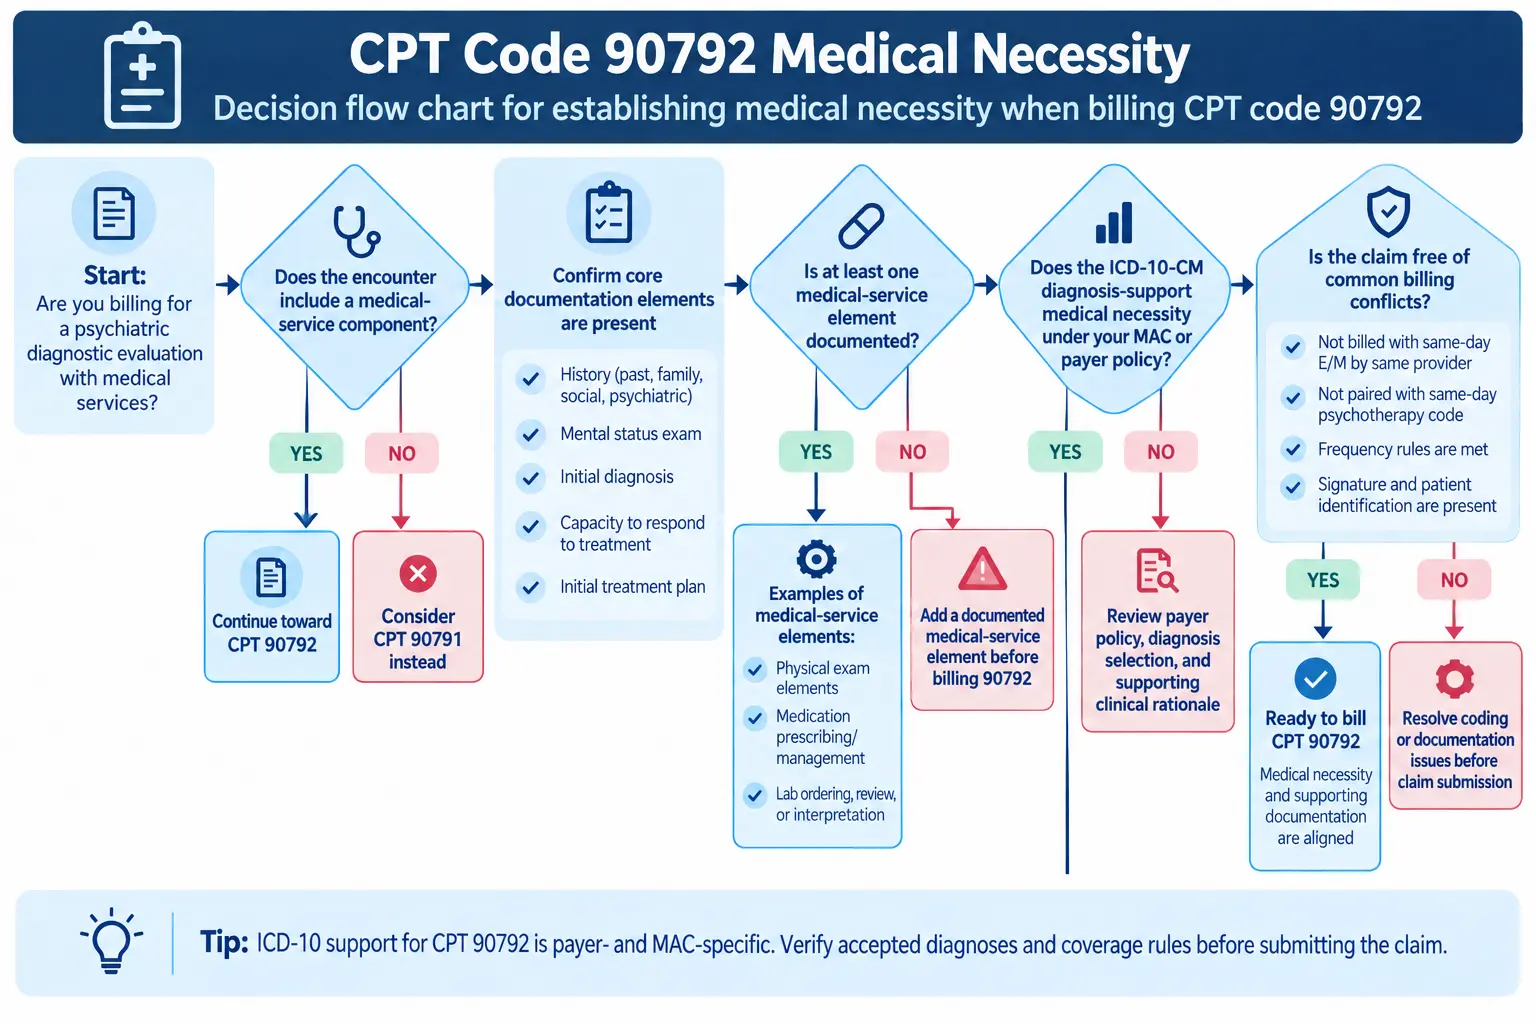
Medical necessity for 90792 is not just a diagnosis code exercise, but the ICD-10 code you attach to the claim is where most reviewers start. CMS's Billing and Coding Article A57520 publishes an explicit list of ICD-10-CM codes that support medical necessity for the whole diagnostic and treatment code family that includes 90792. The list spans several major categories:
- Dementia and cognitive disorders (F01 through F03, and G30 for Alzheimer's disease)
- Substance use disorders (F10 through F19)
- Psychotic disorders (F20 through F25)
- Mood disorders (F30 through F34)
- Anxiety, obsessive-compulsive, and trauma-related disorders (F40 through F45)
- Personality disorders (F60)
- Childhood and developmental disorders (F80 through F98)
- One administrative code, Z01.818, for a preprocedural examination encounter
A claim coded with a diagnosis outside that list falls, per the same article, under codes that "DO NOT Support Medical Necessity" for that MAC's policy. That phrase is worth sitting with. It doesn't mean the diagnosis is wrong. It means the claim may not clear review without additional documentation of medical necessity.
Here's the part that catches clinicians who move between states or switch MACs: this list is specific to First Coast Service Options' jurisdiction, which covers Florida, Puerto Rico, and the Virgin Islands. Other Medicare Administrative Contractors, including Noridian and Novitas, publish their own versions of this article, and the accepted list can vary by MAC. Treat it as a MAC-specific policy, not a single nationwide roster, and pull the current version for your own jurisdiction before you build a template around it.
Underneath all of this sits a broader standard that CMS's Outpatient Psychiatric Services fact sheet points back to: Section 1862(a)(1)(A) of the Social Security Act, which requires that services billed to Medicare be "reasonable and necessary." The ICD-10 list is a tool for demonstrating that standard, not a replacement for it.
How Often Can You Bill 90792?
CMS's Outpatient Psychiatric Services fact sheet sets the baseline rule in one line: 90792 is "reported once per day and NOT on the same day as an E/M service performed by the same individual for the same patient," and it is "covered once at the outset of an illness or suspected illness," with exceptions carved out in the relevant LCD.
The APA's CPT Primer adds Medicare-specific detail that isn't in the CMS fact sheet itself. Medicare pays for only one 90792 per year for institutionalized patients "unless medical necessity can be established for others," and it allows the code to be used again "if there has been an absence of service for a three-year period." Repeat billing on subsequent days is allowed too, when there is documented medical necessity for an extended evaluation, the Primer gives the example of a child evaluation that requires seeing the child and the parents both together and separately.
CMS's NCCI Policy Manual backs the same-day restriction from the claims-integrity side. It states that 90791 and 90792 "are not separately reportable with individual, group, family, crisis, or other psychotherapy codes for the same date of service," and that E/M codes "shall not be reported with either of these diagnostic psychiatric codes." Build your scheduling and your billing workflow around that rule specifically. A same-day med check and diagnostic evaluation for the same patient is a pairing that will get flagged.
What Does CPT Code 90792 Pay?
This is the section where you should trust CMS over any blog, including this one. CMS's Physician Fee Schedule is the authoritative source for the current national and locality-adjusted rate for 90792, and its Look-Up Tool (available at cms.gov/medicare/payment/fee-schedules/physician) is the place to confirm your own number. It's an interactive, locality-driven search tool rather than a static page, so we're not going to reprint a single dollar figure here and call it the CMS rate. Run your own ZIP code or locality through the tool before you build a fee schedule expectation around any number you read online.
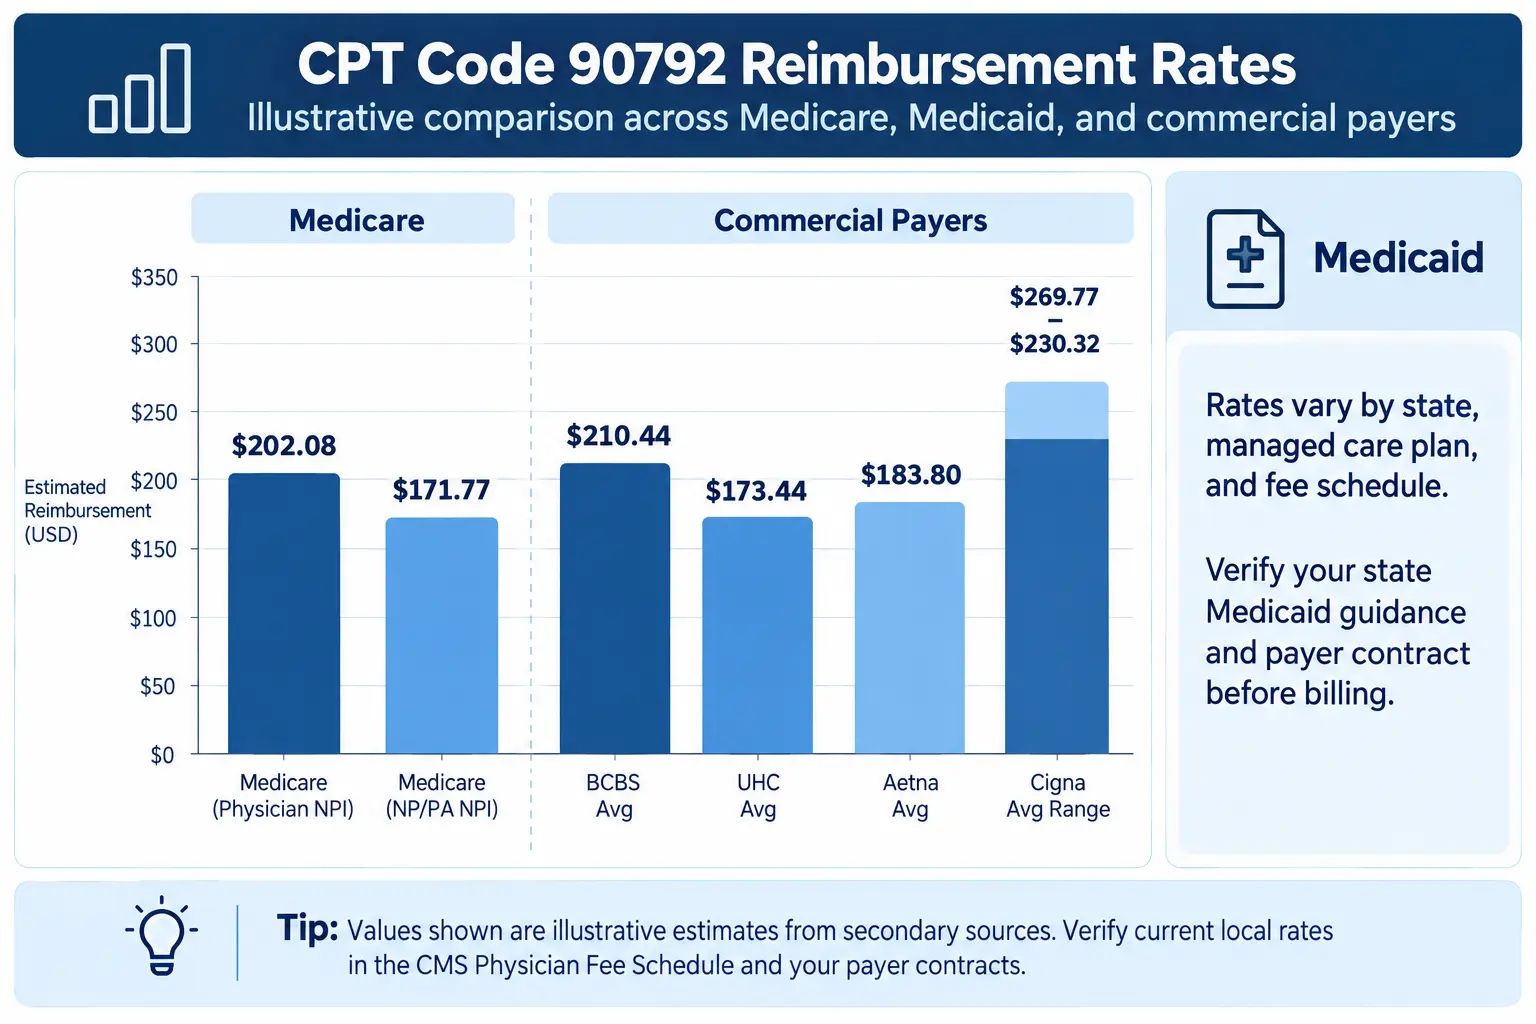
That caution matters because third-party estimates disagree with each other, sometimes by a wide margin. TheraThink's billing guide tracks the Medicare non-facility national rate for 90792 falling from $218.90 in 2022 to $190.57 in 2024 and 2025, with an increase it lists at $202.08 for 2026. MedSole RCM's billing guide cites the same 2026 figure and adds that a psychiatric nurse practitioner billing under her own NPI typically receives about 85% of the physician rate, consistent with Medicare's general non-physician practitioner payment policy, which would put that figure around $171.77.
| Payer type | Illustrative estimate | Source (not CMS-confirmed) |
|---|---|---|
| Medicare, physician NPI (2026 est.) | ~$202.08 | TheraThink, MedSole RCM |
| Medicare, NP/PA NPI (85% policy) | ~$171.77 | MedSole RCM |
| BCBS (national average) | ~$210.44 | PayerPrice |
| UHC (national average) | ~$173.44 | PayerPrice |
| Aetna (national average) | ~$183.80 | PayerPrice |
| Cigna | ~$230.32 (PayerPrice) vs. ~$269.77 (MedSole RCM) | Conflicting, unresolved |
Commercial payer figures show real disagreement between sources. PayerPrice lists Cigna's national average at $230.32, while MedSole RCM's guide cites $269.77 for the same code, a roughly $40 gap between two secondary sources, neither of which is a payer-published fee schedule. Treat every number in that table as directional. Call your payer's provider line or check your own contracted rate before you count on any figure here.
The Real Cost of Documentation Time
Everything above is a compliance conversation. There's a second conversation underneath it, about how much of your day a compliant 90792 note actually takes, and what that time costs you.
According to ICANotes' 2026 survey of 416 licensed behavioral health professionals, distributed through a press release covered by natlawreview.com, 40% of clinicians spend six or more hours a week on documentation and administrative tasks, roughly a full lost workday every week. The same survey found that 49% of respondents said they could take on more patients if documentation consumed less of their time. Dr. October Boyles, ICANotes' Chief Clinical Officer, was cited in that release discussing the finding.
That's a behavioral-health-specific number, and it's worth noting because a lot of the "documentation burden" statistics that circulate online don't hold up to scrutiny once you check the source. A 2021 scoping review published in JAMIA, which screened 3,482 studies on clinical documentation burden, found the concept itself is "ill-defined and inconsistently measured" across the research literature. That's a reasonable caution against treating any single "X% of the day" claim as settled fact, including ones you might have seen elsewhere. What holds up is the ICANotes survey figure above, because it's scoped specifically to behavioral health clinicians and traceable to a named, dated source.
For a 90792 note specifically, that documentation burden concentrates in exactly the areas covered above: pulling a complete history, structuring the mental status exam, and making sure the ICD-10 code and treatment plan line up in a way that survives a payer review. None of that is optional, and none of it should eat your evening.
How ICANotes Supports a Compliant 90792 Note
Select structured findings
The menu-driven psychiatric diagnostic evaluation template lets you select structured findings rather than free-typing a narrative note from scratch.
Add scales inside the chart
Built-in access to more than 100 DSM-5-aligned rating scales, PHQ-9 and GAD-7 among them, supports the diagnostic and treatment-response elements CMS asks for.
Handle the medical component
E-prescribing with EPCS and PDMP checks runs in the same workflow, so medication ordering doesn't require switching systems.
Produce an audit-ready note
The template still produces a readable, audit-ready narrative that maps to the ICD-10 and medical-necessity requirements.
This is where a purpose-built behavioral health EHR earns its place in the conversation, not as a shortcut around the requirements above, but as a way to meet them without retyping the same structure from a blank screen every time.
ICANotes builds its psychiatric diagnostic evaluation template around the same clinical elements CMS lists for 90792: history, mental status exam, diagnosis, treatment plan, and the medical-services component that separates 90792 from 90791. The template is menu-driven, so you're selecting structured findings rather than free-typing a narrative note from scratch, and it still produces a readable, audit-ready narrative on the other end. Built-in access to more than 100 DSM-5-aligned rating scales, PHQ-9 and GAD-7 among them, supports the diagnostic and treatment-response elements CMS asks for directly inside the same chart.
For prescribers specifically, e-prescribing with EPCS and PDMP checks runs in the same workflow as the evaluation itself, so the medical-services component of a 90792 note, medication ordering included, doesn't require switching systems. And because the platform is built specifically for behavioral health rather than adapted from a general medical EHR, the documentation structure maps to the ICD-10 and medical-necessity requirements covered earlier in this piece, instead of asking you to bend a general medical template into a psychiatric shape.
None of that changes the underlying CMS rules. It changes how much of your evening they cost you.
Write audit-ready 90792 notes in less time
Try ICANotes free and see how a purpose-built behavioral health EHR structures the psychiatric diagnostic evaluation around the exact CMS elements 90792 requires.
- Menu-driven psychiatric diagnostic evaluation template
- 100+ DSM-5-aligned scales like PHQ-9 and GAD-7
- EPCS e-prescribing and PDMP in one workflow
- ICD-10 mapping that supports medical necessity
See how ICANotes can support your clinical workflow. Start your free 30-day trial, no credit card required.
Start Your Free 30-Day Trial
Frequently Asked Questions
What is required to bill 90792?
Does 90792 have a time requirement?
What is the difference between CPT 90791 and 90792?
What are the documentation requirements for CPT code 90792?
Does CPT 90792 need a modifier?
How often can 90792 be billed?
How is a diagnostic evaluation different from a routine intake assessment?
References
- CMS, Local Coverage Determination L33252, Medicare Coverage Database: https://www.cms.gov/medicare-coverage-database/view/lcd.aspx?LCDId=33252&CptHcpcsCode=90792
- CMS, Billing and Coding Article A57520: https://www.cms.gov/medicare-coverage-database/view/article.aspx?articleId=57520&LCDId=33252&DocID=L33252
- CMS, Outpatient Psychiatric Services Fact Sheet: https://downloads.cms.gov/medicare-coverage-database/lcd_attachments/31887_33/Outpatient_Psych_Fact_Sheet09.18.14.pdf
- CMS, NCCI Policy Manual, Chapter 11 (2026): https://www.cms.gov/files/document/11-chapter11a-ncci-medicare-policy-manual-2026-final.pdf
- CMS, Physician Fee Schedule Look-Up Tool: https://www.cms.gov/medicare/payment/fee-schedules/physician
- American Psychiatric Association, CPT Primer for Psychiatrists: https://www.psychiatry.org/File%20Library/Psychiatrists/Practice/Practice-Management/Coding-Reimbursement-Medicare-Medicaid/Coding-Reimbursement/cpt-primer-for-psychiatrists.pdf
- AAPC, Codify CPT Code 90792: https://www.aapc.com/codes/cpt-codes/90792
- AAPC coding forum, Modifier AJ discussion: https://www.aapc.com/discuss/threads/modifier-aj.137161
- Noridian Healthcare Solutions, Mental Health billing page: https://med.noridianmedicare.com/web/jeb/specialties/mental-health
- CareSource / Ohio Medicaid, Hospital Behavioral Health Billing Guide: https://www.caresource.com/documents/oh-sp-0075-hospital-behavioral-health-billing-guide/
- TheraThink, CPT Code 90792 billing guide: https://therathink.com/cpt-code-90792/
- PsychiatryBillers.com, CPT Code 90792 billing guide: https://www.psychiatrybillers.com/resources/codes/cpt-code-90792-psychiatric-evaluation-billing-guide
- MedSole RCM, CPT Code 90792 billing guide: https://medsolercm.com/blog/cpt-code-90792
- PayerPrice, CPT 90792 fee schedule: https://payerprice.com/rates/90792-CPT-fee-schedule
- ICANotes Clinician Survey 2026, via National Law Review: https://natlawreview.com/press-releases/new-study-49-behavioral-health-providers-could-take-more-patients-if
- JAMIA, "Measurement of clinical documentation burden among physicians and nurses using electronic health records" (2021): https://academic.oup.com/jamia/article/28/5/998/6090156
Dr. October Boyles
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.




