
CPT Codes 90834 vs. 90837: The Definitive 2026 Billing Guide
Master the exact time thresholds, documentation payers expect, and how to keep every billed psychotherapy session audit-ready.


CPT codes 90834 and 90837 are the two standard codes for individual psychotherapy — and the primary distinction between them comes down to the actual face-to-face time you spend with your client. Bill the wrong one, or fail to document it correctly, and you risk a rejected claim, a payer audit, or a post-payment clawback months later. This guide breaks down the exact time thresholds, the documentation payers expect to see, and how to keep every session audit-ready.
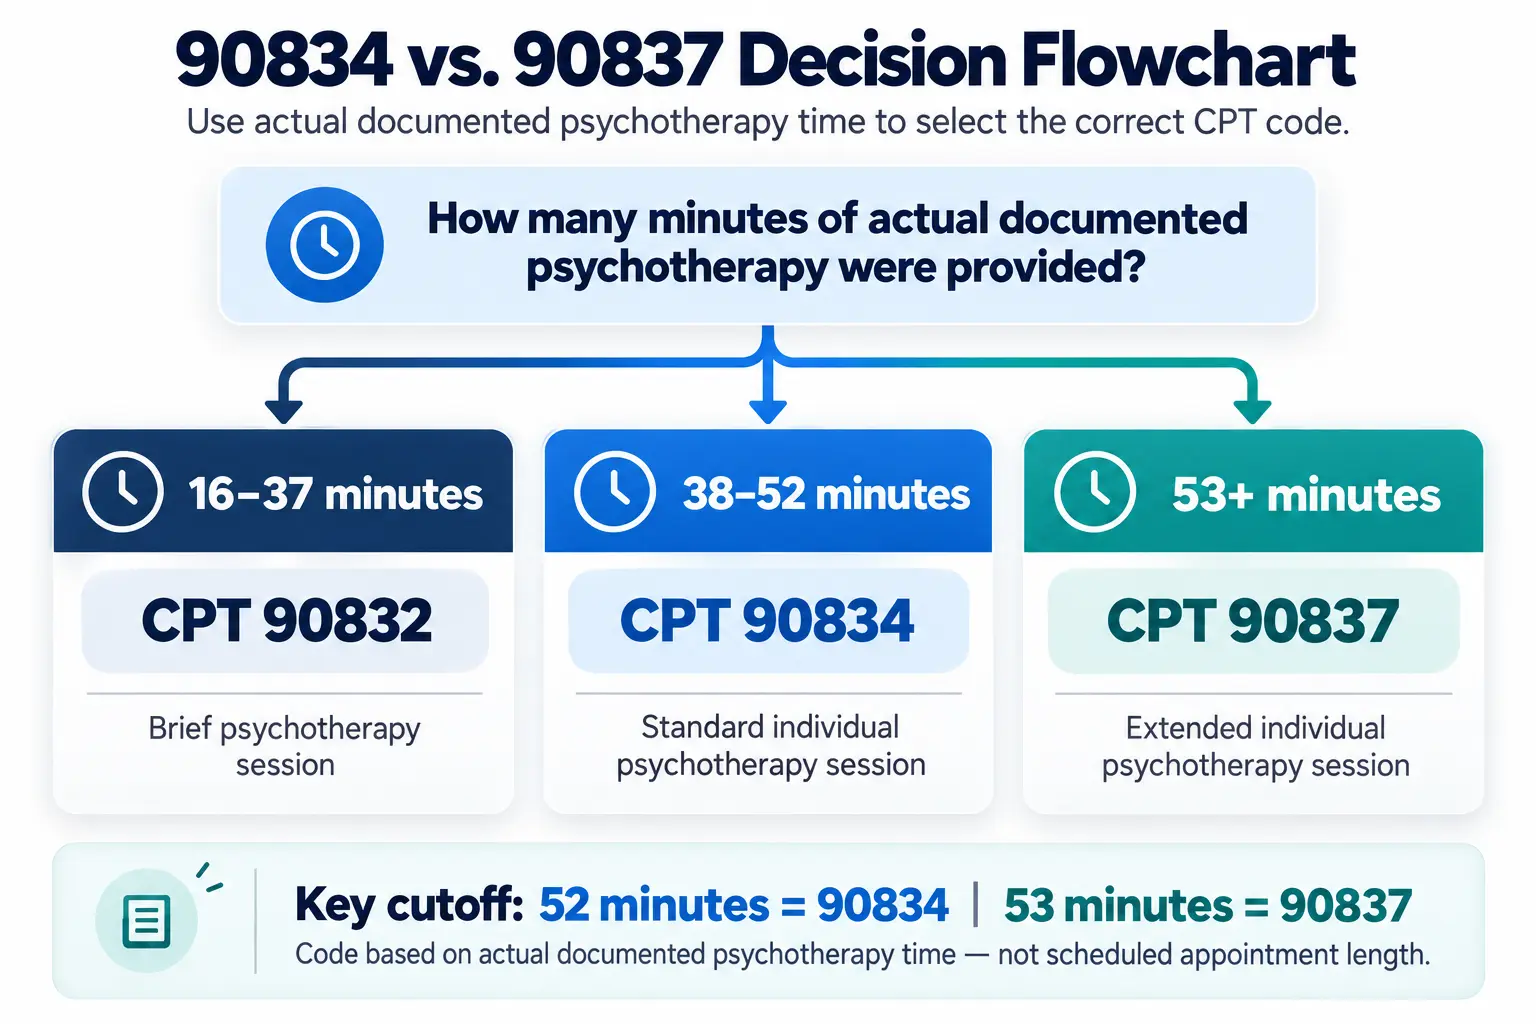
CPT code 90834 is used for 38–52 minutes of individual psychotherapy, while CPT code 90837 is used for 53 minutes or more. The correct code is based on the actual psychotherapy time documented, not the scheduled appointment length. A 50-minute therapy session should therefore be billed as 90834, not 90837.
Key takeaways
- CPT codes 90834 and 90837 are both individual psychotherapy codes. Per the AMA, the primary factor that separates them is face-to-face time with the client — not diagnosis, complexity, or treatment modality.
- CPT code 90834 covers 38–52 minutes of psychotherapy, often called “the standard therapy hour.” CPT code 90837 covers 53 minutes or more.
- 90837 is audited far more frequently than 90834 because it reimburses at a higher rate and is easy to bill by default instead of by clinical necessity.
- Defensible 90837 documentation requires start/stop times (or total face-to-face time), a clinical rationale for the extended session, and a treatment plan that supports the additional time.
- A 50-minute session bills as 90834, not 90837 — rounding a session up “because it felt long” is one of the most common, and most avoidable, coding errors.
Introduction
Every clinician who bills insurance has, at some point, stared at a session note trying to decide whether it was a 90834 or a 90837. It seems like it should be simple — 45 minutes versus 60 minutes — but the reality is messier. Sessions run long because a client is in crisis. They run short because a client cancels the last ten minutes with a phone call. Documentation gets copied and pasted from note to note until nobody remembers what the actual clock said.
That ambiguity is exactly why CPT 90837 has become one of the most heavily scrutinized codes in behavioral health billing. It pays more than 90834, which makes it an attractive default — and that same fact makes it a magnet for payer audits. Clinicians, group practice owners, and billers who don’t have a clean, repeatable way to confirm session length and document medical necessity are the ones who end up fighting denied claims, or worse, repaying money on services they already provided.
This guide lays out the CPT 90834 and 90837 time ranges the AMA has defined, gives you a side-by-side reference table you can use at the point of care, walks through exactly what payers look for when they audit a 90837 claim, and answers the most common billing questions clinicians and practice managers ask about these two codes. For a refresher on psychotherapy coding fundamentals, see our CPT Code Basics Guide.
What Are CPT Codes 90834 and 90837?
CPT codes 90834 and 90837 are both billed for individual psychotherapy — a face-to-face session between a licensed clinician and a client focused on treating a diagnosed mental health condition. Both codes can be used by psychiatrists, psychologists, LCSWs, LPCs, LMFTs, and other licensed behavioral health clinicians, and both can be billed alongside an evaluation and management (E/M) service on the same day when performed by a prescribing provider, using the appropriate add-on modifier. Both codes are time-based, which means the correct code depends on the actual, documented psychotherapy time rather than the length of the scheduled appointment.
What is CPT Code 90834?
CPT code 90834 is used for individual psychotherapy lasting 38 to 52 minutes. Its standard CPT description is “psychotherapy, 45 minutes with patient,” but the session does not need to last exactly 45 minutes to qualify.
CPT 90834 is commonly associated with the standard therapy hour. For example, if a clinician schedules a 45- or 50-minute appointment and documents 40, 45, or 50 minutes of actual psychotherapy, the session falls within the 90834 time range.
The code does not require a particular treatment modality. CBT, DBT, psychodynamic therapy, EMDR, and other psychotherapy approaches may be billed under 90834 when the documented psychotherapy time falls within the appropriate range.
What is CPT Code 90837?
CPT code 90837 is used for individual psychotherapy lasting 53 minutes or longer. Its standard CPT description is “psychotherapy, 60 minutes with patient,” but the code applies beginning at the 53-minute threshold rather than requiring exactly 60 minutes.
CPT 90837 is used for longer psychotherapy sessions. Extended sessions may occur during complex trauma work, EMDR, crisis-related treatment, or other situations in which additional psychotherapy time is clinically appropriate.
As with 90834, the therapeutic technique does not determine whether 90837 should be billed. The primary coding distinction is the actual psychotherapy time documented for the session.
90834 vs. 90837: Time Range Comparison Table
This is the single most-searched question about these two codes, and it’s worth memorizing: the CPT manual doesn’t require an exact 45 or 60 minutes. Instead, the American Medical Association (AMA) sets a time range for each code, and CMS and most commercial payers follow the same rule — you bill whichever code’s range contains your documented session time.
90834 vs. 90837 at a Glance
| CPT 90834 | CPT 90837 | |
|---|---|---|
| Psychotherapy time | 38–52 minutes | 53+ minutes |
| Common descriptor | 45-minute psychotherapy | 60-minute psychotherapy |
| 50-minute session? | Yes | No |
| Requires documentation of actual time? | Yes | Yes |
| CPT Code | Standard Description | Actual Time Range Required | Primary Clinical Use Case |
|---|---|---|---|
| 90832 | 30 minutes of psychotherapy | 16–37 minutes | Brief check-ins or targeted crisis interventions |
| 90834 | 45 minutes of psychotherapy | 38–52 minutes | The standard therapy hour |
| 90837 | 60 minutes of psychotherapy | 53+ minutes | Longer individual psychotherapy sessions meeting the 53+ minute threshold* |
* Longer sessions may occur during trauma treatment, EMDR, crisis-related work, or other clinically appropriate circumstances.
A few details worth calling out about this table:
- The 90834 time range (38–52 minutes) is wide enough to cover most standard sessions, even when a session runs a few minutes short or long of the traditional “50-minute hour.”
- The 90837 time range begins at 53 minutes with no stated upper limit in the CPT manual itself, though individual payers may flag unusually long sessions (90+ minutes) for review.
- There’s no code between 90834 and 90837 — a 52-minute session and a 53-minute session are one minute apart on the clock, but one CPT code apart on the claim. That single minute is exactly why start and stop time documentation matters so much.

CPT Code Examples by Session Length
Here are a few common examples of how documented psychotherapy time maps to CPT codes:
- 37 minutes: CPT 90832
- 38 minutes: CPT 90834
- 45 minutes: CPT 90834
- 50 minutes: CPT 90834
- 52 minutes: CPT 90834
- 53 minutes: CPT 90837
- 60 minutes: CPT 90837
The key cutoff is between 52 and 53 minutes. A 52-minute psychotherapy session is billed as 90834, while a 53-minute session meets the time threshold for 90837.

Download the Free CPT 90834 vs. 90837 Documentation Checklist
Take the guesswork out of psychotherapy coding and documentation. This practical checklist helps you quickly confirm the correct time threshold, document the elements that support your claim, and identify common issues that can lead to denials or payer review. Use it to:
- Verify whether a session meets the 90834 or 90837 time requirement
- Confirm the documentation elements your note should include
- Support the clinical rationale for extended sessions
- Avoid common CPT 90837 denial triggers
- Keep a quick-reference tool on hand for internal documentation reviews
When Should You Use CPT 90834?
Use CPT 90834 when the documented psychotherapy time is between 38 and 52 minutes. It is commonly used for standard individual therapy sessions and applies based on the actual psychotherapy time provided, not the length of the appointment scheduled on the calendar.
For example, a session lasting 40, 45, 50, or 52 minutes falls within the CPT 90834 time range. A 50-minute session should still be billed as 90834, even if the appointment was scheduled for an hour. CPT 90837 does not apply until the documented psychotherapy time reaches 53 minutes.
CPT 90834 may be used for a variety of psychotherapy approaches, including CBT, DBT, psychodynamic therapy, EMDR, and other modalities. The treatment method itself does not determine the code; the primary coding distinction is the amount of psychotherapy time documented for the session.
Clinicians should document the actual psychotherapy time along with the standard elements of the session note, including the presenting concerns, interventions used, client response, and plan for continued treatment. Consistent time documentation helps support accurate coding and reduces the risk of billing a higher-level psychotherapy code when the time threshold was not met.
When Should You Use CPT 90837?
Use CPT 90837 when the documented psychotherapy time is 53 minutes or longer. The code is intended for longer individual psychotherapy sessions and should be selected based on the actual time spent providing psychotherapy, not the length of the appointment scheduled on the calendar.
For example, a psychotherapy session lasting 53, 60, or 65 minutes may fall within the CPT 90837 time range. A 52-minute session does not qualify and should be billed as CPT 90834 instead.
CPT 90837 may be appropriate when a client’s clinical needs require a longer session, such as during complex trauma work, EMDR processing, acute distress, crisis-related treatment, or another situation in which additional psychotherapy time is clinically appropriate. The treatment modality or diagnosis alone does not determine whether 90837 should be used; the documented psychotherapy time must meet the 53-minute threshold.
When billing 90837, the clinical note should clearly support the service provided. Documentation should include the actual psychotherapy time and should reflect the interventions performed, the client’s response, and how the session supported the treatment plan. When the extended length of the session is clinically significant, documenting the rationale for the additional time can help support the claim during payer review.
How Do You Justify CPT 90837?
To justify CPT 90837, documentation should show that at least 53 minutes of psychotherapy were provided and explain why the extended session was clinically appropriate. The note should connect the additional time to the client’s symptoms, treatment goals, interventions, risk level, or other clinical needs.
Strong 90837 documentation should include:
- Actual psychotherapy time: Record the session start and stop times or the total face-to-face psychotherapy time. A session must reach at least 53 minutes to qualify for 90837.
- Clinical rationale for the extended session: Briefly explain why additional time was needed. Examples may include crisis stabilization, complex trauma processing, EMDR work that could not be safely interrupted, significant risk assessment, or another clinically appropriate reason.
- Treatment plan alignment: Show how the extended session supported one or more documented treatment goals.
- Interventions and client response: Document the therapeutic interventions used and how the client responded during the session.
- Risk assessment, when relevant: If safety concerns contributed to the extended session, document the assessment and interventions performed.
- Consistency between the note and the claim: The documentation should support both the time billed and the clinical circumstances of that specific session.
Using 90837 should not depend on diagnosis or treatment modality alone. The key requirements are that the documented psychotherapy time meets the 53-minute threshold and that the record supports the service provided.
CPT 90837 Documentation Requirements and the “Audit Trap”
Because 90837 generally reimburses more than 90834, frequent use may attract greater payer utilization review and documentation scrutiny. CPT 90837 gets audited more frequently because it reimburses at a meaningfully higher rate than 90834, which creates an incentive — even an unconscious one — to round every session up. Payers know this, and their utilization review teams specifically flag providers whose billing patterns show 90837 used for the overwhelming majority of sessions, rather than as the exception for clinically complex cases.
What Payers Look For When They Audit a 90837 Claim
When a commercial payer, Medicare Administrative Contractor, or Medicaid managed care plan reviews a 90837 claim, they’re generally checking for four things:
Start and stop times, or total face-to-face time
“No time documented” is one of the fastest ways to have a 90837 claim denied or recouped. The note needs to show the actual minutes spent with the client present — not the scheduled appointment length.
A clinical rationale for the extended session
The note should explain why this particular session needed more than 45 minutes — active suicidal ideation requiring a full risk assessment, EMDR processing that couldn’t be safely interrupted, a session that included family involvement, or acute crisis stabilization. “Client wanted to talk longer” isn’t a clinical justification a reviewer will accept.
Treatment plan alignment
The extended time should connect back to the client’s documented treatment goals — not read as a stand-alone, disconnected note.
A billing pattern that makes clinical sense
If every single client, regardless of diagnosis or acuity, is billed 90837 every single week, that pattern itself is a red flag, independent of any one note’s quality.
| What reviewers look for | What documentation should show |
|---|---|
| Session time | Start/stop time or total psychotherapy minutes |
| Medical necessity | Why the extended session was clinically needed |
| Treatment-plan alignment | How the work supported an identified treatment goal |
| Billing pattern | 90837 usage consistent with the patient's clinical needs |

What CPT Code Should You Use for a 50-Minute Therapy Session?
A 50-minute psychotherapy session should be billed with CPT code 90834, because 90834 covers 38–52 minutes. CPT 90837 does not begin until 53 minutes.
Why a 50-Minute Session Isn't a 90837
This is worth stating plainly because it’s one of the most common documentation errors: a session that runs 50 minutes is a 90834, not a 90837. The 90837 time range doesn’t begin until 53 minutes. Clinicians sometimes round a 48- or 50-minute session up to the nearest “hour” out of habit, but that rounding is exactly the kind of pattern that shows up in a payer’s data analytics and triggers a chart request. When in doubt, the documented clock time — not the appointment length, and not a mental estimate — should determine the code.
Building an Audit-Ready Habit
The clinicians who avoid 90837 denials aren’t the ones who never bill it — they’re the ones who document consistently every time they do. That means recording start and stop times as a matter of routine, writing one or two sentences of clinical rationale specific to that session, and making sure the note reflects genuine medical necessity rather than a template phrase reused across every chart. Our Billing Pitfalls Article covers several other common denial patterns worth reviewing alongside this one.
How to Document and Bill CPT Code 90837 Correctly
Use this sequence for every extended session, whether you bill 90837 occasionally or regularly:
- Record the actual start and stop time of the session, not the scheduled block. If your EHR timestamps sessions automatically, confirm the timer reflects face-to-face time with the client present, not the full time the chart was open.
- Confirm the total time falls at 53 minutes or more. If it’s 52 minutes or under, code the session 90834 instead — don’t round up.
- Document the clinical rationale for the extended length in a sentence or two: what was happening in the session that required more than the standard hour (crisis stabilization, EMDR reprocessing, complex trauma work, a significant clinical event).
- Connect the session back to the treatment plan — note how the extended time supported a specific, documented treatment goal.
- Complete the standard note elements you’d include in any psychotherapy note: presenting concerns, interventions used, client response, risk assessment where relevant, and plan for the next session.
- Select CPT 90837 on the claim, along with the appropriate ICD-10 diagnosis code, and submit with your standard modifiers (for example, telehealth modifier 95, if applicable).
- Keep the note consistent with your billing pattern. If a payer requests records, your documentation should support that 90837 was the exception used for specific clinical reasons — not the default for every client.
Example of CPT 90837 Documentation
Example of CPT 90837 Documentation
2:02 p.m.–3:00 p.m. (58 minutes)
Extended psychotherapy time was required to address an acute increase in trauma-related symptoms and complete grounding and stabilization interventions before concluding the session. Interventions were consistent with the client's treatment-plan goal of reducing trauma-related distress.
Telehealth Documentation for 90834 and 90837
Both 90834 and 90837 are billable via telehealth, and the same time-based rules apply whether the session happens in person or over video. What changes for telehealth is the additional documentation payers expect: the platform used, confirmation that both clinician and client were in an appropriate, private setting, the client’s location (relevant for state licensure and payer telehealth policy), and the correct telehealth modifier and place-of-service code for that specific payer.
That extra layer is where telehealth claims most often go wrong. Place of service is the first piece: POS 10 identifies a session delivered while the client was at home, and POS 02 applies when the client was anywhere else. The two don't always pay the same — under Medicare, POS 10 maps to the higher non-facility rate, so defaulting every virtual session to 02 can quietly underpay your practice. Modifier selection is the second piece: modifier 95 signals a synchronous audio-video session, while modifier 93 signals audio-only, which Medicare now covers permanently for behavioral health services. Traditional Medicare fee-for-service identifies telehealth by place of service rather than requiring modifier 95, but most commercial payers still expect it, so verify the requirement plan by plan. Beyond coding, the note itself should document the client's consent to be treated by telehealth (verbal consent recorded at the start of the session is acceptable), the platform used, and the client's physical location at the time of service — the last one matters because the client's state determines which licensure rules apply to the session. What telehealth does not change is the time math: a 50-minute video session is still 90834, and a 58-minute video session is still 90837, provided the note documents the actual psychotherapy minutes.
One Medicare-specific rule to keep on your radar: for dates of service after December 31, 2027, Medicare will require an in-person, non-telehealth visit within the six months before a new patient's first mental health telehealth service, and at least one in-person visit every 12 months thereafter — patients already established in telehealth care on or before that date are exempt from the initial six-month visit but still fall under the annual requirement.
Audit-Ready Psychotherapy Notes, Every Session
Built for behavioral health documentation — templates that prompt for the session details, clinical rationale, and treatment-plan connections that keep psychotherapy claims defensible, with coding and claims handled in the same system. Start your free trial today.
- Behavioral health progress note templates built around how clinicians actually document a session
- Prompts for the elements reviewers ask for: interventions used, client response, risk assessment, and plan for continued treatment
- Treatment plans linked to your notes, so an extended session connects back to a documented goal
- CPT and ICD-10 selection on the note itself, carried through to the claim without re-entry
See how ICANotes can support your clinical workflow. Start your free 30-day trial, no credit card required.
Start Your Free 30-Day Trial
Explore ICANotes and see how it can simplify your clinical workflow. No credit card required.
Frequently Asked Questions
What is the exact time range for CPT code 90834?
What is the exact time range for CPT code 90837?
Can I bill CPT 90837 for a 50-minute therapy session?
What is the key difference between 90834 and 90837?
Do commercial insurance companies require prior authorization for 90837?
Can I bill CPT 90837 and 90791 on the same day?
Does the 90837 time requirement include administrative documentation time?
Why do insurance payers audit 90837 claims more frequently than 90834?
How much does CPT 90837 reimburse?
Can medication management (E/M codes) be billed concurrently with 90834 or 90837?
How often can CPT 90837 be billed?
References
- Centers for Medicare & Medicaid Services (CMS). Local Coverage Article A57520 — “Billing and Coding: Psychiatric Diagnostic Evaluation and Psychotherapy Services.” Source for the 90832/90834/90837 time ranges and the start/stop-time documentation requirement cited throughout this article. cms.gov/medicare-coverage-database, Article A57520
- Centers for Medicare & Medicaid Services (CMS). Local Coverage Article A57480 — “Billing and Coding: Psychiatry and Psychology Services.” Confirms the separately-identifiable-service requirement for billing E/M and psychotherapy together. cms.gov/medicare-coverage-database, Article A57480
- Centers for Medicare & Medicaid Services (CMS). MLN901705 — “Telehealth & Remote Monitoring” (December 2025). Source for the POS 02 vs. POS 10 place-of-service distinction referenced in the telehealth section. cms.gov/files/document/mln901705-telehealth-services.pdf
- American Medical Association (AMA). CPT® codebook — psychotherapy code descriptors and time-based coding guidelines (90832, 90834, 90837). Proprietary reference; time ranges above are cross-verified against CMS Article A57520.
Dr. October Boyles
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.




