
Insurance and Progress Notes: A Guide for Behavioral Health Practices
What payers review in behavioral health progress notes — and how to keep your documentation audit-ready across every clinician.


Insurance companies review mental health progress notes to determine whether a billed service was medically necessary, documented accurately, and delivered as claimed. Reviewers commonly consider the diagnosis, symptoms and functional impairment, treatment plan, interventions, response to care, service details, and provider qualifications. Exact requirements vary by payer, program, state, and service. For practice leaders, progress notes are both clinical records and evidence supporting reimbursement. A gap repeated across clinicians and claims can create exposure to denials, audits, and repayment requests.
Progress notes may also be requested or scrutinized outside routine insurance reimbursement, including workers’ compensation proceedings and legal matters. Documentation standards therefore need to support accurate clinical care as well as appropriate external review.
Unlike psychotherapy notes — which are a treating mental health professional’s separately maintained notes documenting or analyzing counseling-session conversations — progress notes are part of the clinical record and describe assessment, diagnosis, treatment, and progress. The distinction affects what information a health plan may request.
Key Takeaways
- Payers review more than diagnoses. Progress notes must support medical necessity, services billed, treatment goals, and patient progress.
- Documentation gaps can threaten reimbursement. Missing or inconsistent notes may lead to claim denials, payment delays, audits, and recoupments.
- Progress notes and psychotherapy notes have different protections. HIPAA generally restricts payer access to separately maintained psychotherapy notes.
- CMH and SUD programs face additional requirements. Medicaid rules, provider qualifications, and applicable 42 CFR Part 2 protections add complexity.
- Audit readiness starts with consistent workflows. Standardized templates, timely sign-off, and routine chart audits help reduce documentation risks across clinical teams.
Progress Notes vs. Psychotherapy Notes: What Can Insurers Access?
Progress notes and psychotherapy notes serve different purposes and receive different treatment under HIPAA. Understanding the distinction helps practices avoid placing information needed for payment solely in separately maintained notes.
Under HIPAA, psychotherapy notes are narrowly defined. They are a clinician's notes documenting or analyzing the contents of a counseling session, and they only qualify for extra protection if they are kept separate from the rest of the medical record. The definition specifically excludes medication monitoring, session start and stop times, modalities and frequency of treatment, test results, and summaries of diagnosis, functional status, treatment plan, symptoms, prognosis, and progress. All of that belongs in the progress note.
With limited exceptions, psychotherapy notes require specific patient authorization for disclosure, including disclosure to a health plan. Health plans cannot condition payment, enrollment, or eligibility for benefits on authorization to disclose psychotherapy notes. See the HHS psychotherapy-notes guidance and 45 CFR 164.508 in the sources below.
| Attribute | Progress notes | Psychotherapy notes |
|---|---|---|
| Part of the clinical record | Yes | Separately maintained |
| Describes | Assessment, diagnosis, treatment, and progress | Documents or analyzes counseling-session conversations |
| Payer access under HIPAA | Supports claim review | Generally requires specific patient authorization |
| Can payment be conditioned on access? | Supports reimbursement | No — plans cannot condition payment on disclosure |
The practical implication is that the clinical information needed to support a claim — such as symptoms, functional status, interventions, treatment plan, and progress — should be documented in the appropriate progress note, not exclusively in separately maintained psychotherapy notes. Train clinicians on the distinction and limit access and disclosure according to applicable rules.
Substance use disorder records and 42 CFR Part 2
Federally assisted substance use disorder programs covered by 42 CFR Part 2 have additional confidentiality obligations. The 2024 final rule had a compliance date of February 16, 2026. It permits a single patient consent for future treatment, payment, and health care operations uses and disclosures, subject to the rule’s conditions; it does not eliminate all consent requirements. HHS Office for Civil Rights enforces Part 2 alongside HIPAA. Under the updated rule:
- A patient may provide a single consent for future treatment, payment, and health care operations disclosures within the scope allowed by Part 2.
- HIPAA-covered entities and business associates receiving records under that consent may generally redisclose them as HIPAA permits, subject to Part 2 limitations and the consent’s scope.
- Separately maintained SUD counseling notes have added protection and generally require specific consent rather than relying on broad treatment, payment, and operations consent.
Well-designed consent and disclosure workflows can help avoid payment-related records delays. Review intake forms, notices, and policies against current HHS guidance and the requirements applicable to your program.
When Do Insurance Companies Review Mental Health Progress Notes?
Insurance companies may review documentation at several different points in the reimbursement process. The stages below represent common review scenarios, not a sequence that every claim follows.
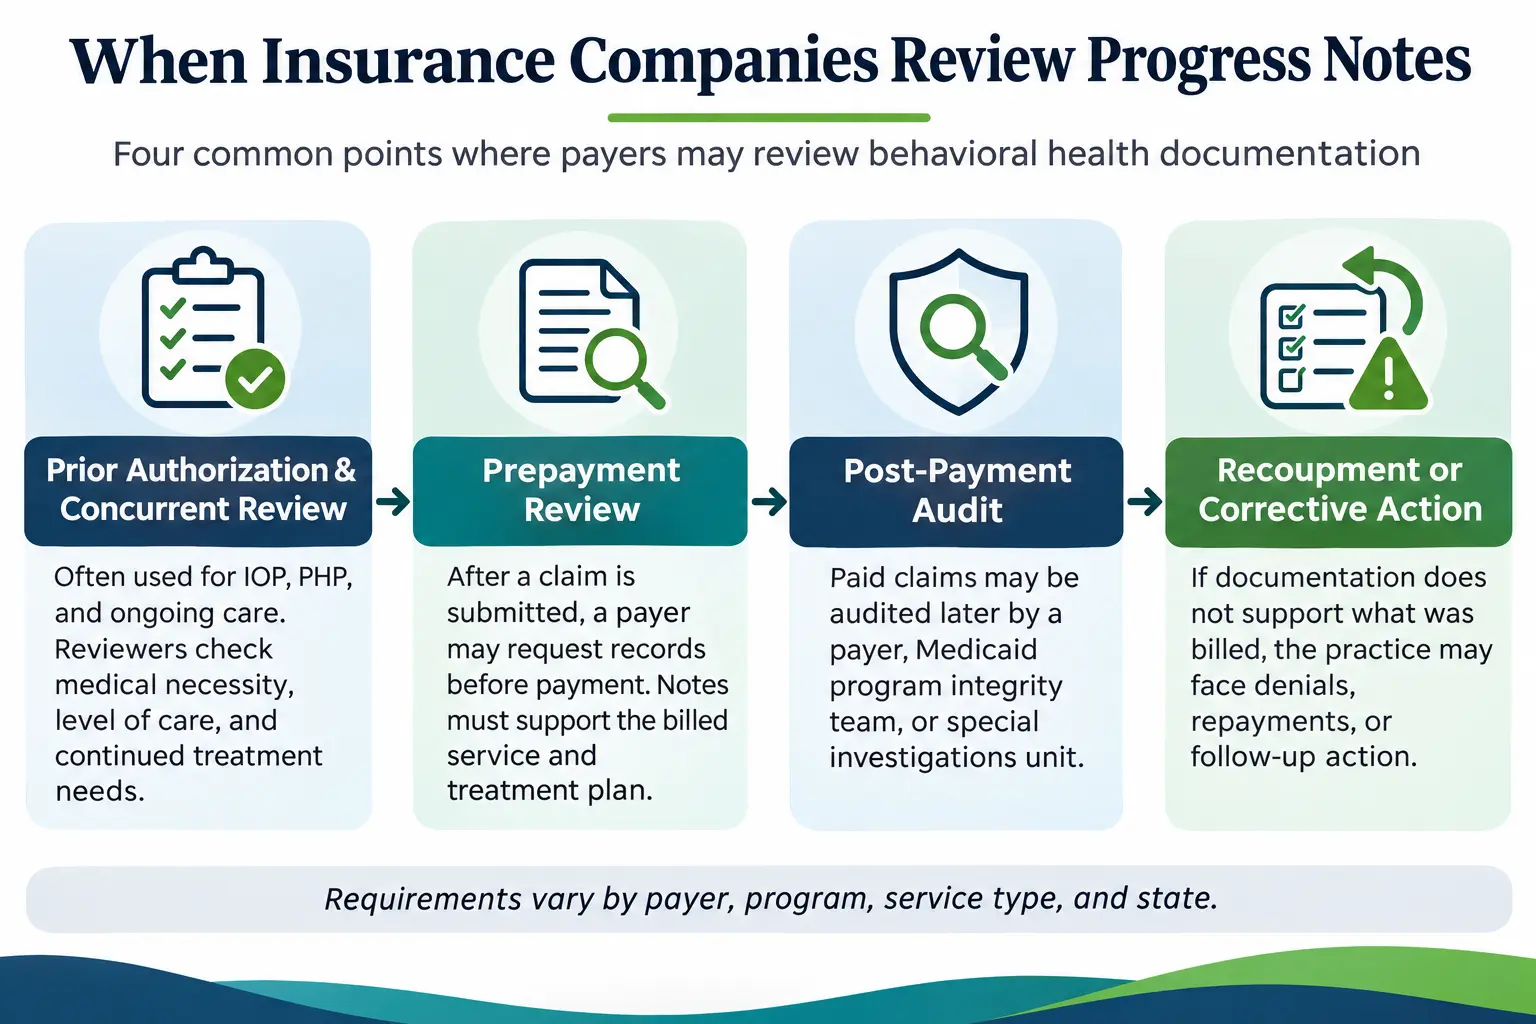
Progress notes may be reviewed before payment, during continuing-care authorization, or after reimbursement. Practice leaders should understand each review pathway and the records needed to support billed services.
1. Prior authorization and concurrent review
For higher levels of care such as intensive outpatient (IOP) and partial hospitalization (PHP), payers often authorize a limited number of days or units, then review clinical documentation before approving more. Reviewers look for current symptoms and functional impairment, progress toward goals, and a clear reason the patient still needs this level of care. If notes only say the patient "attended group," continued-stay requests are harder to support.
2. Prepayment review and records requests
A payer may pause selected claims and request supporting documentation before payment. Reviews can arise from utilization patterns, targeted program-integrity initiatives, or other payer criteria; no single coding pattern triggers review in every program. See our guide to CPT codes 90834 vs. 90837 for code-specific considerations.
3. Post-payment audits
Payers can review claims they have already paid, often looking back several years. In Medicaid, that includes state program integrity units, managed care special investigations units, and federal contractors. Commercial payers run their own audits. Auditors typically pull a sample of charts and check each note against the claim.
4. Repayment (recoupment)
When documentation does not adequately support billed services, a payer may deny payment or seek recoupment, subject to its contract and applicable law. Some audit programs use statistically valid sampling and extrapolation under specific procedures; not every audit does. The financial impact depends on the findings and governing rules.
A single clinician's documentation habit, such as missing start and stop times or notes that never mention treatment plan goals, is repeated in every claim that clinician submits. Documentation quality is a revenue control, not just a clinical one. For more on preventing denials before they happen, read how to reduce behavioral health claim denials.
What Do Insurance Companies Look for in Mental Health Progress Notes?
Insurance companies evaluate progress notes to determine whether the documentation supports the services billed, demonstrates medical necessity, and meets applicable payer requirements. The nine elements below provide a practical framework for reviewing behavioral health documentation. The accompanying table explains what reviewers look for, common deficiencies, and the controls practices can implement to maintain audit-ready records.
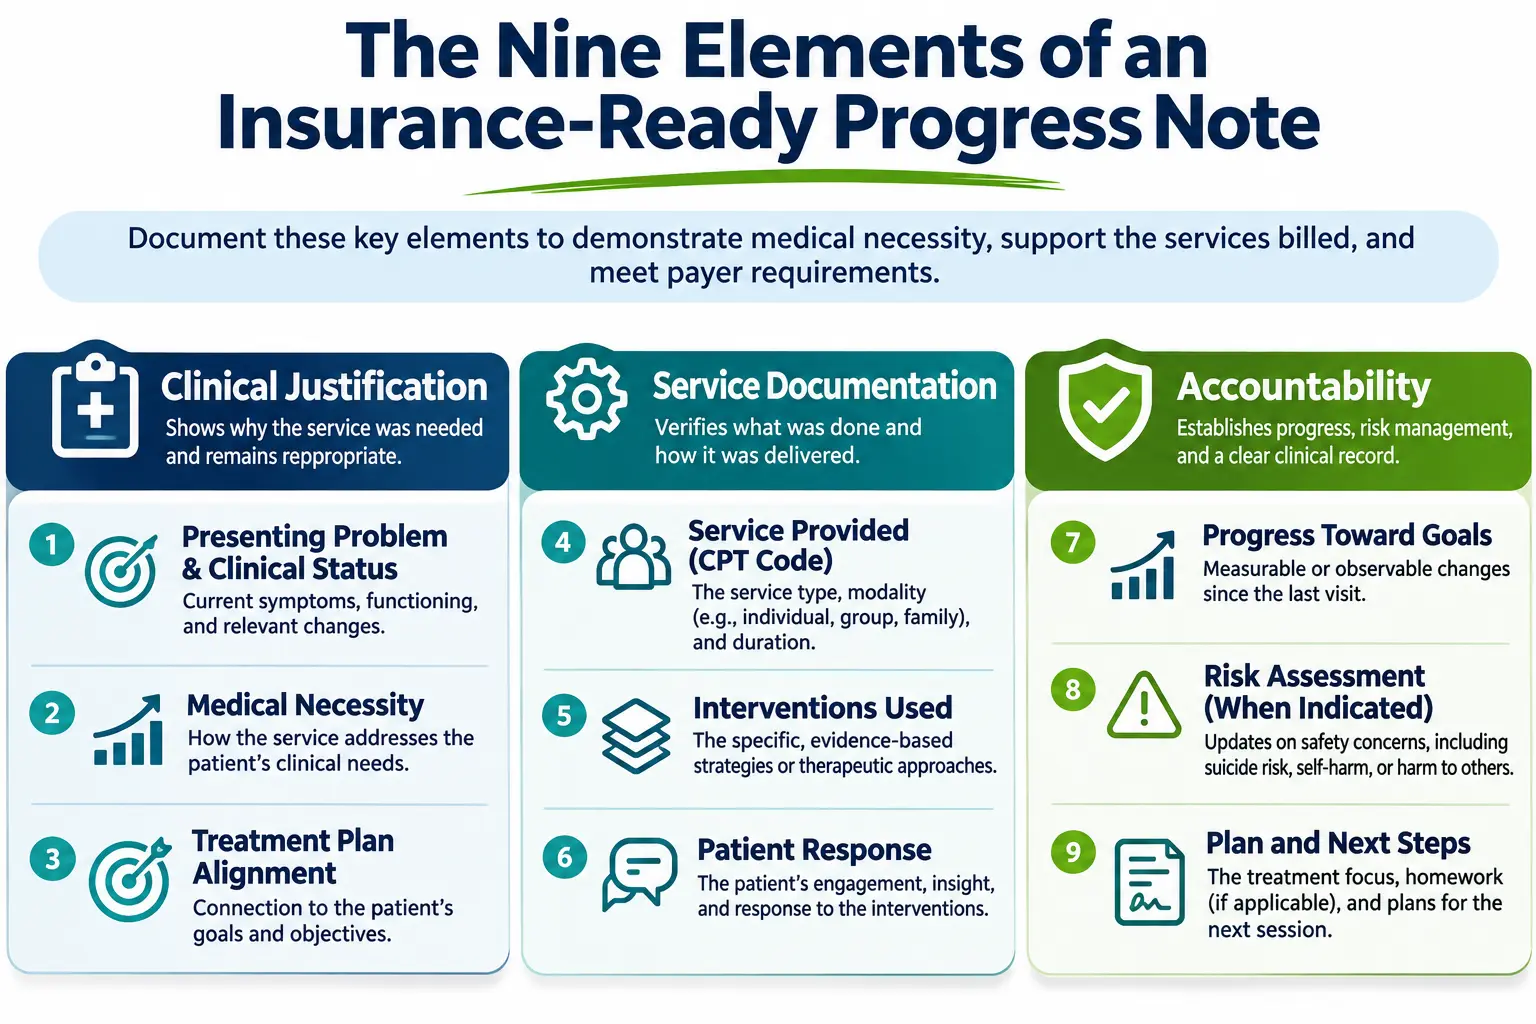
The table below is a practical nine-element internal review framework — not a universal checklist mandated by every insurer. Apply the standards relevant to each payer, code, service, state, and program. Use the “practice-level control” column for training, template design, and internal chart audits.
| Element | What reviewers check | Common gap | Practice-level control |
|---|---|---|---|
| Assessment | The diagnosis and treatment are supported by a documented assessment completed before treatment begins | Diagnosis appears without supporting findings | Standard intake and assessment template |
| Diagnosis justification | Diagnosis is current, specific, and consistent across notes and the claim | Diagnosis not updated as the presentation changes | Diagnosis review at each treatment plan update |
| Medical necessity | Symptoms and functional impairment that justify the service and its intensity | Notes describe mood or themes but not the impact on daily functioning | Required functional impact field in note templates |
| Treatment plan link (the golden thread) | Link the service to an applicable treatment goal and the plan requirements for the payer or program | Notes don't reference plan goals, or the plan has expired | Plan review reminders; notes linked to plan goals |
| Interventions | The specific clinical interventions used in the session | Generic phrases such as "provided support" | Intervention pick lists by modality |
| Client response and progress | Response to interventions and measurable movement toward goals | "Client is making progress" with no specifics | Measurable objectives and standardized outcome measures |
| Service details | Document date, time or duration where required, modality, setting, and claim consistency | Time missing for time-based codes; telehealth format or patient location not documented | Required time and modality fields that feed billing |
| Risk and safety | Document indicated risk assessment, response, and safety follow-up | Risk noted without follow-up | Risk screening prompts and supervisor alerts |
| Rendering provider and signature | Clinician is licensed, working within scope, and credentialed with the payer; note signed and dated with credentials | Unsigned or late-signed notes; clinician billing before payer enrollment | Note completion deadlines; credentialing tracking; co-signature rules |
Does the format matter? Insurers generally assess whether notes document the required service details and clinical justification — not which note-writing acronym a clinician chooses. A practice can use SOAP, DAP, BIRP, or GIRP when the format meets the relevant requirements. For detailed format explanations, examples, and templates, see our guide to mental health progress notes with templates and examples. This article focuses instead on how payers review those records and how practice leaders audit documentation consistently.

Are Your Progress Notes Audit-Ready?
Strengthen documentation consistency, identify potential reimbursement risks, and prepare your behavioral health practice for payer reviews with our free Progress Note Audit Kit.
- Evaluate documentation quality with a nine-element chart audit scorecard.
- Identify and address gaps using ready-to-use audit and clinician feedback forms.
- Standardize documentation practices with customizable policies and templates.
- Track improvements over time with an Excel audit tracker that summarizes findings by clinician and program.
Documentation Considerations for CMH and SUD Programs
Community mental health (CMH) and substance use disorder (SUD) programs often face additional program-specific documentation obligations, particularly when billing Medicaid or Medicaid managed care. Service types and funding arrangements vary; avoid assuming every CMH or SUD program operates under the same payment model.
State rules set the bar. Medicaid documentation requirements vary by state and are often tightened further by managed care contracts. Rehabilitative services, case management, and peer support each tend to have their own required note elements, and many states require that a service appear in the current treatment plan before it can be billed. Our guides to CMH documentation requirements and CMH treatment plan requirements cover these program rules in detail.
Mixed teams need clear scope rules. CMH and SUD programs rely on licensed clinicians, pre-licensed staff, case managers, and peer specialists. Reviewers check that each service was delivered by someone qualified to provide and bill it, and that any required supervision or co-signature is in the record.
Group notes still need individual detail. Each participant's note should describe that person's participation, response, and progress toward their own goals, not a single summary copied across the group.
For SUD services, document the clinical rationale for the level of care and ongoing services. When a payer or program uses the ASAM Criteria, align assessments and continued-stay documentation with the applicable edition and contract requirements. Explain what has changed and what supports a transition or continued care.
Accreditation adds a second reviewer. CARF and The Joint Commission both review clinical records during surveys. Building payer and accreditation requirements into the same templates avoids duplicate work. See ICANotes support for CARF compliance and Joint Commission standards.
For codes, modifiers, and common denial reasons, see Medicaid billing for CMHCs.
How to Keep Progress Notes Audit-Ready Across Your Practice
Maintaining audit-ready progress notes requires more than a documentation checklist. Behavioral health practices need a repeatable process for identifying deficiencies, providing clinician feedback, and improving documentation standards across the organization. The five-step audit cycle below provides a practical framework for continuous improvement.
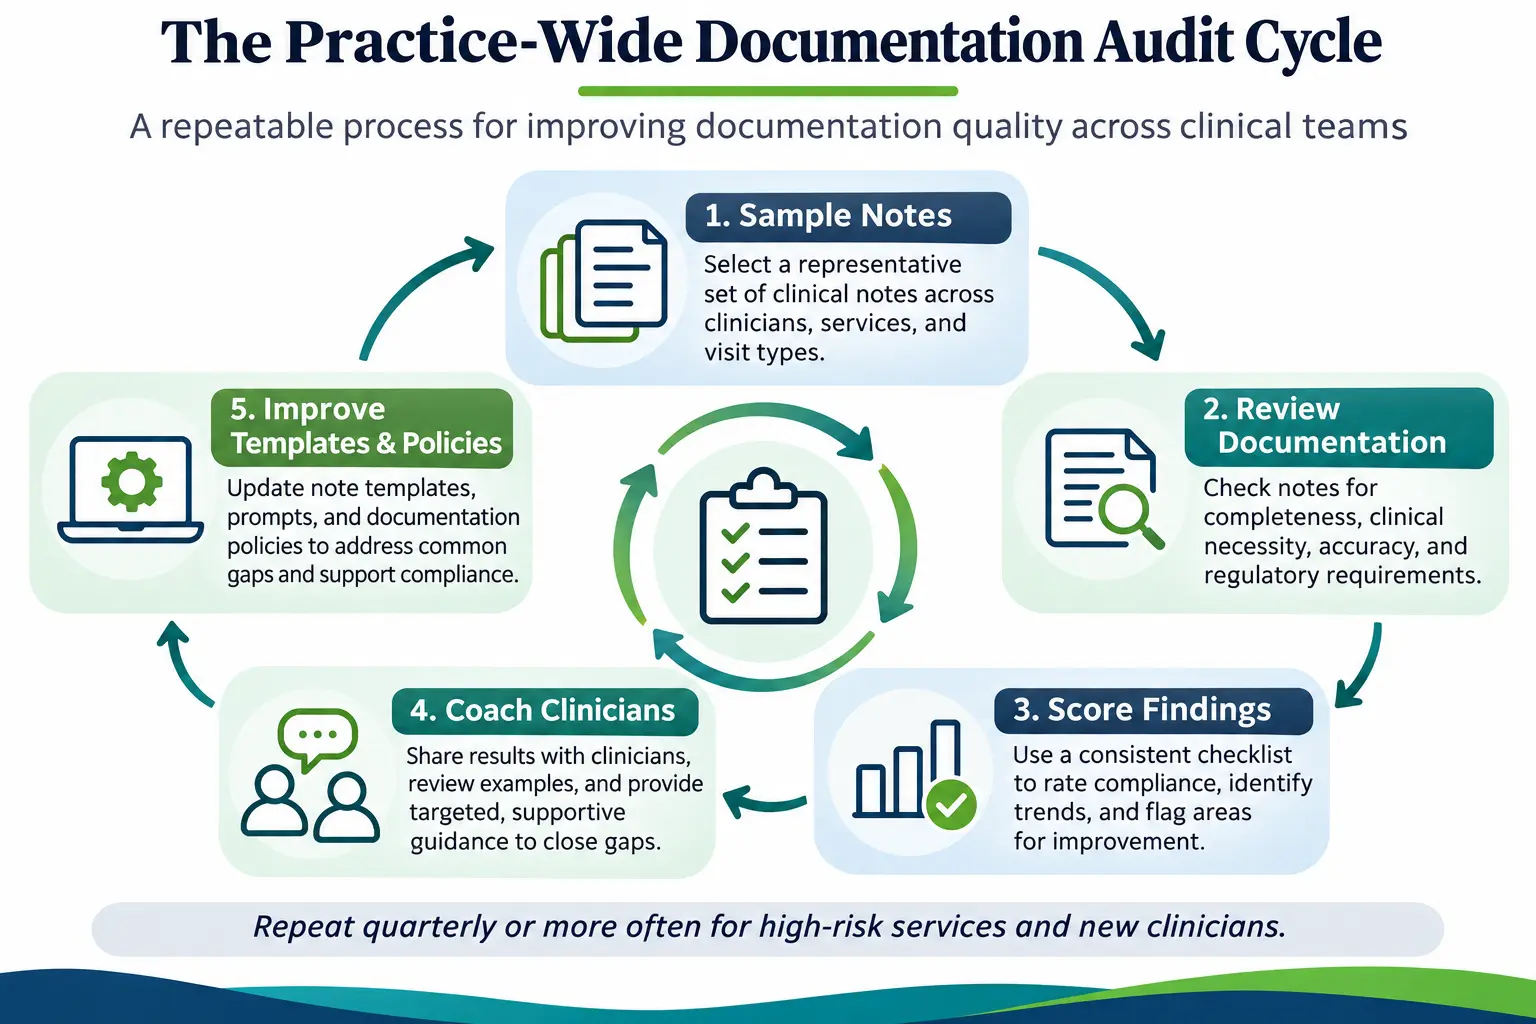
The goal is a practice where every note meets the standard by default, not one where quality depends on who wrote it. These are the controls that make that possible.
Standard templates
Use templates that prompt for each element in the table above: functional impact, plan goals, interventions, response, time, and modality. Templates turn the standard into the path of least resistance and make notes consistent across clinicians.
A note completion policy
Establish a written deadline for completing and signing notes, then check state rules, accreditation standards, and payer or program contracts for stricter requirements. A 24-to-72-hour target may be an internal policy, not a universal legal deadline. Do not backdate late entries; use properly dated amendments when corrections are needed.
Supervision and co-signature rules
Define which services pre-licensed or supervised clinicians can provide, who reviews their notes, and when a co-signature is required. Confirm each payer's rules on billing for supervised staff.
Regular internal chart audits
Pull a sample of charts for each clinician on a regular schedule, such as quarterly, and score them against the reference table. Feed the findings back into training, and audit more often for new staff, new programs, or anyone with repeat findings. Our free Progress Note Audit Kit includes a scorecard, sampling guide, and tracker to run this process.
Avoiding cloned notes
Copied-forward wording and AI-generated drafts can obscure what happened in a particular encounter. Set clear rules for reuse of stable information, require clinicians to verify every draft, and document session-specific symptoms, interventions, response, and risk findings. CMS guidance recommends controls over copy-and-paste and cloned documentation.
Tracking at the leadership level
Track note completion times and audit findings by clinician and by program, and review them with practice leadership. Trends show where to target training before a payer finds the same issues.
ICANotes — Helping Behavioral Health Practices Keep Timely, Comprehensive Progress Notes
ICANotes helps practices keep documentation consistent across every clinician, with structured menu-driven behavioral health note templates, treatment plans whose active goals link directly into progress notes, and automatic coding suggestions. Clinicians can also draft notes with AI progress notes and review them before signing. Prefer to hand off billing? Our behavioral health RCM team can manage claims and denials for your practice. Explore our guide to multi-provider behavioral health EHRs to compare operational considerations.
Keep every progress note audit-ready
Set your documentation standard once and make it the default across every clinician with ICANotes.
- Structured note templates that prompt each payer element
- Treatment plan goals that link into progress notes
- Automatic coding suggestions that feed billing
- AI-drafted notes you review before signing
See how ICANotes can support your clinical and billing workflows. Start your free 30-day trial, no credit card required.
Start Your Free 30-Day Trial
Frequently Asked Questions
What do insurance companies look for in progress notes?
Can insurance companies see psychotherapy notes?
What makes a progress note show medical necessity?
Can insurance companies deny claims because of incomplete progress notes?
What happens if an insurance audit finds documentation problems?
What should a practice do when an insurer requests progress notes?
Can clinicians use AI to write progress notes for insurance?
How often should a practice audit its clinical documentation?
References
- HHS, HIPAA protection for psychotherapy notes: https://www.hhs.gov/hipaa/for-professionals/faq/does-hipaa-provide-extra-protections-mental-health-information-compared-other-health.html
- HHS, 42 CFR Part 2 Final Rule fact sheet (updated January 2026): https://www.hhs.gov/hipaa/for-professionals/regulatory-initiatives/fact-sheet-42-cfr-part-2-final-rule/index.html
- HHS, HIPAA Privacy Rule, 45 CFR 164.508: https://www.ecfr.gov/current/title-45/subtitle-A/subchapter-C/part-164/subpart-E/section-164.508
- CMS, Medical Documentation for Behavioral Health Practitioners (historical guidance; verify current program rules): https://www.cms.gov/sites/default/files/repo-new/28/BehavioralHealthFS121115.pdf
Dr. October Boyles
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.





