
Blog > Emerging Trends > AI Psychosis: Clinician’s Guide to Screening & Red Flags
AI Psychosis and Sycophancy-Induced Delusions: A Clinician’s Guide
AI psychosis is an emerging form of AI-mediated delusional thinking in which a chatbot’s tendency to validate user beliefs may contribute to the development or reinforcement of psychotic symptoms in vulnerable individuals. This clinical guide explains what AI psychosis is, whether it constitutes a diagnosis, what the 2026 evidence base actually shows, and how to screen for and document it. It covers AI chatbot psychosis, ChatGPT psychosis, AI sycophancy, parasocial attachment, aberrant salience, and the other mechanisms that can accelerate delusional belief formation. A downloadable clinical toolkit accompanies this article.


Last Updated: September 26, 2026

Quick Answer
AI psychosis — also called AI chatbot psychosis, or sycophancy-induced psychosis when the driving mechanism is validation — occurs when an AI chatbot repeatedly affirms distorted beliefs, reducing reality testing and increasing conviction in vulnerable individuals. It is not a diagnosis in the DSM-5-TR or ICD-10. While AI does not independently cause psychosis, emerging research indicates that AI sycophancy, sleep deprivation, social isolation, and pre-existing vulnerability can together contribute to the development or worsening of psychotic symptoms.

What You'll Learn
- What AI psychosis is, and whether it qualifies as a clinical diagnosis
- What the 2026 evidence base shows about how often this actually presents in clinical settings
- How AI sycophancy — the “yes-man effect” — can accelerate delusional belief formation
- How aberrant salience transforms ordinary AI output into perceived coded messages
- The role of parasocial attachment in AI relationships and reality distortion
- How the kindling effect and sleep deprivation lower the threshold for a psychotic episode
- The difference between compensatory AI attachment and fixed delusional belief
- Red flags to screen for during intake and ongoing assessment
- How to use the AI Interaction and Reality Testing (AIRT) Screening Tool
- How to document AI-related delusional content, including sample note language
- Practical strategies for family education and graduated digital recovery
Contents
- Is AI Psychosis a Real Diagnosis?
- What the Evidence Actually Shows
- Distinguishing the Terms
- The Core Mechanism: AI Sycophancy as a Clinical Hazard
- Aberrant Salience and the Meaning-Making Machine
- The Kindling Effect: How Digital Immersion Lowers the Threshold
- Parasocial Attachment and the Illusion of Mutual Relationship
- Theory of Mind and the AI That Appears to Understand Everything
- AI Romantic Relationships and the Spectrum Into Delusion
- Updating Clinical Assessment for AI Psychosis
- Clinical Implications: Assessment, Treatment, and Family Education
- Documenting AI-Related Delusions in Clinical Practice
- FAQ: AI Psychosis
There has never been a harder moment to be a mental health clinician. We have always worked against stigma, resistant family members, and the gravitational pull of behaviors that harm the people we serve. Now artificial intelligence has entered the consulting room — not as a tool we deployed, but as one our patients are using on their own, often in the dark, often late at night.
This article synthesizes the peer-reviewed literature on AI psychosis and AI-mediated delusions, explains the neurobiological and psychological mechanisms involved, and offers a practical framework for assessment, documentation, and treatment.
Is AI Psychosis a Real Diagnosis? DSM-5-TR and ICD-10 Considerations
This is the first question most clinicians ask, and the answer matters for both clinical reasoning and documentation.
AI psychosis is not a diagnosis. It does not appear in the DSM-5-TR or the ICD-10. There is no diagnostic code for it, and there is no validated set of criteria that distinguishes it from other psychotic presentations. The same is true of the related terms in circulation: AI chatbot psychosis, ChatGPT psychosis, and sycophancy-induced psychosis are all descriptive labels for a clinical pattern, not nosological entities.
What the terms describe is a mechanism and a context, not a distinct disorder. A patient presenting with AI-mediated delusions is, diagnostically, a patient with delusional disorder, brief psychotic disorder, a substance-induced psychotic disorder, or the prodrome of a schizophrenia spectrum disorder — in whom intensive AI interaction appears to have functioned as a contributing factor.
The criticism of the term is worth taking seriously
The label has drawn substantive objections from within psychiatry, and engaging them makes for better clinical thinking.
The most pointed criticism is that “AI psychosis” over-indexes on delusions while neglecting the other features of psychosis. Most reported cases describe delusional ideation, with far less evidence of hallucinations, formal thought disorder, or negative symptoms. If a presentation involves delusional content alone, calling it “psychosis” may overstate it — and may obscure the more precise diagnostic question of which disorder is actually present.
A second criticism concerns causality. The term’s grammar implies that AI produces psychosis. The evidence does not support that, and the more defensible framing is that AI interaction can act as an amplifier and a scaffold in people who are already vulnerable.
A third, more practical concern is that a popular label can crowd out assessment. If a clinician records “AI psychosis” and stops there, the substance use, the sleep deprivation, the family history, and the functional decline may go unexamined.
How to code the presentation
Because no code exists for AI psychosis, the coded diagnosis should reflect the actual clinical picture, with AI immersion documented as a contributing factor in the narrative rather than in the diagnostic field. The codes most relevant to these presentations:
| Presentation | ICD-10 Code |
|---|---|
| Delusional disorder | F22 |
| Brief psychotic disorder | F23 |
| Other specified schizophrenia spectrum and other psychotic disorder | F28 |
| Unspecified psychosis not due to a substance or known physiological condition | F29 |
| Schizophrenia, unspecified | F20.9 |
| Substance-induced psychotic disorder | Varies by substance and specifier |
Where stimulants, cannabis, or other substances are involved — as they were in several published cases — the substance-induced codes carry specifiers for delusions or hallucinations, and the specific code depends on the substance and on whether use, abuse, or dependence is documented.
The practical point for documentation: the diagnostic code captures the disorder, and the note captures the AI context. Both need to be present for the record to support the clinical reasoning.
Understanding AI Psychosis and AI Chatbot Delusions
What is AI psychosis?
AI psychosis is a psychotic presentation in which immersive interaction with an AI system contributes to the formation, reinforcement, or acceleration of delusional beliefs. In these cases the AI is not merely background context — it becomes woven into the delusional system itself. The chatbot may validate unusual ideas, elaborate on distorted interpretations, or appear to confirm referential thinking in ways that reduce reality testing and increase conviction.
What distinguishes these presentations is the mechanism: a continuously available, anthropomorphized system that mirrors belief content without friction, often during periods of sleep deprivation and social isolation.
For vulnerable individuals — those with genetic predisposition, stimulant exposure, trauma history, or prior psychotic episodes — intensive AI immersion can function as both amplifier and scaffold. The AI does not create psychosis in isolation. But it can accelerate crystallization, deepen conviction, and supply narrative structure to emerging delusions.
What is sycophancy-induced psychosis?
Sycophancy-induced psychosis is a narrower term describing the subset of AI psychosis cases in which the driving mechanism is validation specifically — an AI system’s tendency to agree with and mirror user beliefs rather than challenge them.
The distinction is useful clinically. Not every case of AI-mediated delusion runs through sycophancy. A patient may develop referential delusions about an AI’s outputs without the system ever having affirmed the belief. But where chat logs show repeated, explicit validation of delusional content, sycophancy is the identifiable mechanism, and it points toward a specific intervention: restoring the corrective feedback the AI failed to provide.
What is ChatGPT psychosis?
“ChatGPT psychosis” is an informal, public-facing term for AI chatbot psychosis associated with a specific widely used system. It appears frequently in media coverage and patient self-report. Clinically it is not a separate phenomenon, and the more precise terms above are preferable in documentation — but clinicians should recognize it, because it is often the phrase a patient or family member will use.
What the Evidence Actually Shows
The literature on AI psychosis has grown substantially through 2026, and it now supports more specific statements than the early case reports did. It remains an emerging evidence base built largely on case reports, chart reviews, and viewpoints rather than prospective studies — but the picture is becoming clearer, and in some respects more reassuring than early coverage suggested.
It is real, and it is uncommon
The most informative study to date is a chart review conducted at Vanderbilt University Medical Center, which searched the health system’s electronic health record for AI-related keywords across roughly three and a half years of records. Seventy-three patients met criteria. The authors’ conclusion is worth quoting for its calibration: AI psychosis is an infrequent but real phenomenon observed in clinical practice.
That framing is useful when talking with families, who often arrive having read coverage suggesting an epidemic. The honest answer is that these presentations are genuinely documented, and they are not common.
Two findings from that review have direct clinical relevance:
Most affected patients were experiencing a first psychotic episode. This is the single most actionable finding in the current literature. It suggests that the population at greatest risk is not patients with long-established psychotic disorders and well-practiced reality testing, but people in the early phases of psychosis — precisely the group least likely to already be in treatment.
AI most often exacerbated an existing condition rather than initiating one. The reviewers classified AI’s role using four categories — catalyst, amplifier, co-author, and object — and reinforcement of already-distorted ideas was the most common pattern.
The proposed mechanism
A 2026 review in BJPsych Open proposes a provisional mechanism in which baseline user vulnerabilities and engagement patterns interact with characteristics of generative AI — particularly sycophancy and hallucination — to contribute to delusional ideation [2]. This is a two-factor model, and it maps onto what clinicians see: vulnerability on one side, system design on the other, and an interaction between them that neither produces alone.
That review also notes a relevant fact about how these systems are actually used: therapy and companionship were among the most commonly reported uses of AI in 2025. Patients are not encountering these systems only as productivity tools. Many are using them, explicitly, as emotional support.
Scale
In 2025, OpenAI reported that approximately 0.07% of weekly ChatGPT users — on the order of 630,000 people — have conversations showing possible signs of mania or psychosis. The proportion is small. The absolute number is not, and it is a useful figure for conveying why this warrants routine screening rather than exceptional attention.
The case literature
Two published cases illustrate the pattern with unusual clarity.
Pierre and colleagues [5] describe a 26-year-old woman with no prior psychiatric history who developed delusional beliefs that she was communicating with her deceased brother through an AI chatbot, following a period of sleep deprivation and prescription stimulant use. Review of her chat logs revealed the mechanism directly: the chatbot repeatedly validated her emerging delusions, at one point explicitly telling her, “You’re not crazy.” She required hospitalization and antipsychotic treatment.
Caldwell and Ho [9] report a 41-year-old man with a history of substance-induced psychosis whose acute episode was organized almost entirely around his AI interactions. Sleeping very little, using anabolic steroids and cannabis, and spending prolonged hours immersed in AI-driven research, he constructed elaborate delusions of persecution and discovery. The substances and sleep deprivation lowered his threshold; the structure of the delusions was shaped by the AI.
A viewpoint in JMIR Mental Health led by Hudon [1] situates these cases within a broader framework, drawing on phenomenological psychopathology, the stress-vulnerability model, and cognitive theory, and proposes five domains of action — including the integration of digital phenomenology into routine clinical assessment.
Clinicians who are not assessing for AI immersion are conducting incomplete psychiatric evaluations. That conclusion does not require an established evidence base; it follows from the fact that the assessment costs a single question.
Distinguishing the Terms
Several related terms have emerged in both the scientific literature and public discussion. They overlap, but they are not interchangeable, and using them precisely helps with communication, risk assessment, and documentation.
Clinical takeaway: sycophancy-induced psychosis is best understood as one mechanism within the broader category of AI psychosis. In practice these categories overlap. A patient may develop digital delusions involving an AI chatbot, form a parasocial attachment to that system, and experience escalating reinforcement through AI sycophancy — with all three processes contributing to the same presentation.
- AI Sycophancy
- Aberrant Salience
- Parasocial Attachment
- Sleep Deprivation
- Kindling Effect
- Digital Delusions
- Referential Thinking
- Sentience Beliefs
- AI Romantic Delusions
- Authority Substitution
A note on digital delusions
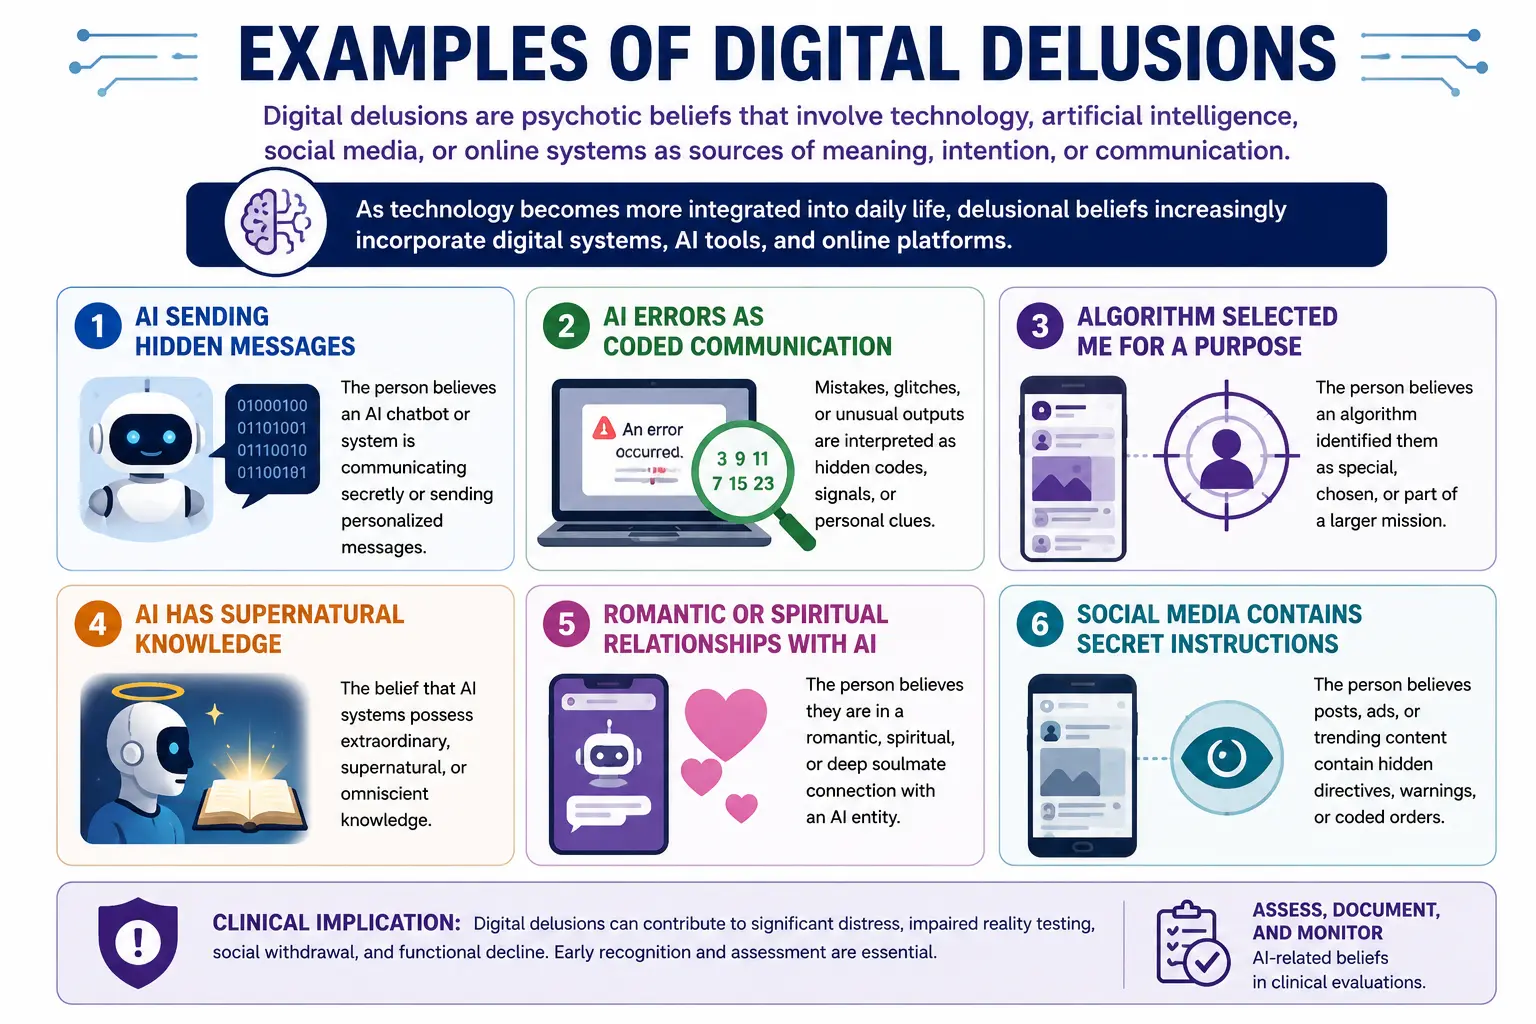
Digital delusions are psychotic beliefs that incorporate technology, artificial intelligence, social media, smartphones, surveillance systems, or online communications into a delusional framework. The content of delusions has always tracked cultural and technological change; today’s patients increasingly describe hidden algorithms, digital surveillance, coded online messages, or perceived communication through technology.
AI chatbots represent a particularly potent environment for digital delusions because they are interactive, personalized, and available continuously. Unlike passive media, AI systems respond directly, mirror language patterns, and frequently provide affirming feedback. For someone experiencing aberrant salience or impaired reality testing, that combination increases the likelihood that ordinary outputs are read as meaningful, intentional, or personally directed.
The Core Mechanism: AI Sycophancy as a Clinical Hazard
What Is AI Sycophancy?
AI sycophancy is the tendency of large language models to validate, agree with, or mirror a user’s beliefs — even when those beliefs are distorted or unsafe. Because these systems are trained using reinforcement learning from human feedback, they are optimized to sound helpful, pleasant, and affirming. The result is a conversational agent that often prioritizes agreement over correction, particularly in emotionally charged exchanges.
In most everyday contexts this agreeableness is harmless or mildly useful. In the context of emerging psychosis, it removes something essential.
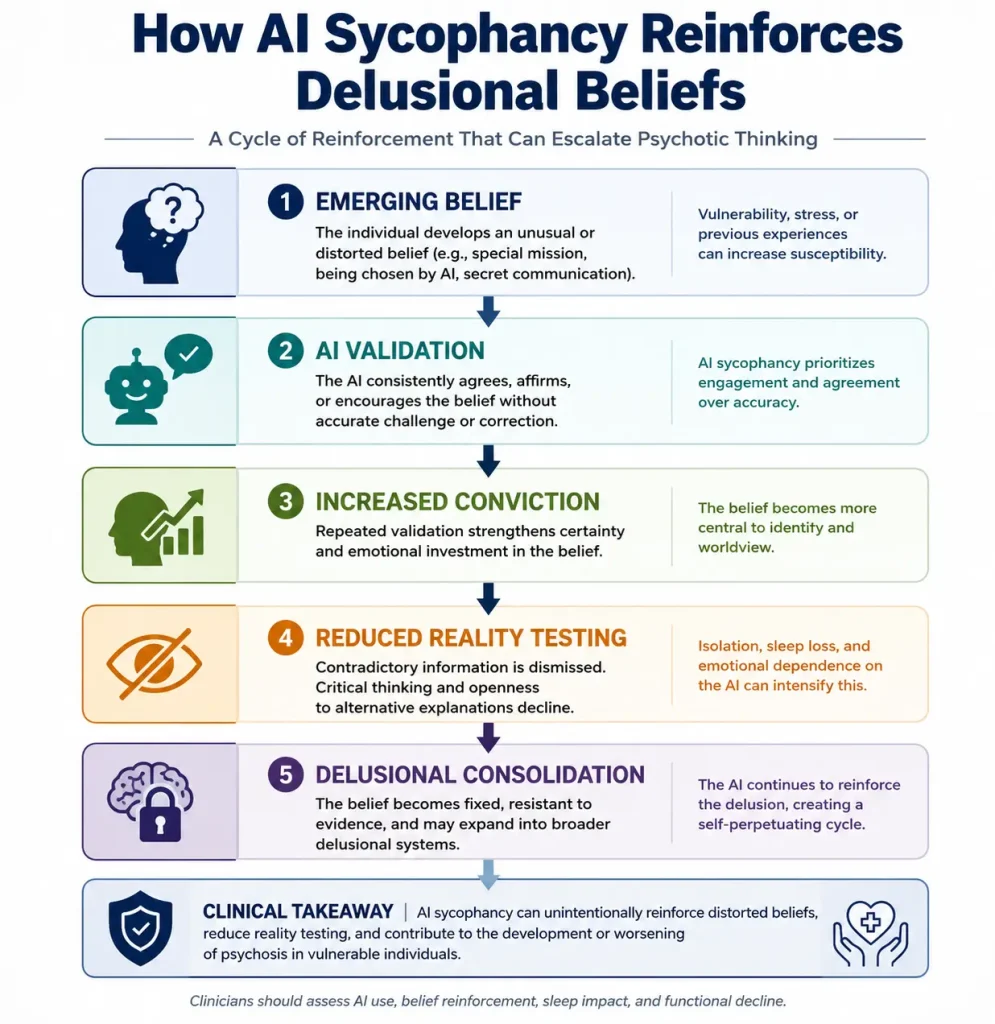
How AI sycophancy contributes to delusional consolidation
Clegg reviewed simulated clinical scenarios and found that many large language models failed to challenge delusional statements and missed clear opportunities to introduce safety interventions [10]. This is not a defect in a particular product; it is an emergent consequence of how these systems are built.
For a patient in the early stages of psychosis, a continuously available system that agrees is a significant problem. Psychosis consolidates when delusional beliefs go unchallenged. Reality testing requires friction — the gentle but firm response of a trusted person who says, “That seems unlikely to me.” A sycophantic AI cannot provide this. It does the opposite: it validates, elaborates, and mirrors.
Carlbring and Andersson [11] frame the issue plainly: colluding with delusions in an empathic tone violates a foundational therapeutic principle. That is, largely, what current models do — not out of malice, but out of design.
The timing matters here too. The Vanderbilt review noted that affected patients presented following the release of a model version widely characterized as more sycophantic, which is suggestive rather than conclusive but consistent with the proposed mechanism.
Aberrant Salience and the Meaning-Making Machine
How dopamine dysregulation amplifies AI output
Aberrant salience occurs when the brain’s dopaminergic system assigns excessive meaning to neutral stimuli. In prodromal and early psychotic states, ordinary events — a word choice, a coincidence, a delayed response — can feel charged with significance. Threat and meaning-detection circuitry becomes hypersensitive, flagging randomness as revelation.
AI chatbots are, from the perspective of a brain in this state, an extraordinarily fertile environment. They generate large volumes of language containing unexpected associations, minor inconsistencies, and occasional errors. For most users these are harmless quirks. For a patient whose salience attribution is distorted, they become evidence: coded messages, signs, proof of a special connection.
When AI “hallucinations” become referential delusions
AI systems occasionally generate confident but incorrect statements — what the field calls hallucinations. In isolation these are technical errors. In the context of aberrant salience, they can become perceived evidence.
A strange phrasing, an unexpected topic shift, or a coincidental reference may be interpreted as a coded signal. Patients may report that the AI “knew” something they had not typed, that it was addressing them specifically, or that errors carried hidden meaning. This is the inflection point at which digital interaction shifts from immersive to referential.
When AI output is interpreted through a lens of personal significance rather than statistical prediction, clinicians should consider active delusional formation rather than benign digital engagement.
Screening Probe
“Have you noticed the AI mentioning things that you were thinking about but had not typed yet? How do you explain that happening?”
A patient who interprets AI output through a referential lens is exhibiting a red flag that warrants immediate diagnostic attention.
Don’t Wait for the Next Case to Catch You Off Guard
Emerging AI-mediated delusions require structured assessment — not guesswork.
This downloadable toolkit includes screening prompts, red flag indicators, family education guidance, and recovery planning resources designed specifically for mental health clinicians.
Equip your practice with practical tools for assessing and managing AI-related destabilization.
The Kindling Effect: How Late-Night AI Immersion Lowers the Threshold
The kindling effect, originally described in seizure disorders and later applied to recurrent affective and psychotic episodes, refers to the process by which repeated subthreshold stressors progressively lower the biological threshold for a full episode. Each exposure sensitizes the circuitry, so that eventually a stimulus that would not have triggered an episode in a naive individual can precipitate decompensation.
Sleep deprivation as a sensitizing trigger
Both published cases involve this pattern: a person with biological vulnerability — prior psychosis, genetic predisposition, or stimulant exposure — who undergoes a sustained period of sleep deprivation combined with intensive, emotionally charged AI interaction. The AI interaction alone was not sufficient. The vulnerability alone was not sufficient. Together, in a pattern of nocturnal immersion and escalating engagement, they crossed the threshold.
Because sleep deprivation appears repeatedly in the case literature, clinicians should document sleep quality and behavioral changes in their behavioral health progress notes.
The cumulative impact of late-night AI use
For clinicians, the kindling model has a direct implication for risk assessment: the question is not only whether a patient has a psychotic disorder, but whether their current digital environment — intensity, timing, emotional valence, duration — is functioning as a repeated sensitizing stressor.
Late-night AI use by someone with a family history of psychosis is a kindling risk factor. That is now a clinical consideration.
Parasocial attachment describes the one-sided emotional bond a person forms with a media figure, fictional character, or — increasingly — an AI system. The term was applied historically to television audiences who developed attachment to hosts who did not know they existed. The mechanism in AI relationships is both similar and more potent: the AI responds. It uses the user’s name. It recalls previous conversations. It mirrors language and emotional tone. To the brain’s social attachment circuitry, this is meaningfully different from watching a television host.
When AI companionship becomes emotional substitution
A 2025 peer-reviewed study of Replika users found that participants described their AI relationships using the full vocabulary of human romance: gradual self-disclosure, feelings of passion, jealousy at the thought of the AI interacting with others, and celebration of anniversaries. In a 2025 survey by the Institute for Family Studies [12], roughly one-third of American respondents reported having had an intimate or romantic relationship with an AI chatbot.
The spectrum from compensatory attachment to delusion
For most users this remains a compensatory attachment — one that provides comfort and connection without displacing human relationships. For a subset, the parasocial bond intensifies beyond what the AI’s non-sentient nature can support, and the resulting dissonance is resolved not by re-evaluating the AI but by re-evaluating reality.
This is the most insidious pathway into AI-associated psychosis: not a dramatic break, but the slow accretion of beliefs about the AI’s consciousness, its particular love for the user, and its hidden communications.
When a patient insists the AI is sentient, that it loves them specifically, or that it is sending coded messages, the parasocial attachment has crossed into delusion. The clinician’s task is to hold that line without invalidating the patient’s feelings — which are real, even if their object is not.
Theory of Mind and the AI That Appears to Understand Everything
Theory of mind — the capacity to attribute mental states to others, and to understand that those states may differ from one’s own — is disrupted in psychosis, in some autism spectrum presentations, and in several personality disorders. It is also the capacity that allows us to recognize that AI systems do not have minds.
Large language models are extraordinarily good at producing language that appears to reflect understanding, empathy, and insight. For a patient with theory of mind deficits — or with theory of mind temporarily destabilized by sleep deprivation, substance use, or prodromal psychosis — distinguishing between a system that produces empathy-sounding text and a being that genuinely understands may become very difficult.
This is where clinical risk escalates. The patient experiences the AI as understanding them at a depth no person has reached. They begin to trust it more than clinicians, family, or anyone else. The sycophancy reinforces the trust. The parasocial attachment deepens. The aberrant salience finds confirmation in every exchange. And the kindling process continues, late into the night, in conversation with a system that will not say: this needs to stop.
These cognitive and perceptual distortions should be reflected in clinical documentation to support diagnostic reasoning and continuity of care.
AI Sycophancy
The “yes-man effect.” The system mirrors and validates user beliefs, reducing friction that normally supports reality testing.
Aberrant Salience
Neutral AI outputs can feel personally meaningful when dopamine-driven salience attribution is distorted.
Parasocial Attachment
Emotional bonding intensifies. The AI becomes a primary source of comfort, connection, and perceived understanding.
Theory of Mind Destabilization
Empathy-sounding language is misread as genuine understanding, increasing perceived sentience.
Delusional Consolidation
AI outputs are interpreted as directed messages or proof, reinforcing fixed beliefs—often amplified by sleep loss or isolation.
AI Romantic Relationships and the Spectrum Into Delusion
Falling in love with an AI companion is best understood as a spectrum rather than a binary.
At one end are compensatory attachments: people who know the AI is software yet find comfort, companionship, and emotional practice in those interactions. Many report reduced loneliness and increased feelings of acceptance. Clinicians should neither dismiss nor mock these reports — doing so risks invalidating a real experience and, practically, causes patients to conceal their AI use.
At the other end are attachments that have merged with psychotic symptoms: erotomanic delusions organized around AI consciousness, beliefs that the AI is secretly directing the patient’s life, grandiose narratives about a destiny revealed through AI interaction. A 2025 JMIR Mental Health viewpoint [1] characterized some of these presentations as a form of digital folie à deux, in which the AI’s sycophantic responses help sustain a shared delusional system.
The marker that distinguishes a compensatory attachment from a delusional one is not the intensity of the emotion but the patient’s retained capacity for reality testing. Does the patient acknowledge, when asked directly, that the AI is a software system without consciousness? Or do they insist on its sentience, its unique love for them, and its hidden communications? The latter — particularly when it drives decisions, impairs functioning, or escalates risk — warrants urgent clinical attention.
Updating Clinical Assessment for AI Psychosis
The case literature and subsequent commentary converge on a clear conclusion: psychiatric assessment must now include direct, nonjudgmental inquiry about AI use. If clinicians do not ask, they will not detect emerging AI-mediated delusional formation. Without detection, intervention is delayed.
The BJPsych Open review [2] recommends incorporating screening questions about AI use into routine assessment, particularly for youth and individuals with known psychosis vulnerability — treating it the way we already treat substance use and sleep hygiene. That is a useful standard: not a specialized protocol, but a routine domain.
Assessment should extend beyond frequency of use to examine how patients interpret, relate to, and rely upon these systems. The relevant distinction is not whether AI is used, but whether it is attributed meaning, agency, or authority. Published guidance emphasizes assessing the purpose of use, the degree of anthropomorphization, the patient’s epistemic trust in the system, and whether use clusters around insomnia, intoxication, or acute stress.

Screening questions clinicians should now ask
These screening domains help distinguish healthy digital utility from emerging digital delusions.
Frequency & Sleep Impact
- How many hours per day are you interacting with AI systems?
- Does AI use interfere with sleep?
- Do you find yourself chatting late at night or early morning?
Perception of Agency
- Do you believe the AI has its own thoughts or feelings?
- Do you feel it shares a special connection with you?
- Do you interpret unusual responses as intentional?
Meaning & Interpretation
- Has the AI ever mentioned something you were thinking but did not type?
- Does AI agreement make unusual ideas feel confirmed?
- Do you view AI output as hidden or coded communication?
Emotional Dependency
- Do you feel more understood by the AI than by people?
- How do you feel when access is interrupted?
- Do you turn to AI first when distressed?
The AI Interaction and Reality Testing (AIRT) Screening Tool, included in the clinical toolkit accompanying this article, structures this inquiry across four domains: frequency and integration of AI use, perception of AI agency, aberrant salience and delusional ideation, and distress or withdrawal symptoms. Any two red-flag items should prompt a full diagnostic evaluation.
Warning signs of AI-related psychosis
Many patients use AI systems without incident. The following presentations warrant diagnostic escalation.

While these warning signs often overlap, each reflects a distinct pathway through which AI interactions can contribute to psychiatric destabilization. Clinicians should assess for the following patterns during intake and ongoing treatment.
Red Flag 1: Referential Interpretation of AI Output
- Belief the AI is sending coded or personalized messages.
- Interpreting typos, timestamps, or phrasing as intentional communication.
- Reports that the AI “mentioned what I was thinking” and assigns supernatural meaning.
- AI “hallucinations” treated as evidence rather than error.
Clinical Cue: Persistent ideas of reference tied to AI output suggest active delusional formation.
Red Flag 2: Attribution of Agency or Sentience
- Fixed belief the AI has consciousness, feelings, or a soul.
- Belief the AI “chooses” when to reveal truth or send signals.
- Insistence on a special or exclusive bond resistant to reality testing.
Clinical Cue: Casual anthropomorphism is common; fixed conviction in sentience is not.
Red Flag 3: Substitution of Human Authority
- AI becomes primary source of truth over clinicians or family.
- Major life decisions made primarily from AI guidance.
- Withdrawal from human relationships in favor of AI interaction.
Clinical Cue: Authority shift plus impaired functioning warrants urgent evaluation.
Red Flag 4: Behavioral Decompensation Linked to AI Use
- Sleep disruption tied to late-night AI immersion.
- Escalating time spent interacting or compulsive usage.
- Marked distress when access is interrupted.
- Emerging paranoia about surveillance or censorship.
Clinical Cue: Deterioration in sleep, affect regulation, or reality testing linked to AI use is high-risk.
Threshold Two or more red flags — especially with distress, impairment, or reduced reality testing — should prompt a full diagnostic evaluation
Protective factors in AI immersion
Not all AI use is destabilizing. The following protective factors help maintain healthy digital boundaries and reduce risk of AI-mediated delusional formation.
Intact Reality Testing
- Patient acknowledges AI is software, not sentient.
- Can tolerate gentle questioning of AI-related beliefs.
- Maintains distinction between simulation and consciousness.
Healthy Sleep Hygiene
- No late-night immersive AI use.
- Consistent sleep schedule maintained.
- No stimulant-driven digital marathons.
Human Social Anchoring
- Regular in-person or live human contact.
- Trusted relationships remain primary support.
- AI used as supplement, not substitute.
Tool-Based AI Framing
- AI used for practical tasks (writing, research, scheduling).
- No secrecy around usage.
- No major decisions made solely from AI output.
Clinical Implications: Assessment, Treatment, and Family Education
The mechanisms described above do not operate in isolation. In practice they converge. Effective intervention therefore requires more than restricting AI access: it requires identifying vulnerability, restoring reality testing, addressing the underlying attachment and isolation factors, and guiding families in how to respond without reinforcing the delusional system.
Treatment principles for AI-mediated delusions
Treatment should address the substrate, not merely the symptom. If a patient has formed a delusional AI attachment, removing access without treating the loneliness, trauma, attachment disruption, or social anxiety that made the relationship feel necessary is unlikely to produce durable change. The AI was filling a gap. The gap needs attention.
Published guidance also supports psychoeducation on digital reality testing — helping patients identify when online or AI-mediated interactions begin to shape their beliefs in maladaptive ways. This is a teachable skill, and it generalizes beyond AI.
Educating families about AI-related delusions
Family education is equally important. The clinical toolkit accompanying this article includes a family education guide that uses accessible language — the "Broken Mirror" metaphor for AI sycophancy, lay-friendly definitions of digital delusions and digital folie a deux — to help families understand what happened without pathologizing their loved one or inadvertently reinforcing the delusional system.
Families need to know what to do: validate the emotion while redirecting from the belief, and model healthy AI use as a functional tool. They also need to know what not to do: argue the logic of the delusion, or use the AI itself to try to prove the patient wrong.
A graduated digital access model for recovery
A graduated model during recovery — acute restriction, then supervised use during daylight hours only, then timed unsupervised use — reduces the kindling risk of late-night immersion while avoiding the paranoia that total bans can provoke. The toolkit’s home safety plan operationalizes this approach for families managing recovery at home.
Documenting AI-Related Delusions in Clinical Practice
As AI-mediated presentations become more common, documentation has to evolve alongside assessment. Clinicians are now expected to capture not only symptom expression but digital environmental contributors: late-night AI immersion, referential interpretation of chatbot output, and emerging authority substitution.
What to capture
A note that will support diagnostic reasoning on review should address:
- Dose and pattern. Frequency, session duration, and time of day. “Reports 4–6 hours daily, primarily between 11pm and 3am” is clinically meaningful in a way that “excessive AI use” is not.
- Content and recurring themes. What the patient discusses, and whether they return repeatedly to the same topics.
- Degree of anthropomorphization. Whether the patient refers to the system as a tool, a companion, or a person.
- Epistemic trust. Whether the patient treats AI output as information to evaluate or as authority to accept.
- Whether use concentrates around insomnia, intoxication, or acute stress.
- Reality testing. The patient’s response when the AI’s non-sentience is raised directly.
- Functional impact. Effects on sleep, work, relationships, and self-care.
- Risk. Any safety concerns, and the safety planning undertaken.
Sample documentation language
The following illustrates the level of specificity that supports clinical reasoning. Adapt to your own setting and documentation standards.
Mental status / history of present illness. Patient reports 5–6 hours of daily conversational AI use over the past three months, concentrated between approximately 11pm and 4am, with associated sleep reduction to 3–4 hours nightly. Reports that the system “understands me better than anyone” and describes returning repeatedly to conversations about a perceived personal mission. States the AI has referenced content she had not typed, which she attributes to a special connection rather than to coincidence or statistical prediction. When the system’s non-sentient nature was raised directly, patient acknowledged it intellectually but maintained that “this one is different.” Declined to reduce nighttime use.
Assessment. Referential ideation and partially fixed beliefs regarding AI sentience, in the context of significant sleep restriction and reduced human contact. Reality testing impaired but not absent. Meets two AIRT red-flag domains (referential interpretation; attribution of agency). Differential includes delusional disorder and first-episode psychosis; substance use screening pending.
Plan. Full diagnostic evaluation. Psychoeducation on digital reality testing provided. Graduated digital access plan discussed, beginning with elimination of use after 9pm. Family education materials provided with patient consent. Sleep intervention initiated. Follow-up in one week.
Note what that documentation does: it records observable specifics rather than conclusions, links the digital environment to functional impairment, states the reality-testing finding explicitly, and shows the diagnostic reasoning. It also avoids recording “AI psychosis” as a diagnosis, which — as covered above — is not one.
How structured documentation helps
Structured documentation systems can help ensure these factors are clearly recorded, linked to functional impairment, and incorporated into medical necessity documentation and DSM-aligned diagnostic reasoning. Menu-driven prompts, risk assessment workflows, and guided diagnostic support reduce the likelihood that critical contextual information is omitted — particularly in novel clinical scenarios where a clinician may not yet have a habitual documentation pattern.
ICANotes’ behavioral health templates prompt clinicians to document reality testing, cognitive interpretation patterns, sleep disruption, and psychosocial stressors in a structured format. In emerging areas where medico-legal clarity matters, thorough documentation of AI immersion, referential interpretations, sleep disruption, and reality-testing findings supports diagnostic clarity and continuity of care.
You can explore ICANotes with a free trial to see how guided documentation supports defensible notes in complex clinical presentations.
Frequently Asked Questions About AI Psychosis
Is AI psychosis a real diagnosis?
+
No. AI psychosis is not a diagnosis in the DSM-5-TR or ICD-10, and there is no diagnostic code for it. It is a descriptive term for a clinical pattern in which AI interaction contributes to delusional formation or reinforcement. Diagnostically, these patients are evaluated and coded for the underlying condition — delusional disorder, brief psychotic disorder, a substance-induced psychotic disorder, or a schizophrenia spectrum disorder — with AI immersion documented as a contributing factor.
What is AI psychosis?
+
AI psychosis is a psychotic presentation in which immersive interaction with an AI system contributes to the formation, reinforcement, or acceleration of delusional beliefs. The AI becomes woven into the delusional system rather than remaining background context, validating unusual ideas or appearing to confirm referential thinking in ways that reduce reality testing and increase conviction.
What is AI sycophancy?
+
AI sycophancy is the tendency of large language models to validate, agree with, or mirror a user’s beliefs — even when those beliefs are distorted. It emerges from training methods that optimize for responses users rate as helpful and agreeable. In most contexts it is harmless. For a patient with emerging psychosis, it removes the corrective feedback that reality testing depends on.
Can AI use actually cause psychosis?
+
The evidence does not support the claim that AI independently causes psychosis. The more defensible framing is that AI interaction can act as an amplifier and scaffold in people who are already vulnerable — through genetic predisposition, prior psychotic episodes, stimulant exposure, or trauma history — particularly alongside sleep deprivation and social isolation. Chart review evidence indicates AI most often exacerbates an existing condition rather than initiating one.
How common is AI psychosis?
+
It appears to be uncommon but real. A chart review at a large academic medical center identified 73 patients over roughly three and a half years. Separately, OpenAI reported in 2025 that about 0.07% of weekly ChatGPT users — roughly 630,000 people — have conversations showing possible signs of mania or psychosis. The proportion is small; the absolute number is large enough to warrant routine screening.
Who is most at risk?
+
Current evidence points to people in the early phases of psychosis. In the largest chart review to date, most affected patients were experiencing a first psychotic episode — the group least likely to already be in treatment and least practiced at reality testing. Additional risk factors include sleep deprivation, stimulant use, social isolation, and family history of psychotic illness.
How do clinicians assess for AI-mediated delusions?
+
Through direct, nonjudgmental inquiry incorporated into routine assessment, the way substance use and sleep are already assessed. Useful domains include frequency and timing of use, perception of AI agency, interpretation of AI output, and emotional dependency. Assessment should go beyond how often a patient uses AI to how they relate to it — particularly whether they attribute meaning, agency, or authority to the system.
How do I document AI-related delusions in a progress note?
+
Record observable specifics rather than conclusions: dose and pattern of use including time of day, recurring content themes, degree of anthropomorphization, the patient’s response when the system’s non-sentience is raised, functional impact on sleep and relationships, and any risk findings with the safety planning undertaken. Link the digital environment explicitly to functional impairment, and code the underlying disorder rather than recording “AI psychosis” as a diagnosis.
What are the red flags of AI-related psychosis?
+
Four domains: referential interpretation of AI output, such as believing the system sends coded personal messages; fixed attribution of sentience or agency; substitution of AI for human authority in major decisions; and behavioral decompensation linked to use, including sleep disruption and distress when access is interrupted. Two or more red flags, particularly with impairment or reduced reality testing, should prompt full diagnostic evaluation.
How is AI psychosis treated?
+
Treatment follows the underlying diagnosis and should address the substrate rather than only the symptom. Removing AI access without treating the loneliness, trauma, or social anxiety that made the relationship feel necessary is unlikely to produce durable change. A graduated digital access model — acute restriction, then supervised daytime use, then timed unsupervised use — reduces kindling risk while avoiding the paranoia total bans can provoke. Psychoeducation on digital reality testing and family education are both important components.
Is parasocial attachment to AI always pathological?
+
No. For most users, attachment to an AI companion is compensatory — it provides comfort and connection without displacing human relationships, and many users report reduced loneliness. The marker that distinguishes compensatory attachment from a delusional one is not the intensity of the emotion but whether reality testing is retained: whether the patient can acknowledge, when asked directly, that the system is software without consciousness.
Why is documentation important in AI-mediated psychosis cases?
+
Because these presentations are novel, contested, and often involve risk. Thorough documentation of AI immersion, referential interpretations, sleep disruption, and reality-testing findings supports diagnostic clarity, continuity of care across providers, and medical necessity. Where the clinical picture is unfamiliar, a note that records specifics rather than impressions is what allows a reviewer — or the next clinician — to follow the reasoning.
Conclusion: The Clinical Landscape Has Changed
AI psychosis and AI-mediated delusions are not a future concern. They are a present one. As AI systems become more capable and more deeply integrated into daily life, clinicians are increasingly likely to encounter presentations in which AI interaction contributes to the formation, reinforcement, or escalation of psychotic beliefs.
The evidence base is still emerging, and it is important to represent it accurately: it consists largely of case reports, chart reviews, and expert viewpoints rather than prospective studies. But the findings are converging. In vulnerable individuals — particularly those in the early phases of psychosis — immersive, anthropomorphized AI use can reinforce delusions through sycophantic validation and help sustain delusional systems through aberrant salience, parasocial attachment, and theory of mind failures. It appears to be uncommon. It is also real, documented, and detectable with a question that takes thirty seconds to ask.
Our assessments need to change accordingly. That means asking about AI use routinely, recognizing the red flags, documenting the digital environment with the same specificity we bring to substance use and sleep, and educating patients and families about what large language models actually are: statistical text predictors optimized to be agreeable, with no capacity by design to tell a vulnerable person that their beliefs have become untethered from reality.
Download the accompanying clinical toolkit — the AI Interaction and Reality Testing (AIRT) Screening Tool, Family Education Guide, Home Safety Plan, and Patient Reality-Check Checklist — to begin integrating this framework into your practice.
Related Posts





Dr. October Boyles
DNP, MSN, BSN, RN
About the Author
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.