
Mental Health Progress Notes: 10 Examples and 5 Templates
A practical guide to what belongs in a behavioral health progress note, with five copy-ready note formats and ten fictional progress note examples.


A useful mental health progress note makes the care delivered in a specific encounter clear to the next clinician, the client, and, when applicable, a reviewer. This guide shows what to include, offers five copy-ready note formats, and provides ten fictional progress note examples across behavioral health settings. Adapt each example to the encounter you actually provided and the requirements that apply to your practice.
Document the reason for the encounter, relevant findings, the intervention or service, the client's response, progress toward the treatment plan when applicable, and the next step. The format can vary; the note should accurately reflect the encounter.
What you'll learn
- The six questions a mental health progress note should answer about symptoms, care provided, client response, progress, functioning, and continued treatment.
- How SOAP, DAP, BIRP, GIRP, and PIE organize the same clinical information.
- How to adapt five copy-ready note templates to the details of an actual encounter.
- What clear, specific documentation looks like in 10 fictional mental health progress note examples.
- How to connect the session to treatment goals and explain the need for continued care when appropriate.
- How to use the free Mental Health Progress Note Cheat Sheet to review a note before signing.
What Are Mental Health Progress Notes?
A mental health progress note records a behavioral health encounter: the client's presentation, the service provided, the client's response, clinical assessment, and next steps. It supports continuity of care and, when services are billed, helps show why the service was appropriate.
A progress note may serve several readers. A covering clinician needs to understand what changed and what comes next. The client may request access to much of the medical record. A payer may review documentation supporting a billed service. Include clinically relevant facts and reasoning without trying to transcribe every moment of the session.
- For continuity of care, record meaningful changes in symptoms, functioning, risk, and treatment direction.
- For a defensible record, distinguish client report from your observations and clinical judgment.
- For reimbursement, document the service furnished, relevant time when required, and the clinical basis for treatment under the applicable payer policy.
How are progress notes different from psychotherapy notes?
Under HIPAA, psychotherapy notes have a specific meaning: notes a mental health professional records to document or analyze the contents of counseling conversations and keeps separate from the rest of the medical record. Ordinary documentation of diagnosis, symptoms, treatment, and progress is not a psychotherapy note merely because the service was therapy. HHS guidance on psychotherapy notes.
| Progress notes | Psychotherapy notes | |
|---|---|---|
| Part of the medical record? | Part of the medical record | Maintained separately under the HIPAA definition |
| Required for billing? | May support a billed service | Not the documentation used to support a claim |
| Releasable to payers? | May be disclosed as permitted or required by applicable law and policy | Generally requires specific authorization, with limited exceptions |
| HIPAA protection | Standard | Heightened |
| Contents | Presentation, interventions, response, plan | Your private process notes, hypotheses, reactions |
Keep any separately maintained psychotherapy notes separate from the progress note. Record information needed for treatment, continuity, and billing in the medical record, while using professional judgment about the detail necessary. For a broader guide to clinical record types, see our related post on Types of Therapy Notes.
What to Include in a Behavioral Health Progress Note
The content needed depends on the service, setting, payer, and clinical circumstances. Use this list as a review guide, then follow the documentation standards that apply to your work. A routine follow-up may be brief; a change in risk, diagnosis, or treatment warrants more explanation.
| # | Element | What to capture when relevant |
|---|---|---|
| 1 | Session details | Date of service, start and end times, modality (in person or telehealth), client location if remote, client name plus a second identifier, provider name and credentials. |
| 2 | Presenting concern | Why the client came in today, in their words where possible. "Client presented reporting increased difficulty sleeping over the past two weeks, stating, 'I wake up at 3am and cannot stop thinking about work.'" — not "Client came in for therapy." |
| 3 | Clinical observations | Relevant observed findings and meaningful changes from baseline; include focused mental-status findings when clinically indicated. |
| 4 | Risk and safety | Risk findings and response when assessed or clinically indicated, consistent with the setting's screening policy. |
| 5 | Symptom status | Specific symptoms, not diagnostic labels. "Depression" is a diagnosis; "hypersomnia, anhedonia, and 15-lb weight loss over six weeks" are symptoms. Include scale scores and the change from last administration. |
| 6 | Interventions | Specific service or techniques delivered and the client's response; use enough detail to explain the encounter. |
| 7 | Client response | How the client actually responded — engaged, partially engaged, declined. This is your evidence that the service is having clinical effect, or that the approach needs to change. |
| 8 | Link to the treatment plan | Name the goal or objective this session addressed and state the progress. This is the Golden Thread, and it is the single strongest medical-necessity signal in the note. |
| 9 | Plan and signature | Next appointment, homework, referrals, medication changes, safety plan updates. Signed with name and credentials. |
The Golden Thread
The "golden thread" is the connection between assessment, diagnosis, treatment goals, the service provided, and follow-up. A progress note should make that connection visible when relevant. State which goal the encounter addressed and what the client's response or current status means for the plan.
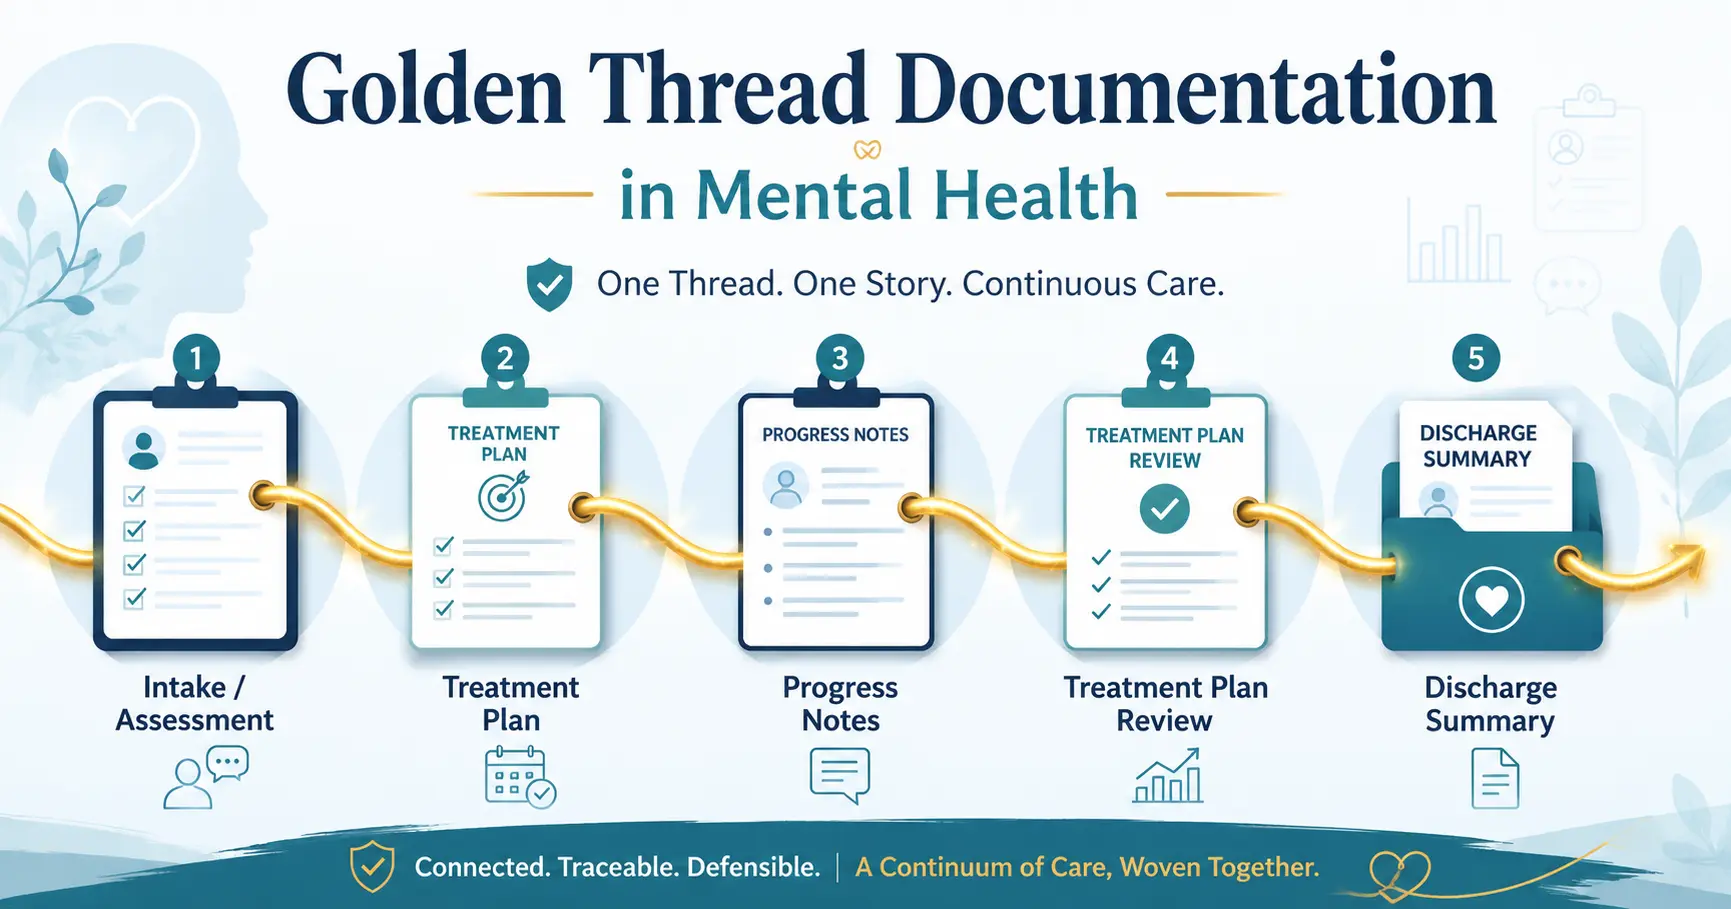
| Document | What it must establish |
|---|---|
| Intake / initial assessment | Presenting problem, DSM-5 diagnosis with the specific criteria met, diagnostic justification, baseline functioning |
| Treatment plan | Goals and objectives that directly address the documented diagnosis |
| Progress notes | Interventions used, client response, and progress toward each named goal |
| Treatment plan reviews | Updated goals, and clinical rationale for continuing, modifying, or ending treatment |
| Discharge summary | Course of treatment, goals achieved and not achieved, final clinical status, aftercare plan |
If progress is limited, explain the clinical picture and whether the plan should continue, change, or be reviewed. Lack of improvement alone does not establish that treatment was unnecessary.
Mental Health Progress Note Cheat Sheet
Use these six questions to review a note before signing: What symptoms did the client report? What did the clinician do? How did the client respond? What changed? How is daily functioning affected? When treatment is billed, why is continued care appropriate?
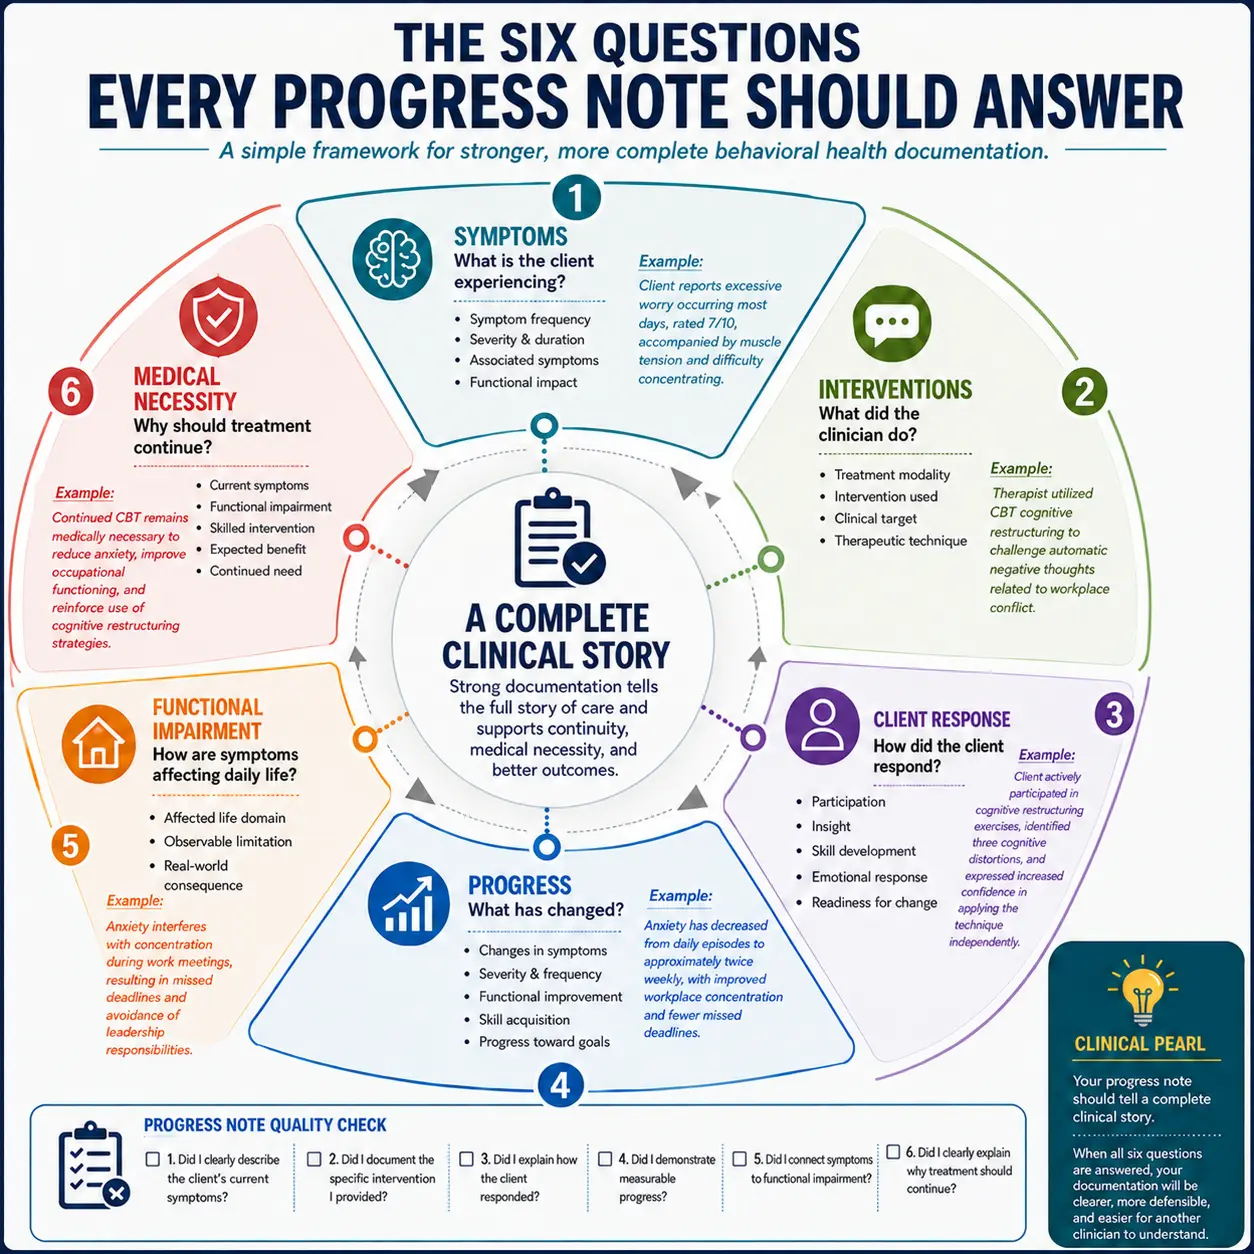
The six-question framework gives you a quick review of the clinical story. Document each element to the depth appropriate for the encounter and the rules that apply to your setting.

Get the Free Mental Health Progress Note Cheat Sheet
Keep a practical review guide close at hand when you’re ready to sign a note.
- Check your note against six key documentation questions.
- Use a quick checklist to spot details you may have missed.
- See the framework applied in a fictional, annotated SOAP note.
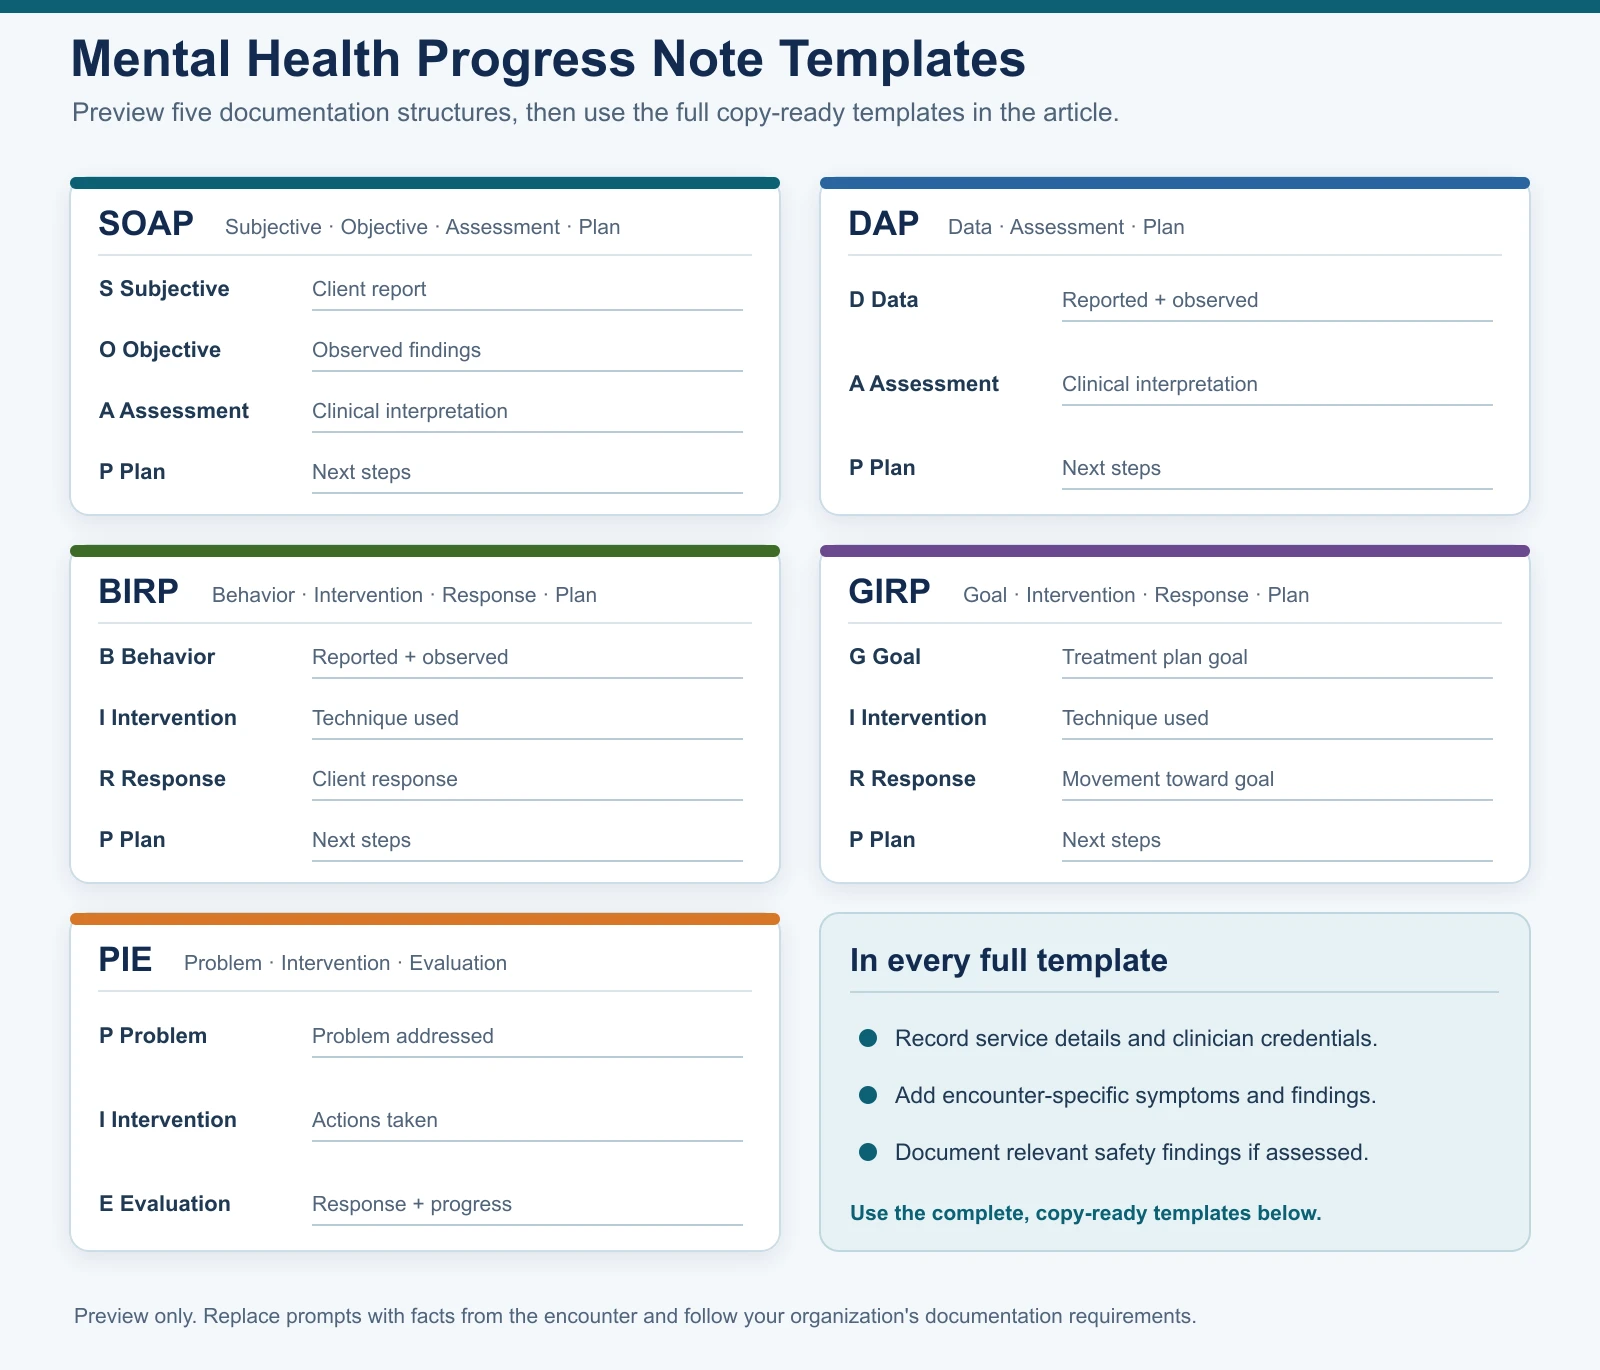
Five Mental Health Progress Note Formats
No single structure fits every practice. Use the format required by your organization or payer. When you can choose, select the one that helps you document the service clearly and consistently.
| Format | Sections | Best for | Main advantage |
|---|---|---|---|
| SOAP | Subjective, Objective, Assessment, Plan | Integrated care, medical settings, prescribers | Universally recognized; separates client report from clinical observation cleanly |
| DAP | Data, Assessment, Plan | Routine outpatient therapy | Combines reported and observed data; merges subjective and objective into one narrative section |
| BIRP | Behavior, Intervention, Response, Plan | Agency and community mental health, IOP, residential | Highlights what you did and how the client responded |
| GIRP | Goal, Intervention, Response, Plan | Goal-focused treatment | Opens with a treatment plan goal |
| PIE | Problem, Intervention, Evaluation | Case management, crisis work, nursing | Problem-led and compact; well suited to non-therapy encounters |
Which Mental Health Progress Note Format Should You Choose?
- GIRP puts a treatment goal first and can help clinicians keep the note connected to the plan.
- SOAP separates the client's report, observed findings, clinical assessment, and plan. It may fit integrated or prescribing settings.
- DAP combines reported and observed information in one Data section, which some clinicians find efficient for routine follow-up.
- BIRP gives interventions and the client's response their own sections, making that relationship easy to see.
- PIE organizes documentation around a problem, intervention, and evaluation. Some teams use it for case management and other service contacts.
- New point
Go deeper on individual formats: SOAP notes | DAP notes | BIRP notes | PIRP vs GIRP vs BIRP
Copy-Ready Mental Health Progress Note Templates
Choose a mental health progress note template, copy it into your approved documentation system and replace every prompt with encounter-specific information. Do not prefill a safety finding, intervention, or client response that was not assessed or observed. Add fields required by your organization or payer.
SOAP Note Template
DAP Note Template
BIRP Note Template
GIRP Note Template
PIE Note Template
Ten Mental Health Progress Note Examples
These fictional mental health progress note examples show different ways to document an encounter. They are teaching examples, not templates for clinical judgment or billing. Confirm diagnoses, code selection, time, scope of practice, and payer rules for the real service before using similar language.

1. Progress Note Example: Depression in Individual Therapy Using SOAP
Client reported continued low mood, stating, “I got out of bed every day this week, but it took me until noon most days.” Reports sleeping 11 to 12 hours nightly, down from 13 to 14 at intake. Completed four of seven scheduled behavioral activation entries. Identified returning to her weekly pottery class as the activity she most wants back. Denied alcohol use.
Appeared adequately groomed, a change from the previous two sessions. Psychomotor activity mildly slowed. Mood described as “flat but not awful”; affect constricted, congruent. Speech normal in rate and volume. Thought process logical and goal-directed. No perceptual disturbance. Insight fair, judgment intact.
Client demonstrates measurable symptom reduction, with a 5-point PHQ-9 decrease and improved hygiene and sleep duration. Functional impairment persists in the occupational domain; client remains on reduced hours.
Behavioral activation adherence is partial but improving, and the client is now generating her own activity targets rather than accepting assigned ones, which suggests increasing engagement.
Moderate; goal remains active.
Fair to good.
Continue weekly individual therapy.
Assign behavioral activation schedule with pottery class added for the coming week.
Introduce cognitive restructuring targeting the automatic thought “I've already wasted the whole day.”
Readminister PHQ-9 in four weeks.
03/19/2026
2. Progress Note Example: Anxiety in Individual Therapy Using BIRP
Client reported three panic episodes since the last session, all triggered by group meetings at work, stating, “I can feel it coming about ten minutes before and there's nothing I can do.” Described leaving two meetings early.
Presented with visible psychomotor agitation, shifting position repeatedly and maintaining limited eye contact. Speech rapid. Affect anxious, congruent with stated mood.
Score 15 (severe), unchanged from two weeks ago.
Denied SI/HI; no safety concerns identified.
Provided education on the avoidance-maintenance cycle, using the client's two early departures from work meetings as the worked example.
Introduced the rationale for interoceptive exposure and collaboratively constructed a graded exposure hierarchy with eight steps, ranging from listening to a recorded meeting (SUDS 20) to speaking unprompted in a full team meeting (SUDS 90).
Reviewed previously taught diaphragmatic breathing and corrected technique after observing that the client had been breathing shallowly and rapidly.
Client engaged actively in building the hierarchy and volunteered three items independently. Initially resistant to the exposure rationale, stating, “So your advice is to make it worse?”
Resistance was explored. By the end of the discussion, the client was able to articulate the difference between escape and habituation and agreed to attempt step 2.
Practiced corrected breathing for four minutes and reported a subjective decrease from SUDS 55 to SUDS 30.
Complete hierarchy step 2 — remain in a meeting for its full duration with breathing support — at least twice before the next session. Log SUDS before, during, and after each attempt.
Continue weekly individual therapy.
Discuss psychiatric consultation for medication support at the next session if GAD-7 remains above 12.
03/19/2026
3. Progress Note Example: Psychiatric Medication Management Using SOAP
Patient reports partial improvement in mood since the last visit eight weeks ago but continued anhedonia and difficulty concentrating at work: “The crying stopped but I still can't make myself care about anything.”
Reports taking sertraline 150 mg daily without missed doses.
Denies nausea, sexual side effects, or activation.
Sleep improved to 7 hours from 4 to 5 hours. Appetite unchanged.
No alcohol or substance use reported.
Alert and oriented x4. Adequately groomed. Psychomotor activity within normal limits. Mood described as “flat”; affect constricted but reactive. Speech normal. Thought process linear. No psychotic symptoms.
Score 16, unchanged from 16 eight weeks ago.
No SI/HI identified.
168 lb; stable.
118/76
Major Depressive Disorder, Recurrent, Moderate (F33.1)
Inadequate response to sertraline 150 mg after eight weeks at a therapeutic dose. PHQ-9 remains unchanged despite reported improvement in tearfulness and sleep.
Residual anhedonia, low energy, and concentration impairment remain the primary drivers of occupational impairment.
Discussed three options with the patient: increase sertraline, augment treatment, or cross-taper to an alternative agent. Patient prefers augmentation given the partial response already achieved.
Add bupropion XL 150 mg daily to target low energy, anhedonia, and concentration. Continue sertraline 150 mg daily.
Reviewed seizure risk, blood pressure effects, insomnia, and interaction monitoring. Patient verbalized understanding and agreement.
Follow up in four weeks with repeat PHQ-9.
Contact the office for agitation, worsening insomnia, or any emergence of suicidal thoughts.
Continuing weekly therapy with current therapist; release on file.
4. Progress Note Example: Crisis Psychotherapy Encounter
Client contacted the office at 15:20 requesting an urgent appointment following the loss of her job that morning. Seen same day.
Client presented tearful and visibly distressed, with psychomotor agitation. Speech pressured at times. Affect dysphoric and labile. Thought process goal-directed but ruminative. Oriented x4. No perceptual disturbance. Insight fair; judgment currently impaired by acute distress.
“I keep thinking it would be easier if I just did not wake up tomorrow.”
Client denied thoughts of taking action, a method, intent, or plan.
Item 1 positive; items 2 through 5 negative.
Access to medications and firearms, prior self-harm, substance use, protective factors, and ability to use supports.
A trazodone supply at home was identified and addressed in the safety plan.
Acute distress and new passive suicidal thoughts increased concern relative to the prior visit.
Completed a collaborative safety plan and reviewed warning signs and support contacts.
Practiced grounding techniques during the session.
Discussed steps to reduce access to medication.
Disposition was determined after the full assessment and consultation rather than from the screening score alone.
Supervisor T. Ramos, LCSW-S
Consultation addressed the assessment, medication access, and follow-up plan.
The team agreed to outpatient follow-up after confirming the means-safety arrangement with the client and her sister, with the client’s permission. The rationale and consultation were recorded.
Client reviewed the safety plan and identified whom to contact if suicidal thoughts intensified, including 988 and local emergency services.
Clinician arranged a next-day check-in.
03/14/2026
Visit frequency increased temporarily.
Psychiatric evaluation requested.
Treatment plan will be reviewed for a safety-focused objective.
5. Progress Note Example: Substance Use Counseling Using DAP
Client reported one drinking episode since the last session, describing four beers on Friday evening following a conflict with his brother: “I was doing fine for eleven days and then I just wasn't.”
Day 4
Attended 2 of 3 planned meetings.
Denied cravings in the past 48 hours.
Not readministered this session.
Presented on time, adequately groomed, with no signs of acute intoxication or withdrawal. Affect subdued and congruent. Speech normal. Oriented x4.
Denied SI/HI; no safety concerns identified.
Alcohol Use Disorder, Moderate (F10.20)
Client reported one drinking episode after eleven days without alcohol. The episode followed an interpersonal trigger identified in earlier sessions.
Recognizing the interpersonal trigger, using an alternative coping response, and monitoring drinking and related functioning.
The reported lapse alone does not establish a remission specifier.
Conducted a functional analysis of the Friday drinking episode, mapping the trigger, thoughts, urge intensity, and consequence.
Added a family-conflict coping plan to the relapse prevention worksheet, including a pre-arranged exit script and a call to his sponsor.
Reinforced that disclosure of the lapse was clinically valuable.
Complete one urge-surfing log and attend three recovery meetings before the next session.
Continue weekly.
03/19/2026
6. Sample Progress Note: Group Therapy Summary and Individual Member Note
Engagement was high in the psychoeducation segment and dropped during in-vivo practice, with three members declining the temperature exercise. Facilitator normalized reluctance and reframed the exercise as optional exposure.
Two members disclosed using distress tolerance skills successfully during the past week, which visibly shifted group buy-in.
No safety concerns arose in group.
Assessed as improving.
“Client will demonstrate use of at least two distress tolerance skills when experiencing urges to self-harm, reducing self-harm incidents from weekly to no more than monthly within 90 days.”
Client participated in psychoeducation on TIPP skills and in-vivo practice of paced breathing.
Facilitator provided coaching on pacing when the client's breathing rate remained elevated during the exercise.
Client was prompted to share her own use of a distress tolerance skill during the past week.
Client was verbally engaged throughout, contributing three times without prompting — an increase from one contribution in each of the prior two groups.
Declined the temperature exercise, stating, “Cold stuff is a hard no for me,” and this was accepted without further prompting.
Successfully completed paced breathing after coaching and reported a subjective drop in tension.
Reported using paired muscle relaxation twice during the week instead of self-harming.
Reports no self-harm incidents in the past two weeks, down from weekly at treatment start.
Continue weekly DBT skills group.
Client to log each TIPP skill use before the next group.
Individual therapist to be notified of the two-week self-harm-free interval for treatment plan review.
Substantial; goal remains active.
03/19/2026
7. Sample Progress Note: Case Management Contact Using PIE
Client's Medicaid benefits are scheduled to lapse 03/31/2026 due to an incomplete redetermination packet, placing continued access to psychiatric medication at risk.
Client reported that she received the packet but “couldn't figure out the income part” and set it aside.
Reports taking medication as prescribed.
Denied current psychiatric crisis.
Denied SI/HI.
Affect anxious but organized; speech normal.
Walked client through the income verification section by phone and identified that two pay stubs plus a written statement from her employer would satisfy the requirement.
Contacted the county benefits office with the client's signed release on file and spoke with caseworker R. Alvarez, reference #88231.
Confirmed the submission deadline and that fax submission is accepted.
Scheduled a clinic appointment for 03/17/2026 to complete and fax the packet together.
Confirmed that a 14-day medication supply remains and contacted the prescriber's office to request a 30-day bridge supply as a contingency.
Client was cooperative and engaged throughout the call and expressed relief at having a scheduled appointment rather than a deadline.
Client was able to restate the two documents she needs to bring, indicating adequate comprehension.
Client reports difficulty with written administrative forms generally, which has now affected two separate benefit processes.
This recurring pattern should be reflected in the case management plan rather than treated as a one-time problem.
Maintain uninterrupted benefit coverage — rated as on track.
Meet in person to complete and submit the Medicaid redetermination packet.
Confirm bridge supply received before 03/20/2026.
Propose adding a case management objective addressing administrative-form support at the next treatment plan review.
8. Sample Progress Note: Couples Therapy Using DAP
Couple reported two escalated arguments since the last session, both beginning over household logistics and ending with one partner leaving the room.
J.M. raises a concern, R.M. responds with a correction of factual detail, J.M. escalates in volume, and R.M. disengages.
Both partners were able to describe the sequence when it was named.
Constricted affect with tearfulness at two points.
Guarded initially, warming over the session.
Screened separately at intake and re-screened this session; both denied intimate partner violence.
Neither partner reported safety concerns. No SI/HI reported by either party.
The pursue-withdraw cycle documented at intake remains the primary maintaining dynamic.
Notably, both partners identified the pattern in session this week without therapist prompting, which is new and represents the first observable movement on Goal 1.
Content of the arguments continues to be secondary to the interactional process.
J.M.'s individual depressive symptoms appear to amplify the pursuit behavior and should continue to be addressed in her concurrent individual treatment.
Used enactment to slow one logistics disagreement in real time, interrupting at the point of escalation.
Coached J.M. to state the underlying need rather than the complaint.
Coached R.M. to reflect before correcting.
Both partners completed the enactment with support.
Each partner will note one instance of the pursue-withdraw cycle during the week without attempting to fix it.
Continue biweekly conjoint sessions.
03/26/2026
9. Sample Progress Note: Telehealth Therapy Using SOAP
Session conducted via the practice's HIPAA-compliant video platform with two-way audio and video throughout. No technology disruptions occurred; video quality was adequate for observation of affect and psychomotor activity.
Client's residence in Springfield, Illinois.
Clinic office in Illinois.
Client identity verified by visual recognition and date of birth.
Telehealth informed consent on file, dated 01/08/2026, and verbally reconfirmed by the client at the start of the session.
Emergency contact and current physical address confirmed, and nearest emergency department identified.
Client confirmed she was alone and in a private space.
Client reported a difficult week following a performance review at work, stating, “It confirmed everything I already thought about myself.”
Reports two nights of initial insomnia.
Completed the assigned thought record on 3 of 7 days.
Visible from mid-torso up; appeared adequately groomed. Affect dysphoric, reactive, and congruent with stated mood. Speech normal in rate and volume. Thought process linear. No perceptual disturbance apparent. Insight good.
Score 11, up from 9 two weeks ago. Administered through the patient portal prior to the session.
Denied SI/HI; no plan, intent, or means concerns. No current safety concerns.
Persistent Depressive Disorder (F34.1)
Modest symptom increase following an identifiable stressor, consistent with the reactivity pattern documented in the treatment plan rather than a change in baseline.
Completed thought records demonstrate accurate identification of cognitive distortions, with continued difficulty generating alternative thoughts.
Telehealth remains clinically appropriate: client is stable, has no elevated risk factors, and reports that the modality improves attendance.
Continue weekly telehealth sessions.
Focus on generating and rating alternative thoughts rather than identification alone.
Complete thought records daily, adding the alternative-thought column.
Readminister PHQ-9 in two weeks.
03/19/2026
10. Sample Progress Note: IDD Skills Support Using BIRP
Client arrived on time and greeted staff independently. Two instances of task refusal occurred during the scheduled kitchen activity, both at the transition point between steps, presenting as verbal refusal “no, done” and moving away from the counter.
2 instances, both occurring during transitions between task steps.
Verbal refusal and moving away from the counter.
Client used her communication device to request a break on the second occasion — the first independent break request recorded this month.
No aggression, self-injury, property destruction, or other safety concerns observed.
Delivered the visual task-sequence support outlined in the behavior support plan, presenting three steps at a time rather than the full six.
Provided a two-minute advance warning before each transition.
Reinforced the independent break request immediately with verbal praise and an honored two-minute break.
Used least-to-most prompting on the third and fourth steps: independent, then gestural, then partial physical.
Completed 5 of 6 kitchen-task steps, up from 3 of 6 at the last recorded session.
Gestural prompting on 2 steps and partial physical prompting on 1 step.
Independent break request occurred once.
Client returned to the task independently after the honored break.
90 seconds
25 seconds
Continue the three-step visual sequence.
Continue the two-minute transition warning.
Continue reinforcing independent break requests on a continuous schedule for the next two weeks before thinning.
Add a fourth step to the independent sequence if step completion remains at 5 of 6 for three consecutive sessions.
Report the new break-request skill to the team for the treatment plan review due 04/02/2026.
Use Objective Language in Mental Health Progress Notes
A useful note distinguishes the client's report, what the clinician observed, and the clinician's interpretation. Replace unsupported labels with the behavior or statement that led to your assessment.
| Instead of | Write |
|---|---|
| "Client was manipulative." | "Client repeatedly redirected the session away from discussion of the incident; when the clinician returned to the topic, client changed the subject or began crying. Pattern was noted and explored." |
| "Client is non-compliant." | "Client reports not completing the between-session thought records for the third consecutive week. Barriers to completion explored; client identifies time constraints and low motivation as factors." |
| "Client was resistant." | "Client declined to engage with the cognitive restructuring exercise, stating, 'I don't see the point of this.' Clinician explored the hesitation; client identified prior negative experience with a similar exercise." |
| "Client has poor insight." | "Client denied that substance use is problematic despite reporting two DUI arrests in the past year and relationship disruption attributed by family to substance use. Insight rated as limited." |
| "Client seemed like she was lying." | "Client's account of events differed from the account provided at the last session. Discrepancy noted; clinician did not comment on it but observed that affect was flat throughout the discussion." |
| "Client is doing well." | "Client reports reduction in depressive symptoms. PHQ-9 score 6, down from 14 at last administration. Reports returning to work full time and resuming daily exercise." |
| "Client is stable / unchanged." | "No significant change in symptom presentation from the prior session; client reports continued baseline level of initial insomnia and mid-day fatigue." |
| "Client denied everything." | "Client denied suicidal ideation, homicidal ideation, auditory and visual hallucinations, and current substance use." |
| "Provided counseling." | "Introduced cognitive restructuring to address the automatic thought 'I am a failure.' Client identified three cognitive distortions and generated two alternative balanced thoughts with moderate success." |
| "Discussed issues." | "Used motivational interviewing to explore ambivalence about reducing alcohol use; elicited change talk regarding the impact on parenting." |
Replace labels with observations
Some labels can obscure the observation behind them or sound judgmental if a client reads the record. A clinical term may still be appropriate when it is supported by the assessment; explain the basis rather than relying on the label alone.
Cultural considerations
Use the language the client uses to describe themselves, in quotation marks where appropriate. Document cultural, spiritual, and community strengths as part of the clinical picture rather than recording only deficits. Do not document culturally normative beliefs or practices as symptoms unless they represent a departure from the client's own cultural norms and are causing distress or impairment.
Mental Status Exam Language to Adapt
In a mental health progress note, include mental-status findings relevant to the encounter and any meaningful change from baseline. The examples below are prompts, not default text. Record only what you assessed or observed, and use greater detail when presentation or risk calls for it.
| Domain | Within normal limits | Notable findings |
|---|---|---|
| Appearance | "Adequately groomed, dressed appropriately for weather and setting, appears stated age." | "Disheveled; wearing clothing appearing unwashed; appears older than stated age." |
| Behavior / psychomotor | "Psychomotor activity within normal limits. Eye contact appropriate. Gait steady." | "Psychomotor retardation observed"; "Psychomotor agitation; shifted position repeatedly and wrung hands throughout"; "Fine tremor noted in bilateral hands." |
| Attitude | "Cooperative and engaged throughout." | "Guarded; answered direct questions briefly and did not elaborate"; "Initially hostile, softening over the course of the session." |
| Mood | "Mood described by client as 'okay.'" | "Mood described by client as 'empty'"; "Client described mood as 'furious, all the time.'" |
| Affect | "Affect full range, reactive, congruent with stated mood." | "Affect constricted"; "Affect blunted and incongruent with content"; "Affect labile, shifting from tearful to laughing within minutes"; "Affect flat." |
| Speech | "Speech normal in rate, volume, tone, and fluency." | "Speech pressured and difficult to interrupt"; "Speech slowed with increased latency of response"; "Speech reduced in volume, nearly inaudible at times." |
| Thought process | "Thought process logical, linear, and goal-directed." | "Thought process tangential; required redirection three times"; "Circumstantial"; "Loose associations noted"; "Thought blocking observed twice." |
| Thought content | "No delusions, obsessions, or paranoid ideation elicited. Denied SI/HI." | "Persecutory ideation reported regarding neighbors"; "Ruminative content focused on past employment"; "Endorsed passive suicidal ideation without intent or plan." |
| Perception | "No perceptual disturbance reported or observed." | "Reported auditory hallucinations, described as a single male voice commenting on her actions, occurring daily"; "Appeared to respond to internal stimuli twice during the session." |
| Cognition | "Alert and oriented x4. Attention and concentration intact. Recent and remote memory grossly intact." | "Oriented to person and place, not to date"; "Concentration impaired; unable to complete serial sevens"; "Difficulty recalling two of three objects at five minutes." |
| Insight | "Insight good — client connects symptoms to identified stressors." | "Insight limited; client attributes symptoms exclusively to external circumstances despite documented pattern." |
| Judgment | "Judgment intact; able to describe appropriate responses to hypothetical scenarios." | "Judgment impaired by acute distress"; "Judgment questionable given reported decision to discontinue medication without consultation." |
Standardized measures worth documenting
When a measurement from a rating scale is clinically relevant, name the instrument, record the score, and compare it with prior results when available. A score can help describe change, but it does not by itself establish treatment effectiveness or medical necessity.
- PHQ-9 — depression. Range 0—27. Minimal 0—4, mild 5—9, moderate 10—14, moderately severe 15—19, severe 20+
- GAD-7 — generalized anxiety. Range 0—21. Minimal 0—4, mild 5—9, moderate 10—14, severe 15+
- PCL-5 — PTSD. Range 0—80; provisional diagnosis suggested at 33+
- C-SSRS — Columbia Suicide Severity Rating Scale
- AUDIT-C — alcohol use
- MDQ — bipolar spectrum
- Y-BOCS — OCD
Behavioral Health Progress Notes and Billing Codes
A behavioral health progress note should support the service billed. Code choice depends on the service delivered, clinician type, time or medical decision-making when applicable, and payer policy. The table below is a quick orientation, not a substitute for current code guidance.
Common behavioral health CPT codes
| Code | Service | Time requirement |
|---|---|---|
| 90791 | Psychiatric diagnostic evaluation, without medical services | No specific CPT time requirement; without medical services |
| 90792 | Psychiatric diagnostic evaluation, with medical services | No specific CPT time requirement; includes medical services |
| 90832 | Individual psychotherapy | 16—37 minutes |
| 90834 | Individual psychotherapy | 38—52 minutes |
| 90837 | Individual psychotherapy | 53 minutes or more |
| 90833 / 90836 / 90838 | Psychotherapy add-on, billed with an E/M code | 16—37 / 38—52 / 53+ minutes of psychotherapy, documented separately from the E/M service |
| 90839 / 90840 | Psychotherapy for crisis (first 60 min / each additional 30 min) | 30—74 minutes for 90839 |
| 90846 | Family psychotherapy, without the patient present | Confirm current code and payer requirements |
| 90847 | Family or couples psychotherapy, with the patient present | Confirm current code and payer requirements |
| 90853 | Group psychotherapy | No specific time requirement; document actual duration |
| 90785 | Interactive complexity add-on | Add-on; document the specific complicating factor |
Psychiatric diagnostic evaluation codes 90791 and 90792 differ by whether medical services are included. Office or outpatient E/M codes such as 99204 and 99205 are not psychiatric diagnostic evaluation codes. When psychotherapy is furnished with an E/M service, document the psychotherapy service and its time separately from the E/M work, and confirm that the applicable add-on code is supported.
What the record should support
- Time and service. Record start and stop times or total time as required by the code and payer. For time-based psychotherapy codes, compare the documented psychotherapy time with the current code definition.
- Clinical rationale. Describe the symptoms or functional concerns addressed and why the service and level of care were appropriate.
- Intervention and response. Name what you did with enough detail to distinguish the service and document how the client responded. For an EMDR encounter, include the phase, target, and ratings when clinically relevant and consistent with your documentation standard.
- Treatment direction. Explain how the encounter relates to the diagnosis and plan when applicable, and what happens next.
Check the current AMA CPT code set, CMS guidance for Medicare, and the individual payer's policy before billing. Coding requirements can change and may differ by setting. CMS billing and coding guidance.
Common Mental Health Progress Note Mistakes
- Copying previous notes. Reused language may hide meaningful changes in the client's presentation or the service provided. Review each note for accuracy before signing.
- Omitting treatment direction. When relevant, show how the encounter relates to a goal or explain why the plan needs review.
- Leaving out clinically relevant risk findings. Document the assessment and response when risk is indicated. Follow your setting's policy for routine screening and documentation.
- Recording time that conflicts with the billed service. Reconcile the record and code before submission.
- Describing interventions vaguely. Name the technique or service and the client's response.
- Backdating a late entry. Record the encounter date and the actual date of entry under your organization's correction and late-entry policy.
- Repeating "no progress" without context. Describe barriers, clinical reasoning, and any change or review of the treatment plan.
Mental Health Progress Note Review Checklist
Use this mental health progress note checklist before signing, alongside the requirements for your role, setting, and payer.
How Strong Are Your Progress Notes?
Take our free 5-minute Progress Note Self-Assessment Tool to see how your documentation stacks up. Identify gaps, reduce compliance risk, and get practical insight into whether your notes are audit-ready.
It’s a quick way to spot documentation weaknesses before they become billing or compliance problems.
Take the 5-Minute Self-Assessment
Write Mental Health Progress Notes More Efficiently
A practical mental health progress note workflow makes it easier to capture the encounter while the details are fresh. Templates can prompt for missing information, but each note still needs the clinician's review and encounter-specific judgment.
Habits that save the most time
Document promptly
Complete the note as soon as practical and within your organization's and payer's required timeframe.
Use a short transition when available
Record key findings before moving to the next encounter, even if you finish the full note later.
Jot key phrases
If you cannot write the full note immediately, capture three or four specific phrases — a direct quote, the intervention, the client's response — before you lose the detail.
Block documentation time
Protect it in the schedule so it does not get displaced by back-to-back sessions.
Build a phrase library
Normal MSE findings, standard safety language, your most-used interventions. Templates should prompt you, not complete your documentation for you.
What to look for in progress note software
- Auto-populated session details — date, time, duration, modality, provider, client identifiers
- Prebuilt templates for each visit type you actually run, not just "therapy session"
- Click-to-add clinical interventions that produce narrative text rather than checkbox output
- Built-in risk assessments and outcome measures with score tracking over time
- Treatment plan goals that carry into the note automatically, so the Golden Thread is structural
- A real amendment and addendum function with an audit trail — never direct editing of a finalized note
- Access controls, audit logs, and safeguards appropriate to the practice's HIPAA obligations
Build audit-ready progress notes faster in ICANotes
ICANotes is an EHR built for behavioral health workflows, with menu-driven charting that connects your notes to the treatment plan. Start a free trial and document a real visit type end to end.
- Build mental health progress notes with guided, menu-driven charting.
- Bring active treatment-plan goals into notes to document progress toward them.
- Built-in PHQ-9, GAD-7 & risk screeners with tracking
- Auto-filled session details and CPT-aligned time
See how ICANotes can support your clinical workflow. Start your free 30-day trial, no credit card required.
Start Your Free 30-Day Trial
Frequently Asked Questions
How long should a mental health progress note be?
How often should I write mental health progress notes for each client?
What is the difference between progress notes and psychotherapy notes?
Which progress note format should I use?
What happens if I write a progress note late?
Can I copy and paste from a previous progress note?
Are there words I should avoid in progress notes?
How long do I have to keep progress notes after treatment ends?
Can I use dictation or AI scribes for progress notes?
How detailed do progress notes need to be for insurance reimbursement?
Dr. October Boyles
Dr. October Boyles is a behavioral health expert and clinical leader with extensive expertise in nursing, compliance, and healthcare operations. With a Doctor of Nursing Practice (DNP) and advanced degrees in nursing, she specializes in evidence-based practices, EHR optimization, and improving outcomes in behavioral health settings. Dr. Boyles is passionate about empowering clinicians with the tools and strategies needed to deliver high-quality, patient-centered care.





